超声评估唇部解剖与玻尿酸填充剂位置:精准度、移位与人群差异
2026年9月12日31 min read
Plastic and Reconstructive Surgery
结论与实践要点
循证层面:本研究为 126 例、双中心横断面超声研究(证据等级中等),提供了 HA 唇部注射「非预期肌内放置」以及垂直注射致更深沉积、高血管化与移位的量化证据。
局限:为单时点横断面,缺乏长期随访与患者主观满意度数据;「移位」以超声下填充剂位置异常 + 高血管化间接提示,未给出血流动力学因果;未设盲法评估。
临床提示:唇部皮下层极薄(<1 mm),注射应优先浅层(黏膜下 / 结缔组织)线性或团块浅置,避免垂直深插导致肌内放置与血管损伤;治疗前可用高频超声评估个体唇层厚度与血管分布,落实个体化进针层次。
Background:Lip fillers composed of hyaluronic acid are commonly used for aesthetic enhancement, yet the anatomical changes they induce and their relationship to demographic factors remain incompletely understood.
Methods:A cross-sectional study of 126 participants was conducted at clinics in London and Amsterdam. High-frequency ultrasound was used to assess lip layer thickness, submucosal gland dimensions, and filler position. Demographic data were recorded and correlated with anatomical findings and filler distribution.
Results:Treated patients demonstrated significantly increased thickness in the connective tissue and pars peripheralis layers. The subcutaneous layer averaged less than 1 mm in both upper and lower lips, resulting in intramuscular filler placement in most treated individuals. Vertical injection techniques were associated with deeper filler deposition, hypervascularity, and evidence of migration. Lip anatomy varied significantly with sex, race and ethnicity, body mass index, and age.
Conclusions:Hyaluronic acid fillers alter lip anatomy in measurable ways, often resulting in unintended intramuscular placement due to the limited subcutaneous space. Demographic factors significantly influence lip structure and filler behavior, supporting the need for individualized treatment planning. Future studies should investigate long-term outcomes and patient perspectives.
Lip augmentation using hyaluronic acid (HA) fillers is among the most frequently performed procedures in aesthetic medicine, offering enhancement of volume, shape, and symmetry. 1 Contemporary injection techniques increasingly emphasize natural outcomes and safety, but the precise in vivo behavior of HA fillers within lip tissues remains insufficiently understood. 2 Most techniques rely on anatomical landmarks and clinical experience, with little direct feedback on actual filler deposition relative to intended anatomical planes.
High-frequency ultrasound has emerged as a valuable tool in facial aesthetic medicine, enabling noninvasive visualization of soft-tissue architecture and filler localization. 3 , 4 Early ultrasonographic studies have shown that even when superficial injection techniques are used, targeting dermal or subcutaneous planes, filler product frequently localizes within the orbicularis oris muscle, particularly the pars marginalis. 5 This unexpected intramuscular placement may influence treatment longevity, aesthetic outcomes, and the risk of complications, such as vascular compromise or nodularity. 6
Another underexplored area involves the role of demographic variation in lip anatomy and filler behavior. Lip thickness, connective tissue density, and submucosal gland presence may vary by age, sex, race and ethnicity, and body mass index (BMI), yet these variables are rarely accounted for in treatment planning. 7 Understanding how these factors influence filler distribution and anatomical response is essential for developing individualized, safe, and effective enhancement strategies.
The current study addresses these knowledge gaps through a cross-sectional, ultrasound-based assessment of lip anatomy in patients with and without previous HA filler treatment. We aimed to characterize normative lip layer thickness and glandular structures, evaluate the discrepancy between intended and actual filler placement, identify patterns of technique-related migration, and examine correlations between demographic factors and both anatomical and filler-related findings. By elucidating the anatomical realities of lip filler procedures, this study seeks to inform a more personalized and evidence-based approach to aesthetic lip enhancement.
A total of 126 participants were enrolled in this cross-sectional observational study, including patients who had previously received HA lip filler treatment ( n = 52) and those with no history of lip augmentation ( n = 74). History of lip filler treatment (from practitioner notes) included product, volume, technique, and target layer; protocols were recorded when available. Vertical techniques (eg, tenting, “Russian lip”) were classified from patient self-report or clinics advertising these methods. Horizontal injections were represented by the nonsurgical lip tubercle (NLT) technique. ( See Video [online] , which demonstrates the NLT technique, showing bolus and linear thread superficial placement for enhancement of the right lower tubercle.)
An equal number of participants ( n = 63) were recruited from a private aesthetic clinic in London, United Kingdom; a private clinic in Amsterdam, the Netherlands; and Erasmus University Medical Centre in Rotterdam, the Netherlands. All participants provided written informed consent for the use and analysis of their anonymized data. The study was approved by local ethics committees and conducted in accordance with the Declaration of Helsinki (2013 revision), applicable local laws, and Good Clinical Practice guidelines for research involving human subjects.
Inclusion criteria were age 18 years or older, willingness and ability to provide informed consent, and ability to comply with ultrasound imaging and data collection procedures.
Exclusion criteria were history of permanent fillers or non-HA injectables in the lips, active skin or mucosal conditions of the lips (eg, herpes labialis, cheilitis), previous lip surgery or trauma, pregnancy or lactation, or any medical condition contraindicating ultrasound imaging or HA filler treatment.
补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)prs-158-065e-s001.mp4Video. This video demonstrates the NLT technique, showing bolus and linear thread superficial placement for enhancement of the right lower tubercle.
Ultrasound measurements were performed between September 1, 2024, and December 12, 2024, using high-frequency linear probes: a 20-MHz transducer (GE Venue Go/Venue Fit; GE Healthcare) or an 18-MHz transducer (Philips Affiniti 70). Additional anatomical comparisons were performed in a Logiq E10 with a compact linear probe up to 24 MHz (GE Healthcare) and a Vevo MD with a probe up to 70 MHz (Fujifilm VisualSonics). All scans were performed by experienced clinicians using a standardized protocol for probe orientation, landmarking, and measurement points. To assess reliability, repeated scans were performed in 20 patients. Multiple ultrasound systems were used (GE Venue Go, Philips Affiniti 70, Logiq E10, and Vevo MD), but only high-frequency linear probes with standardized settings were used. These measures were taken to minimize operator- and device-related variability.
Table 1 presents a list of abbreviations used throughout the article.
Table 1. Abbreviations
| Abbreviations | Definitions |
|---|---|
| L | Lower lip subcutaneous layer thickness |
| LC | Connective tissue layer of lower lip |
| LG | Lower gland (lower lip mucosal gland greatest width) |
| LM | Pars marginalis muscle layer of lower lip |
| LP | Pars peripheralis muscle layer of lower lip |
| LT | Total thickness (of all layers) of lower lip |
| LW | Wet mucosal layer of lower lip |
| U | Upper lip subcutaneous layer thickness |
| UC | Connective tissue layer of upper lip |
| UG | Upper gland (upper lip mucosal gland greatest width) |
| UM | Pars marginalis muscle layer of upper lip |
| UP | Pars peripheralis muscle layer of upper lip |
| UT | Total thickness (of all layers) of upper lip |
| UW | Wet mucosal layer of upper lip |
| VP | Vertical position of ultrasound probe |
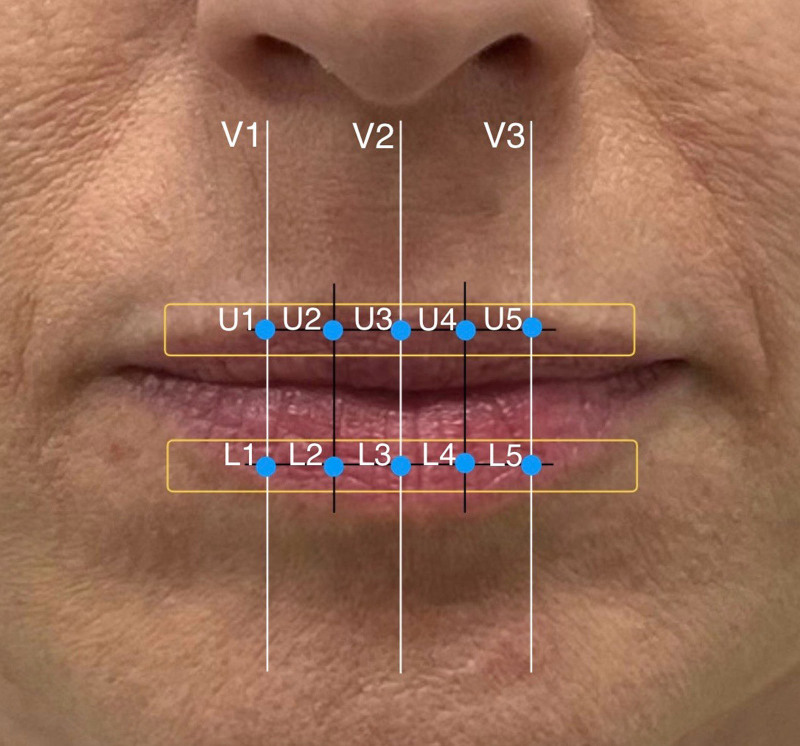
Five anatomical layers of the lips were measured at 5 predetermined midline points (Figs. 1 and 2 ), encompassing the subcutaneous layer (U1 through U5 and L1 through L5); the pars marginalis of the orbicularis oris muscle (UM1 through UM5 and LM1 through LM5); connective tissue (UC1 through UC5 and LC1 through LC5); pars peripheralis (UP1 through UP5 and LP1 through LP5); and wet mucosa (UW1 through UW5 and LW1 through LW5).
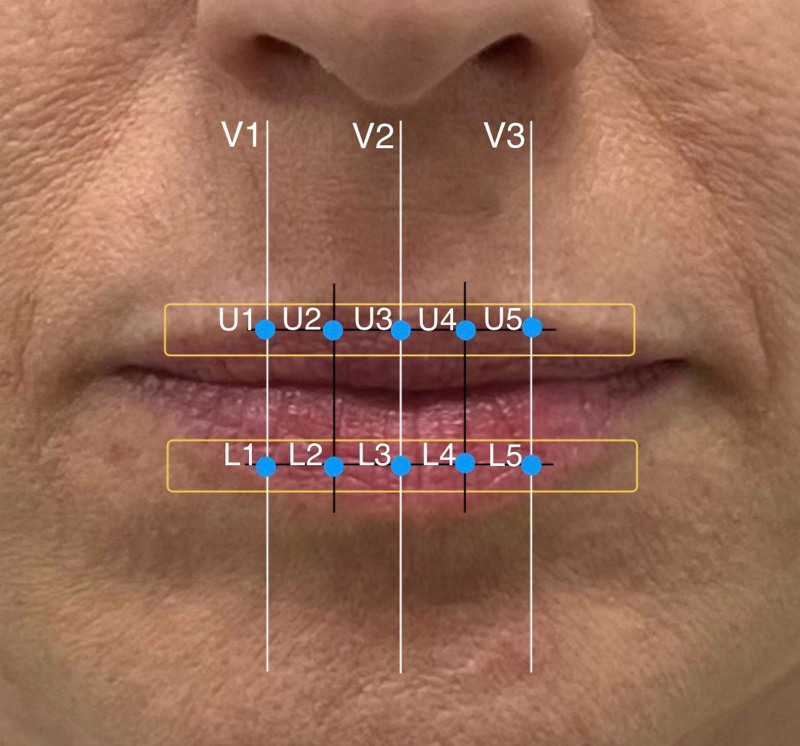
Fig. 1. The horizontal position of the probe (held at a right angle to the surface of the lips) to measure the thickness of the layers at 5 points (between the width of the base of the nose) for the upper lip (U1 through U5) and lower lip (L1 through L5) and the vertical position to measure continuity of the subcutaneous layer and filler spread (V1 through V3).探头水平放置(与唇面垂直)于 5 点测量上下唇各层厚度的示意。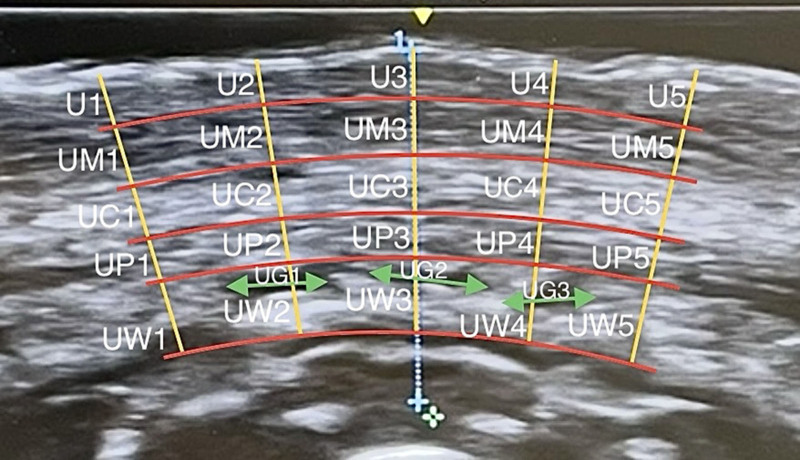
Fig. 2. Ultrasound cross-sectional image of the upper lip showing measurements of the subcutaneous layer (U1 through U5), pars marginalis (UM1 through UM5), connective tissue (UC1 through UC5), pars peripheralis (UP1 through UP5), wet mucosa (UW1 through UW5), and the 3 largest glands (UG1 through UG3). The total lip thickness at each point is abbreviated UT1 through UT5 (not shown). B-mode image acquired at 20 MHz using a linear transducer.上唇超声横断面:显示皮下层、缘层、结缔组织、周边层、湿黏膜等层厚测量点。In addition, the 3 largest identifiable submucosal glands were measured in both upper and lower lips (UG1 through UG3 and LG1 through LG3). Total lip thickness was calculated at each point (UT1 through UT5 and LT1 through LT5).
Probe positioning followed a standardized protocol: horizontal orientation for cross-sectional imaging at 5 points between the philtral columns (U1 through U5 and L1 through L5) and vertical orientation for longitudinal imaging and evaluation of layer continuity and filler migration (V1 through V3).
To ensure measurement reliability, intrarater assessments were repeated for 20 participants (10 per site), with a 2-week interval between scans. Concordance was assessed using intraclass correlation coefficients (ICCs).
The following variables were recorded for all participants: age, sex, race and ethnicity, and BMI; lip type according to the Lip Classification of Tubercles; lip fullness per the validated Teoxane Lip Fullness Scale; history of lip filler treatment (as per available practitioner notes), including product brand, volume, injection technique, and anatomical target layer; presence of filler spread or migration, including notation of vertical or horizontal probe position, with spread categorized as single-plane (SC only), 2-plane (SC + PM), or multiplane (3 or more layers), with note of cases confined exclusively to the subcutaneous layer); ultrasound signs of hypervascularity; and history of lower face botulinum toxin type A treatment within the previous 6 months.
Of the 126 participants included, 109 were women and 17 were men. The mean patient age was 34.6 ± 9.8 years. There was equal recruitment from London and Amsterdam. Fifty-two participants had previously received HA lip fillers, and 74 were untreated. Because this was an exploratory cross-sectional study, no a priori power calculation was performed.
Intrarater reliability was moderate to excellent across most aggregated lip layer measurements. Intrarater reliability testing in 20 participants demonstrated moderate to excellent agreement across lip layers (ICC range, 0.71 to 0.89). Reliability was lower in individual upper lip gland measurements, but overall agreement remained acceptable. ( See Table, Supplemental Digital Content 1 , which shows ICCs demonstrating moderate to excellent reliability for most lip layer measurements, with lower reliability for upper lip gland measures, https://links.lww.com/PRS/I548.)
Lower lip layers were significantly thicker than upper lip layers across most anatomical regions, with the greatest differences observed in the wet mucosa ( P < 0.001) and connective tissue ( P < 0.001) layers. A significant interaction was found between lip position and layer ( F 3.01,376.67 = 3.34; P < 0.02), indicating regional variation in thickness by lip location (Table 2 and Fig. 3 ).
Table 2. Descriptive Statistics of Lip Layer Thickness by Lip Positiona
| Measure | Mean | SD |
|---|---|---|
| U | 1.47 | 0.34 |
| L | 1.65 | 0.42 |
| UM | 1.37 | 0.35 |
| LM | 1.43 | 0.40 |
| UC | 1.61 | 0.56 |
| LC | 1.87 | 0.62 |
| UP | 1.53 | 0.38 |
| LP | 1.61 | 0.43 |
| UW | 2.26 | 0.71 |
| LW | 2.29 | 0.62 |
| UT | 8.36 | 1.30 |
| LT | 9.01 | 1.52 |
| UG | 2.69 | 0.62 |
| LG | 2.81 | 0.61 |
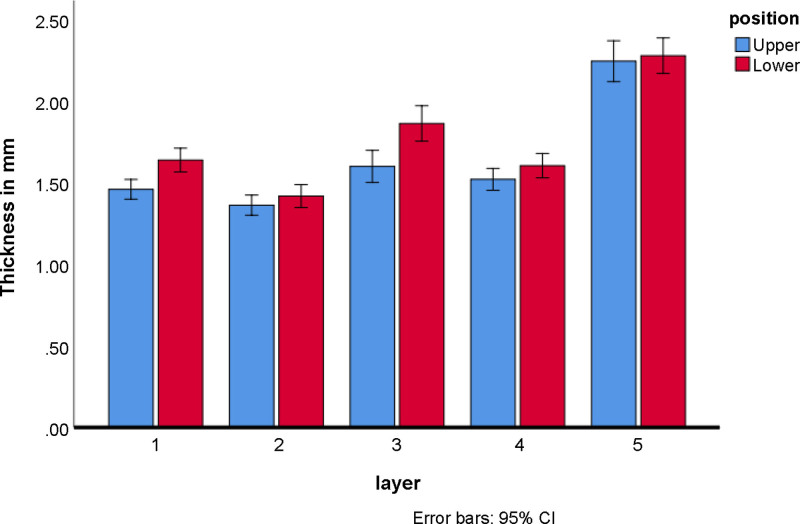
Fig. 3. Interaction effect of position and layer of the lip on thickness.唇部位置与层次对厚度的交互效应图。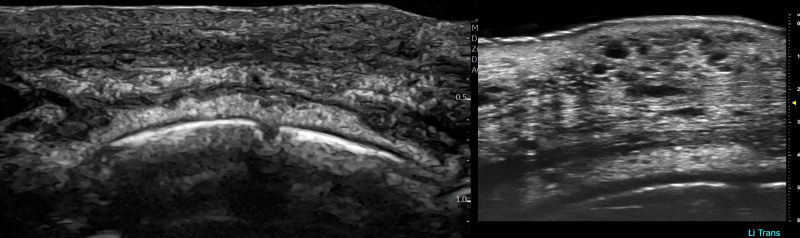
Fig. 4. Ultrasound cross-sectional image of the lower lip from the same patient, taken on the same day. The left image, obtained with an 18-MHz probe, shows isoechoic changes in the pars marginalis and connective tissue that are difficult to distinguish. The right image, captured with an ultra–high-frequency probe up to 70 MHz, reveals these same areas as distinct HA filler deposits within the same layers.同一患者下唇超声横断面:18-MHz 探头下缘层与结缔组织的等回声改变(较难区分)。
Male participants demonstrated significantly greater lip thickness in select layers, including the upper lip wet mucosa ( P = 0.02), total upper lip thickness ( P = 0.03), and total lower lip thickness ( P = 0.046). Differences on the basis of race and ethnicity were also observed: people with mixed race exhibited significantly greater lower lip subcutaneous thickness compared with White participants ( P = 0.01), and Asian/Chinese participants showed significantly greater lower gland thickness compared with Indian participants ( P = 0.046) (Tables 3 and 4 ).
Table 3. Descriptive Statistics and Significant t Test Results for Lip Layer Thickness by Sexa
| Layer and Group | No. | Mean | SD | t | df | P |
|---|---|---|---|---|---|---|
| U | ||||||
| Male | 17 | 1.58 | 0.43 | 1.50 | 124 | 0.14 |
| Female | 109 | 1.45 | 0.33 | |||
| UM | ||||||
| Male | 17 | 1.47 | 0.34 | 1.21 | 124 | 0.23 |
| Female | 109 | 1.35 | 0.36 | |||
| UC | ||||||
| Male | 17 | 1.59 | 0.44 | −0.18 | 124 | 0.86 |
| Female | 109 | 1.61 | 0.58 | |||
| UP | ||||||
| Male | 17 | 1.50 | 0.28 | −0.36 | 124 | 0.72 |
| Female | 109 | 1.53 | 0.40 | |||
| UW | ||||||
| Male | 17 | 2.62 | 0.75 | 2.32 | 124 | 0.02 |
| Female | 109 | 2.20 | 0.69 | |||
| UT | ||||||
| Male | 17 | 8.99 | 1.34 | 2.16 | 123 | 0.03 |
| Female | 109 | 8.26 | 1.27 | |||
| UG | ||||||
| Male | 17 | 2.49 | 0.59 | −1.43 | 106 | 0.16 |
| Female | 109 | 2.72 | 0.62 | |||
| L | ||||||
| Male | 17 | 1.78 | 0.37 | 1.45 | 124 | 0.15 |
| Female | 109 | 1.63 | 0.42 | |||
| LM | ||||||
| Male | 17 | 1.55 | 0.38 | 1.38 | 124 | 0.17 |
| Female | 109 | 1.41 | 0.40 | |||
| LC | ||||||
| Male | 17 | 1.81 | 0.39 | −0.46 | 124 | 0.65 |
| Female | 109 | 1.88 | 0.65 | |||
| LP | ||||||
| Male | 17 | 1.75 | 0.42 | 1.41 | 124 | 0.16 |
| Female | 109 | 1.59 | 0.43 | |||
| LW | ||||||
| Male | 17 | 2.33 | 0.51 | 0.25 | 124 | 0.80 |
| Female | 109 | 2.29 | 0.64 | |||
| LT | ||||||
| Male | 17 | 9.48 | 0.94 | 2.08 | 32.48 | 0.046 |
| Female | 109 | 8.92 | 1.58 | |||
| LG | ||||||
| Male | 17 | 2.57 | 0.67 | −1.73 | 106 | 0.09 |
| Female | 109 | 2.85 | 0.60 |
Table 4. Descriptive Statistics of Lip Layer Thickness by Race and Ethnicitya
| Layer and Race and Ethnicity | No. | Mean | SD |
|---|---|---|---|
| U | |||
| White | 94 | 1.44 | 0.34 |
| Black | 11 | 1.62 | 0.40 |
| Indian | 8 | 1.59 | 0.44 |
| Asian/Chinese | 8 | 1.33 | 0.14 |
| Mixed | 5 | 1.70 | 0.26 |
| UM | |||
| White | 94 | 1.37 | 0.36 |
| Black | 11 | 1.40 | 0.28 |
| Indian | 8 | 1.34 | 0.35 |
| Asian/Chinese | 8 | 1.51 | 0.41 |
| Mixed | 5 | 1.06 | 0.25 |
| UC | |||
| White | 94 | 1.62 | 0.59 |
| Black | 11 | 1.62 | 0.45 |
| Indian | 8 | 1.73 | 0.60 |
| Asian/Chinese | 8 | 1.53 | 0.28 |
| Mixed | 5 | 1.30 | 0.58 |
| UP | |||
| White | 94 | 1.54 | 0.41 |
| Black | 11 | 1.40 | 0.32 |
| Indian | 8 | 1.57 | 0.27 |
| Asian/Chinese | 8 | 1.57 | 0.30 |
| Mixed | 5 | 1.52 | 0.22 |
| UW | |||
| White | 94 | 2.17 | 0.60 |
| Black | 11 | 2.64 | 1.38 |
| Indian | 8 | 2.59 | 0.83 |
| Asian/Chinese | 8 | 2.38 | 0.35 |
| Mixed | 5 | 2.35 | 0.61 |
| UT | |||
| White | 93 | 8.29 | 1.29 |
| Black | 11 | 8.83 | 1.35 |
| Indian | 8 | 8.83 | 1.60 |
| Asian/Chinese | 8 | 8.42 | 0.79 |
| Mixed | 5 | 7.83 | 1.54 |
| UG | |||
| White | 80 | 2.64 | 0.58 |
| Black | 11 | 2.77 | 0.75 |
| Indian | 7 | 2.34 | 0.51 |
| Asian/Chinese | 7 | 3.21 | 0.52 |
| Mixed | 3 | 3.22 | 0.92 |
| L | |||
| White | 94 | 1.61 | 0.40 |
| Black | 11 | 1.75 | 0.37 |
| Indian | 8 | 1.63 | 0.38 |
| Asian/Chinese | 8 | 1.58 | 0.24 |
| Mixed | 5 | 2.23 | 0.77 |
| LM | |||
| White | 94 | 1.44 | 0.40 |
| Black | 11 | 1.58 | 0.53 |
| Indian | 8 | 1.13 | 0.31 |
| Asian/Chinese | 8 | 1.44 | 0.26 |
| Mixed | 5 | 1.34 | 0.35 |
| LC | |||
| White | 94 | 1.86 | 0.62 |
| Black | 11 | 2.09 | 0.64 |
| Indian | 8 | 1.70 | 0.62 |
| Asian/Chinese | 8 | 2.03 | 0.65 |
| Mixed | 5 | 1.60 | 0.33 |
| LP | |||
| White | 94 | 1.62 | 0.44 |
| Black | 11 | 1.52 | 0.39 |
| Indian | 8 | 1.47 | 0.49 |
| Asian/Chinese | 8 | 1.60 | 0.20 |
| Mixed | 5 | 1.88 | 0.49 |
| LW | |||
| White | 94 | 2.23 | 0.60 |
| Black | 11 | 2.54 | 0.57 |
| Indian | 8 | 2.49 | 0.92 |
| Asian/Chinese | 8 | 2.43 | 0.53 |
| Mixed | 5 | 2.40 | 0.78 |
| LT | |||
| White | 94 | 8.96 | 1.42 |
| Black | 11 | 9.30 | 2.48 |
| Indian | 8 | 8.43 | 1.69 |
| Asian/Chinese | 8 | 9.22 | 0.88 |
| Mixed | 5 | 9.47 | 1.56 |
| LG | |||
| White | 80 | 2.77 | 0.59 |
| Black | 11 | 2.98 | 0.78 |
| Indian | 7 | 2.34 | 0.25 |
| Asian/Chinese | 7 | 3.26 | 0.43 |
| Mixed | 3 | 3.31 | 0.77 |
BMI was significantly positively correlated with increased lip thickness in the subcutaneous layer ( P = 0.01), connective tissue ( P = 0.03), and wet mucosa ( P = 0.04) layers, as well as with Fitzpatrick skin type ( P = 0.001), but not with lip fullness. Age was significantly inversely correlated with total lip thickness ( P = 0.02) and lip fullness ( P = 0.01). Skin type and lip fullness were both significantly positively correlated with several individual layers, including the connective tissue ( P = 0.01) and wet mucosa ( P = 0.01). ( See Table, Supplemental Digital Content 2 , which shows correlations between lip layer thickness and BMI, age, skin type, lip fullness, and recent botulinum toxin use, https://links.lww.com/PRS/I549.)
Participants who had received recent lower face botulinum toxin injections demonstrated significantly reduced thickness in the lower lip connective tissue ( P = 0.03) and subcutaneous layers ( P = 0.04), suggesting potential structural effects of neuromodulator treatment.
Lip type 1A was the most common, comprising 67.5% of the sample. Significant thickness differences were observed across lip types, with type 3A exhibiting greater upper lip connective tissue thickness compared with other ( P < 0.001), and type 2A showing significantly greater muscular thickness than type 3A ( P = 0.001). Type 1A also demonstrated greater UC thickness compared with other ( P = 0.04). ( See Table, Supplemental Digital Content 3 , which shows lip layer thickness by Lip Classification of Tubercles type. Bonferroni post hoc analysis indicated that the 3A lip type exhibited significantly greater UC thickness compared with other lip types [ P < 0.001], and the 2A lip type demonstrated significantly greater LM thickness compared with the 3A lip type [ P = 0.001]. A significant difference in UC thickness was also observed between 1A and other lip types [ P = 0.04], https://links.lww.com/PRS/I550.)
Treated patients demonstrated significantly greater thickness in the following layers compared with untreated patients: connective tissue of the upper lip ( P = 0.04), pars peripheralis of the upper lip ( P = 0.003), connective tissue layer of the lower lip ( P = 0.01), and pars peripheralis of the lower lip ( P = 0.01). In contrast, the wet mucosal layer of the upper lip was significantly thicker in untreated patients ( P = 0.02). ( See Table, Supplemental Digital Content 4 , which shows a comparison of lip layer thickness in treated versus untreated patients. Descriptive statistics reflect layer thickness differences between treated and untreated patients. Independent samples t tests revealed significantly thicker layers in treated patients for UC [t(85.65) = −2.06, P = 0.04], UP [t(79.92) = −3.01, P = 0.003], LC [t(124) = −2.85, P = 0.01], and LP [t(124) = −2.57, P = 0.01]. In contrast, untreated patients exhibited significantly greater thickness in the UW layer [t(124) = 2.35, P = 0.02], https://links.lww.com/PRS/I551.)
Filler volume and time were positively correlated with thickness in several lip layers, especially UC, UM, and UT ( P < 0.001). Spread and hypervascularity also correlated with thickness across layers and were strongly associated with filler type, injection technique, and hypervascularity presence ( P < 0.001). ( See Table, Supplemental Digital Content 5 , which shows associations between lip layer thickness and filler-related variables, including filler type, amount, injection technique, spread, and hypervascularity, https://links.lww.com/PRS/I552. See Figure, Supplemental Digital Content 6 , which shows frequency of filler spread by filler type, https://links.lww.com/PRS/I553. See Figure, Supplemental Digital Content 7 , which shows frequency of filler spread by injection technique, https://links.lww.com/PRS/I554. See Figure, Supplemental Digital Content 8 , which shows frequency of filler spread by presence of hypervascularity, https://links.lww.com/PRS/I555.)
Filler was frequently identified in the pars marginalis, reflecting unintentional intramuscular deposition, most strongly linked to vertical injections. Spread occurred in 52% of treated patients (27 of 52) and was significantly more common with vertical (73% [22 of 30]) than horizontal injections (24% [5 of 21]; Fisher exact test; odds ratio 8.8; P = 0.0007); here, spread denotes displacement of filler beyond the intended injection site. With respect to the layers involved, vertical cases always crossed multiple layers, most commonly SC + PM, whereas among NLT horizontal injections, filler was confined to the SC layer in 20% of cases and present in both the SC and PM layers in 80%, with none extending beyond 2 layers.
This ultrasound-based investigation provides novel insights into the structural changes in lip anatomy associated with HA filler treatment, demographic variation, and injection technique. The findings highlight both predictable and unintended outcomes of aesthetic lip augmentation, with implications for safety, personalization, and technique refinement.
The moderate to excellent intrarater reliability across most lip layer measurements supports the utility of high-frequency ultrasound as a dependable modality for evaluating lip anatomy. However, lower reliability for certain upper lip and glandular measures highlights the importance of standardizing probe positioning and reinforcing training for clinicians using ultrasound in aesthetic practice. 8 , 9
Patients with previous filler treatment demonstrated significantly greater thickness in the connective tissue, pars peripheralis, and total lip regions. These findings reflect structural augmentation resulting from HA deposition and subsequent tissue remodeling. 10 Conversely, untreated patients showed thicker wet mucosa, suggesting that natural anatomical variability may influence both aesthetic goals and response to treatment. Understanding baseline anatomy is therefore essential for individualized planning.
Variations in submucosal gland dimensions were observed, with evidence of enlargement in treated patients, especially in association with deeper injection techniques and spread. These findings raise clinical considerations regarding lip hydration, edema, and potential gland-related complications. Previous reports of subclinical inflammation in lacrimal and salivary glands among filler users support the need for vigilance when injecting near mucosal structures. 11
All injection techniques resulted in intramuscular filler placement, regardless of intended depth. Horizontal techniques (eg, NLT) produced more localized, superficial deposition within the subcutaneous or pars marginalis layers, without spread beyond the vermilion border. In contrast, vertical techniques (eg, tenting, “Russian lip”) were linked to deeper, multilayered deposition, hypervascularity, and glandular changes.
Filler was frequently detected in the pars marginalis, reflecting the trajectory of vertical vectors, with ultrasound confirming expansion along muscle fibers. This supports a technique-dependent, not volume-driven, process (Fig. 4 ).
Doppler imaging was used to identify hypervascularity associated with filler placement. Previous studies have already described labial artery anatomy in detail. 13 Although lidocaine may contribute to transient vasodilation, the persistent hypervascularity observed months after injection is more consistent with trauma- or filler-related proinflammatory effects, and possible vascular remodeling from repeated injection or overfilling.
Although injector practice varies in terms of filler rheology, syringe size, needle gauge, and injection pressure, our findings remain broadly applicable. Filler was frequently identified in the pars marginalis regardless of product or device, underscoring that technique selection and anatomical awareness are the key determinants of placement. These results are therefore relevant to all injectors, independent of product choice or instrumentation.
The study also identified clear associations between filler type and the likelihood of product spread. Certain HA formulations were more frequently associated with diffusion beyond intended planes, potentially due to rheologic properties such as G′ and cohesivity. 12 , 14 This finding suggests that product selection, in addition to technique, plays a significant role in controlling filler localization and minimizing complications.
Sex differences were significant, with men exhibiting greater total lip thickness, particularly in the upper lip wet mucosa, total upper lip thickness, and total lower lip thickness. Race and ethnicity differences also emerged: participants with mixed race had greater lip layer thickness than White participants, and Asian/Chinese participants had thicker glandular layers than Indian participants. These differences emphasize the need for racially and ethnically sensitive, sex-aware aesthetic planning. 10
BMI was positively correlated with several lip layers, particularly the wet mucosa, suggesting that individuals with higher body mass may have naturally fuller lips. In contrast, age was inversely related to multiple lip layers, indicating structural decline with aging. These observations are consistent with clinical patterns of perioral volume loss and reinforce the need to factor both age and BMI into treatment strategy. 8 , 10
Lip fullness scores were positively associated with multiple anatomical layers, especially the connective tissue and mucosal regions. These results support the volumizing effect of HA fillers and offer insight into how anatomical targets may be prioritized depending on the desired aesthetic outcome. 11
A negative correlation between recent botulinum toxin use and connective tissue thickness in the lips suggests a possible interaction between neurotoxin treatments and structural lip volume. This finding warrants further investigation, but it raises interesting questions about the sequencing and combined use of neuromodulators and fillers in the lower face. 15
The lower lip was significantly thicker than the upper lip across nearly all layers, with the wet mucosa showing the greatest difference. This anatomical insight supports the standard practice of preserving or enhancing the natural 1:1.6 upper to lower lip ratio in aesthetic design. 10 , 12
Lip type 1A was most prevalent in the sample, consistent with common aesthetic ideals. However, significant thickness differences among types—such as greater connective tissue in type 3A and greater muscular layer thickness in type 2A—reinforce the relevance of lip classification systems in clinical planning.
In clinical practice, high-frequency ultrasound has been assimilated both as an evaluation tool (for filler localization, migration, and vascularity) and as a guidance tool in high-risk anatomical zones. Expertise with the device was acquired over several months of structured training and daily clinical use, after which it became integral to treatment planning and complication management.
The routine use of ultrasound in every lip filler procedure may not be feasible, but the increasing accessibility of portable high-frequency devices and structured training is making this technology more practical. Ultrasound should be considered particularly valuable for complex cases, revision treatments, and complication management, rather than as a mandatory tool for all procedures. In this context, our findings highlight how ultrasound can enhance anatomical understanding, improve safety, and inform personalized treatment planning.
Several limitations must be acknowledged. Although balanced across treatment groups, the overall sample size was modest. Broader demographic representation, particularly across groups with diverse race and ethnicity, would enhance generalizability.
The distribution of participants across race and ethnicity subgroups was unbalanced, with some groups represented by only a few individuals. Therefore, subgroup findings should be considered exploratory rather than definitive.
The cross-sectional design limits inference of causality. Although treated and untreated patients were compared, preexisting anatomical variation and demographic influences may also contribute to observed differences. Longitudinal studies are required to confirm causal relationships.
Ultrasound is inherently operator-dependent, and multiple devices were used in this study. However, all investigators were experienced, a standardized protocol was followed, and intrarater reliability testing confirmed measurement consistency, making systematic bias unlikely.
Common techniques were grouped for analysis, but individual injector variation and undocumented modifications may influence results.
Lifestyle, hydration, and skin quality were not assessed, but may affect lip anatomy and filler behavior.
The study focused on anatomical rather than perceptual outcomes. Future work should incorporate satisfaction and aesthetic assessments to bridge structural findings with clinical relevance.
Potential confounding factors, such as smoking, hydration status, hormonal fluctuations, and history of oral procedures, were not recorded. These may influence lip thickness and vascularity and should be considered in future studies.
This study provides the first high-resolution ultrasound-based evidence of consistent intramuscular filler deposition in the lips, regardless of injection depth or technique. The subcutaneous layer is too thin to reliably contain filler, leading to unintentional spread into the pars marginalis.
Vertical vector injection techniques result in greater filler migration, hypervascularity, and glandular changes, whereas conservative methods involving horizontal vector techniques demonstrate more predictable and safer outcomes.
These findings establish a normative reference for lip anatomy and support the use of ultrasound in treatment planning. Personalized injection strategies informed by anatomical variation and ultrasound imaging can improve both safety and aesthetic results.
Dr. Schelke and Dr. Velthuis are shareholders in Cutaneous BV, a company that provides educational courses and materials for facial ultrasound imaging. Dr. Wortsman is a speaker for UCB and Novartis and a consultant for Galderma. Prof. Cotofana is the chief executive officer of Cotofana Anatomy Corp., a company that specializes in anatomic education. The remaining authors have no financial interests to disclose.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
背景:玻尿酸(HA)唇部填充常见,但其引起的解剖改变及与人口学因素的关系尚不充分。
背景:玻尿酸(HA)等填充剂注射后的「移位 / 扩散」并非随机,既往缺乏对其走向规律的影像学证据。
研究设计:意大利团队提出的三层(深层脂肪、浅层脂肪、真皮皮下层)超声引导中面部年轻化技术,属观察性/概念验证研究;15 例患者(13 女 2 男,50±8 岁,范围 42-65 岁