隧道式深层平面提升术矫正下面部与颈部松弛的回顾性队列研究
2026年10月19日28 min read
Plastic and Reconstructive Surgery Global Open
Plastic and Reconstructive Surgery Global Open
结论与实践要点
TDL是一种整合深层平面技术与SMAS/颈阔肌折叠悬吊的隧道式面部颈部提升,目标为矫正下面部与颈部松弛、维持V形下颌轮廓。其机制基于在第四层(低血管化)内隧道式游离,于实时最易活动的组织点进行深部组织复位与折叠,减少术区组织扰动与出血,并规避面神经分支、耳大神经及颈部大血管/淋巴管损伤风险;辅以皮下射频通过热效应(40–84°C)促进成纤维细胞分化与新胶原生成,改善皮肤松弛。
属单中心回顾性队列(样本n=93,单一术者),证据等级有限,结论外推需谨慎。原文称「无并发症」优于文献报道的对照技术并发症率,但该比较非同期、非随机,不能直接推导TDL安全性绝对占优。随访上限1年,缺乏>2年数据;术者自订松弛量表与FACE-Q(满意度变化显著,P<0.001)并用,但美学改善的主要依据为照片与量表,未提供盲法评估。原文未提供统一的术中出血量、住院时长及费用数字;是否适用于非 Hispanic/White人群亦未论证。
Background:Facial and neck lift procedures are gaining relevance worldwide, as patients have an increasing interest in maintaining a youthful appearance and reversing facial aging changes; this has led to the development of the tunneled deep-plane lift (TDL), a surgical intervention that corrects laxity of the lower third of the face and the neck.
Methods:A retrospective study of the TDL technique was conducted among patients in Colombia with a follow-up of 1 year. To assess the aesthetic and morphological changes, we compared the facial and neck laxity scale results before and after surgery; we also measured the excess skin after the suspension of the superficial muscular aponeurotic system and platysma; procedure satisfaction was evaluated through FACE-Q scale results.
Results:Among 93 patients, the average age was 52.9 years. Preoperatively, patients had facial laxity of grade 4 (52.68%) and grade 3 (32.25%), and neck laxity of grade 2 (50.53%) and grade 3 (38.70%); after the procedure, patients’ facial and neck laxity improved to grade 1 in most cases (80%).
Conclusions:TDL is a technique that corrects laxity of the lower third of the face and the neck. This approach manipulates deep facial tissues using the deep-plane technique and involves plication of the superficial muscular aponeurotic system and platysma, providing immediate and noticeable results that are sustained for up to 1 year. The technique is suitable for patients aged 30–50 years, and the adjunctive use of subdermal radiofrequency enhances results by improving laxity and signs of skin aging.
Question: Can the tunneled deep-plane lift (TDL) safely and effectively correct lower facial and neck laxity in patients across different age groups?
Findings: In this retrospective cohort of 93 patients with a 1-year follow-up, TDL improved facial and neck laxity in most patients, with grades improving from 3 to 4 preoperatively to grade 1 postoperatively. Patient-reported satisfaction increased significantly (FACE-Q, 14.2–85.1; P < 0.001), with no reported complications.
Meaning: TDL provides a safe, reproducible, and durable option for lower facial and neck rejuvenation, combining deep-plane and plication principles to achieve high patient satisfaction.
Facial and neck lift procedures are currently gaining significant relevance in the practice of aesthetic plastic surgery. According to the results of the International Society of Plastic Surgery survey conducted for the year 2022, face lift procedures rank 11th, and neck lift procedures rank 12th among the most common procedures performed by plastic surgeons worldwide, and the annual volume of both has grown by more than 30% during the past 5 years. 1 It is important to note that these procedures are surpassed only by various body contouring procedures and rhinoplasty, highlighting the growing popularity and demand for these facial surgery techniques among patients.
Aesthetic facial surgery traces its origins to the early 20th century, with Eugene von Hollander performing the first rhytidectomy in 1901 and Lexter describing his face lift technique in 1906, both aimed at minimizing the effects of aging by repositioning soft tissues to achieve a more youthful orientation. 2 , 3 The demand for aesthetic and reconstructive facial surgery increased following the World Wars due to the injuries sustained during these conflicts; in 1970, with advances in the understanding of facial anatomy, Skoog performed the first facial procedures that involved deep fascial tissues; in 1976, Mitz and Peyronie coined the term “superficial muscular aponeurotic system (SMAS),” an anatomical region central to many of the techniques used today; in 1989, Furnas described the function of the midface ligaments and the role they play in aging. 3
Regarding face lift techniques for the lower third of the face and neck, the deep-plane face lift and SMAS plication face lift are the most commonly used surgical procedures for these areas. There is ongoing debate about which technique is superior. 4 Plication techniques involve the in-folding of the SMAS and suture suspension without any SMAS incision, whereas the deep-plane face lift involves undermining the skin–SMAS flap as a single unit, following a more limited subcutaneous dissection. 5 Both techniques have demonstrated similar effectiveness in patients aged 50–70 years, but the deep-plane face lift shows better results in patients older than 70 years. 4
Today, patients are increasingly interested in maintaining a youthful appearance and wish to reverse facial changes that occur with aging at an earlier age (between 30 and 40 y). They frequently turn to nonsurgical and surgical measures to fulfill this need. It is observed that 72% of nonsurgical procedures in plastic surgery are focused on reversing facial aging, and surgical interventions account for 8% of the total aesthetic procedures. 1 Most patients who reach the surgical stage have previously undergone nonsurgical procedures such as threads, fillers, collagen inducers, ultrasound, radiofrequency, or polymers, which produce a significant degree of subdermal and/or intermediate-plane fibrosis or scarring, such as in the facial aponeurosis (SMAS) or neck (platysma), thereby potentially limiting the surgical procedure, its dissection, or approach.
This new technique, the tunneled deep-plane lift (TDL), emerges as a method that combines the benefits of the deep-plane face lift and the SMAS plication face lift. It focuses on achieving natural results with minimal incisions and is applicable to younger individuals. This article aims to demonstrate this new technique and its outcomes.
A retrospective observational cohort study was conducted, using data obtained from the medical records of Dr. Nora Stanford, the pioneer of the TDL. The study covered the period from 2023 to 2025.
The study population consisted of all patient records from Dr. Nora Stanford’s practice in Barranquilla, Colombia, who underwent the TDL between June 2023 and July 2025, and had at least 1 year of follow-up. All patients underwent presurgical assessments to determine eligibility for the TDL procedure. Eligibility criteria included a body mass index of less than 29 kg/m 2 in men and 28 kg/m 2 in women, nutritional education focused on healthy nutrition, and a psychological evaluation regarding their own facial appearance. Patients were excluded if they required a full face lift, defined as facial laxity of grade 3 or higher plus at least one of the following criteria: brow ptosis greater than 5 mm, a negative malar excursion test, or neck laxity of grade 3 or higher. Additional exclusion criteria included the need for bone modification surgery, active smoking (failure to quit smoking at least 1 mo before surgery), or a medical history of connective tissue disease.
Data for this study were extracted from the patient database of Dr. Nora Stanford. The operational database included the following variables:
Table 1. Facial Laxity Scale
| Grade | Description |
|---|---|
| Grade 1 | Nasolabial folds faintly visible at the alar bases or extended up to one-third of their length |
| Grade 2 | Nasolabial folds visible along their entire length to the labial commissure |
| Grade 3 | Marionette lines and jowls |
| Grade 4 | Marionette lines, jowl descent, and facial tissue descent below the mandibular line |
Table 2. Neck Laxity Scale
| Grade | Description |
|---|---|
| Grade 1 | Laxity confined to the submental triangle, cricoid cartilage, or upper neck |
| Grade 2 | Laxity or skin flap with the lower edge reaching the thyroid cartilage, usually corresponding to the mid-neck |
| Grade 3 | Laxity or skin flap reaching the clavicular line or low neck |
| Grade 4 | Skin flap extending beyond the clavicular line outside the cervical area |
Table 3. Treatments of Facial and Neck Laxity Based on the Scale
| Grade | Description |
|---|---|
| Grade 1 | Managed with monopolar subdermal radiofrequency treatment for facial toning, with or without contouring or liposuction of the lower third of the face and neck |
| Grades 2–3 | Managed with TDL focused on the lower third of the face and mid-neck |
| Grade 4 | Managed with extended TDL to the middle third of the face, with minimal movements, and full neck involvement |
This technique is described step by step in Supplemental Digital Content 1, and the technique can also be seen in a real patient in Video 1 or in a 3-dimensional animation in Video 2. ( See Video 1 [online] , which demonstrates the TDL technique performed in a real patient, illustrating the complete surgical workflow.) ( See Video 2 [online] , which provides a 3-dimensional conceptual overview of the TDL. The animation illustrates the anatomical planes involved in the procedure.) ( See table, Supplemental Digital Content 1 , which describes a structured step-by-step overview of the TDL technique, https://links.lww.com/PRSGO/F112.)
补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)gox-14-e7987-s001.mp4Video 1. This video demonstrates the Tunneled Deep Plane Lift (TDL) technique performed in a real patient, illustrating the complete surgical workflow.补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)gox-14-e7987-s002.mp4Video 2. This animated video provides a three-dimensional conceptual overview of the Tunneled Deep Plane Lift (TDL). The animation illustrates the anatomical planes involved in the procedure
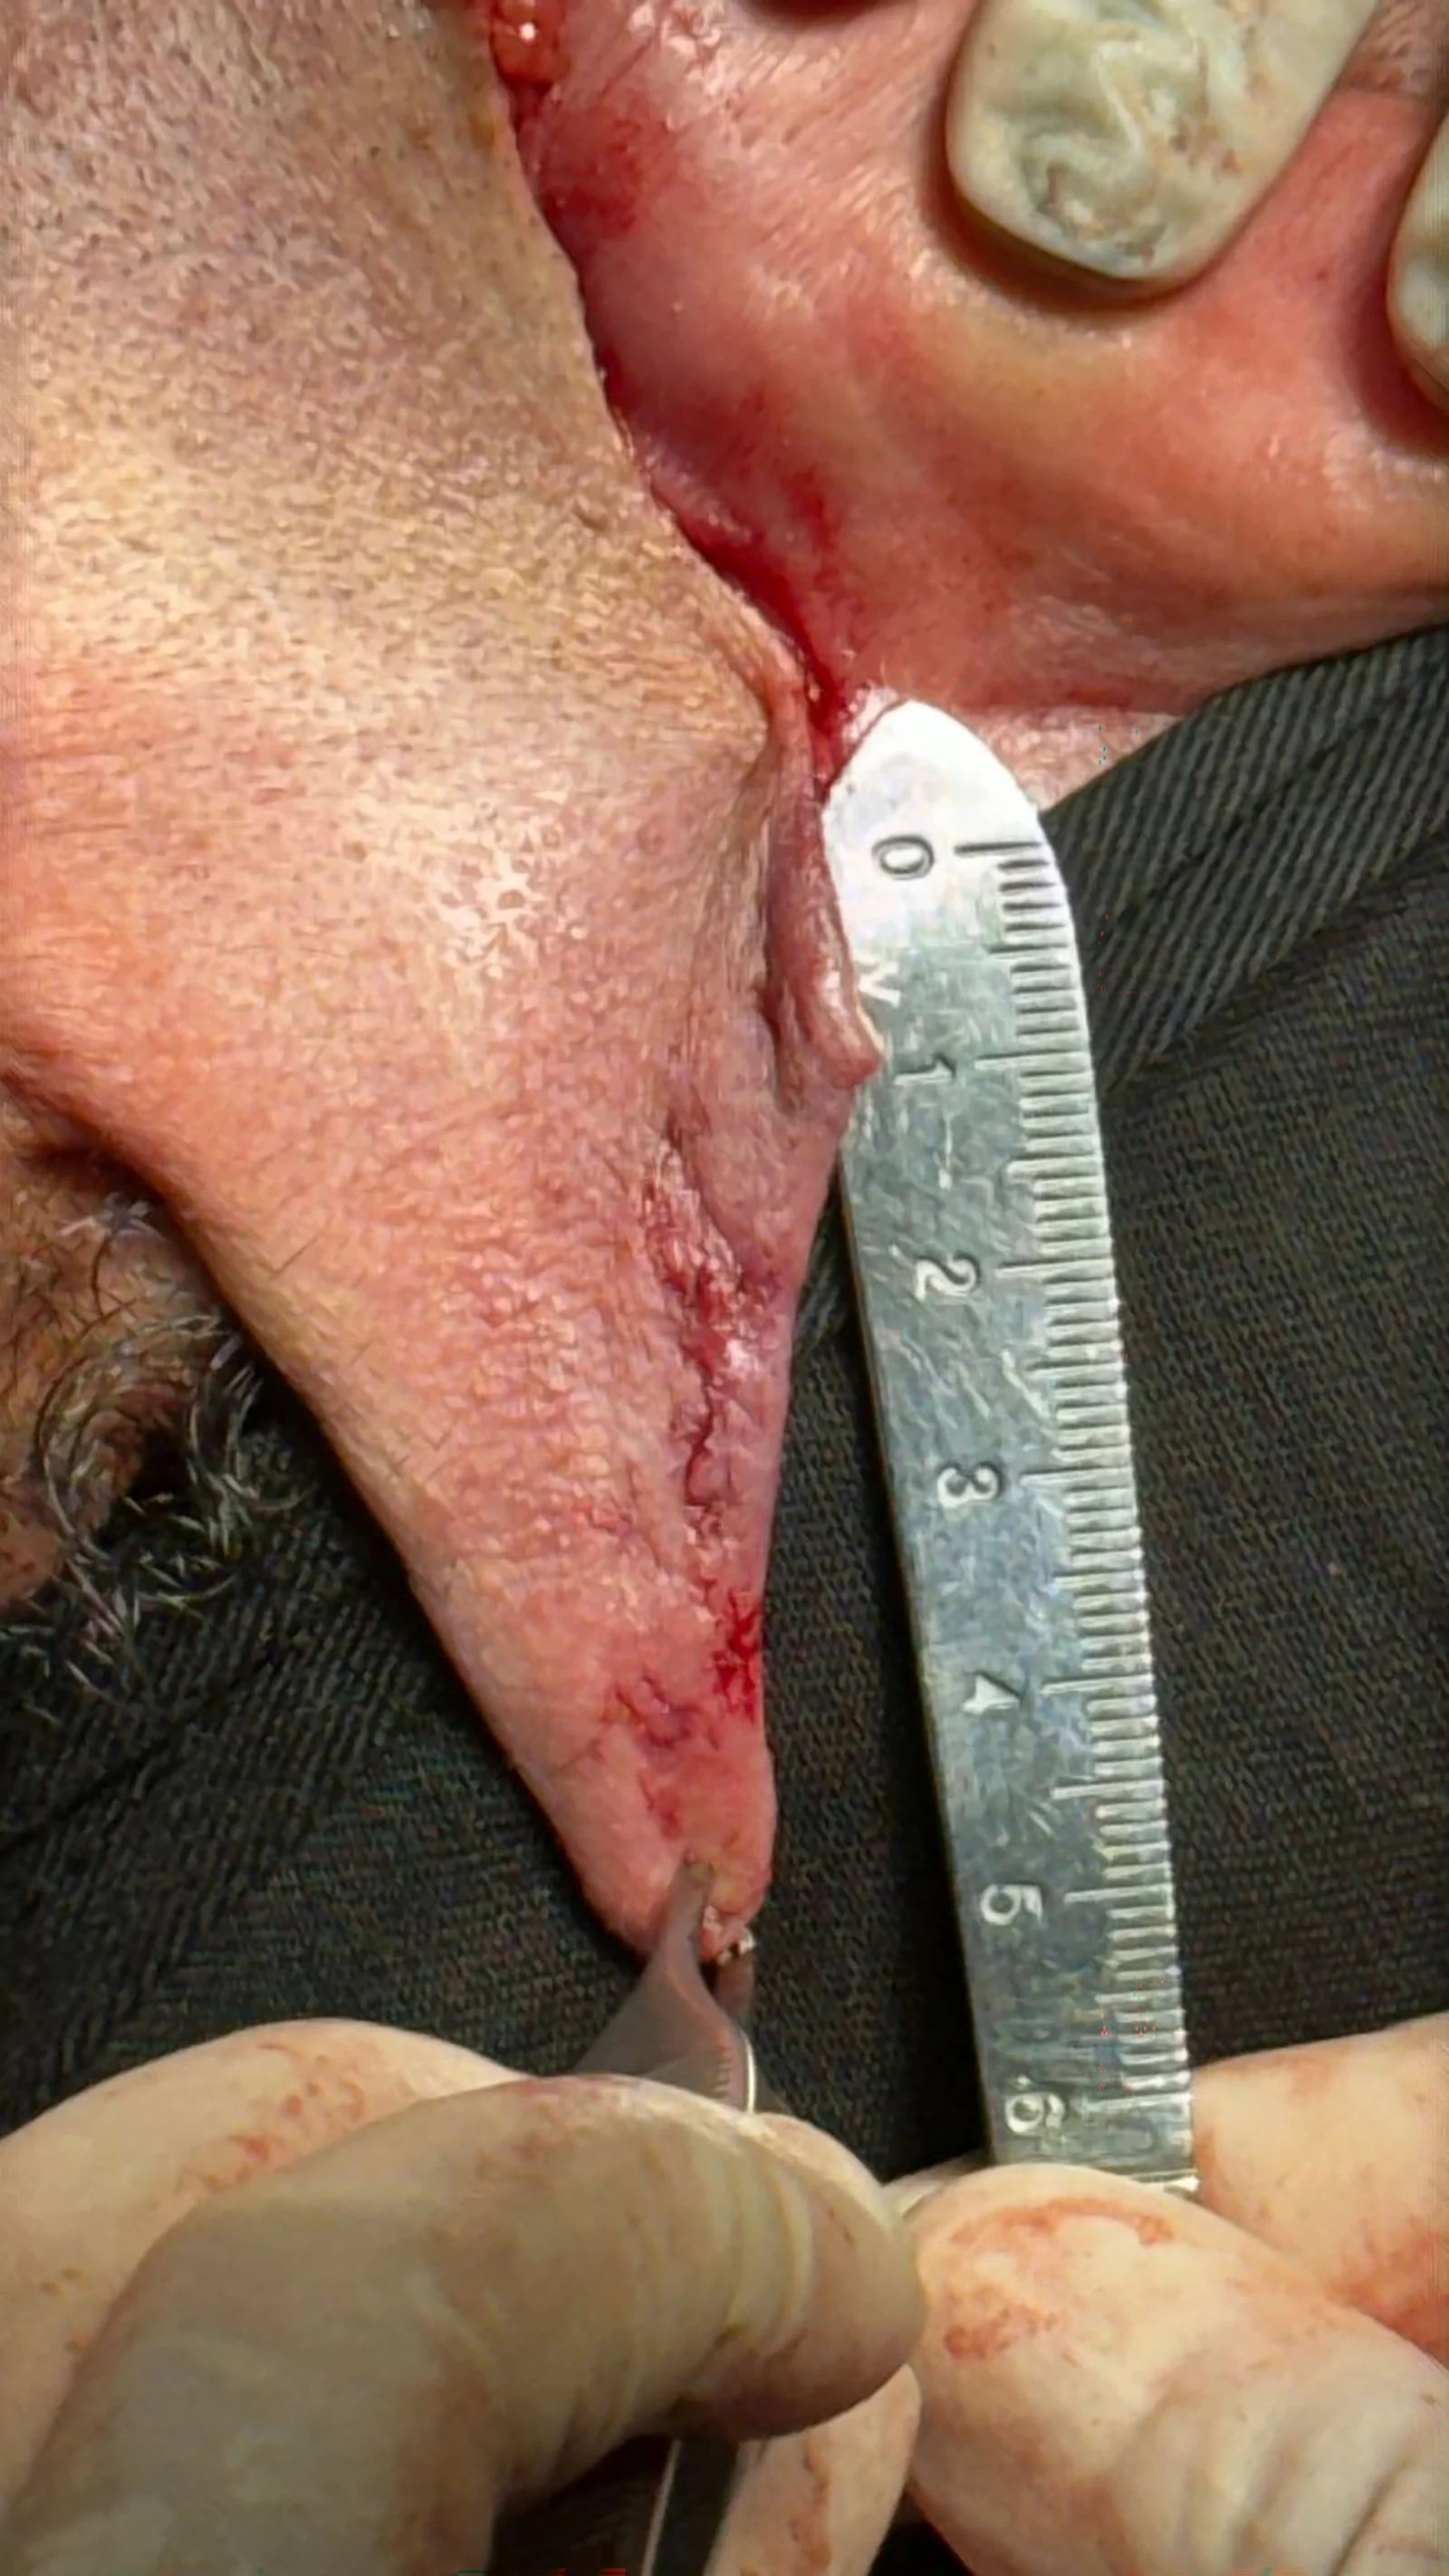
To assess the aesthetic and morphological changes resulting from the intervention, we compared the facial and neck laxity scale results before and after the surgery. We also measured the excess skin after suspension of the SMAS and platysma (Fig. 1 ) as evidence of the block displacement of the fascial tissues. Procedure satisfaction was evaluated through differences observed in FACE-Q scale results (presurgery versus postsurgery).
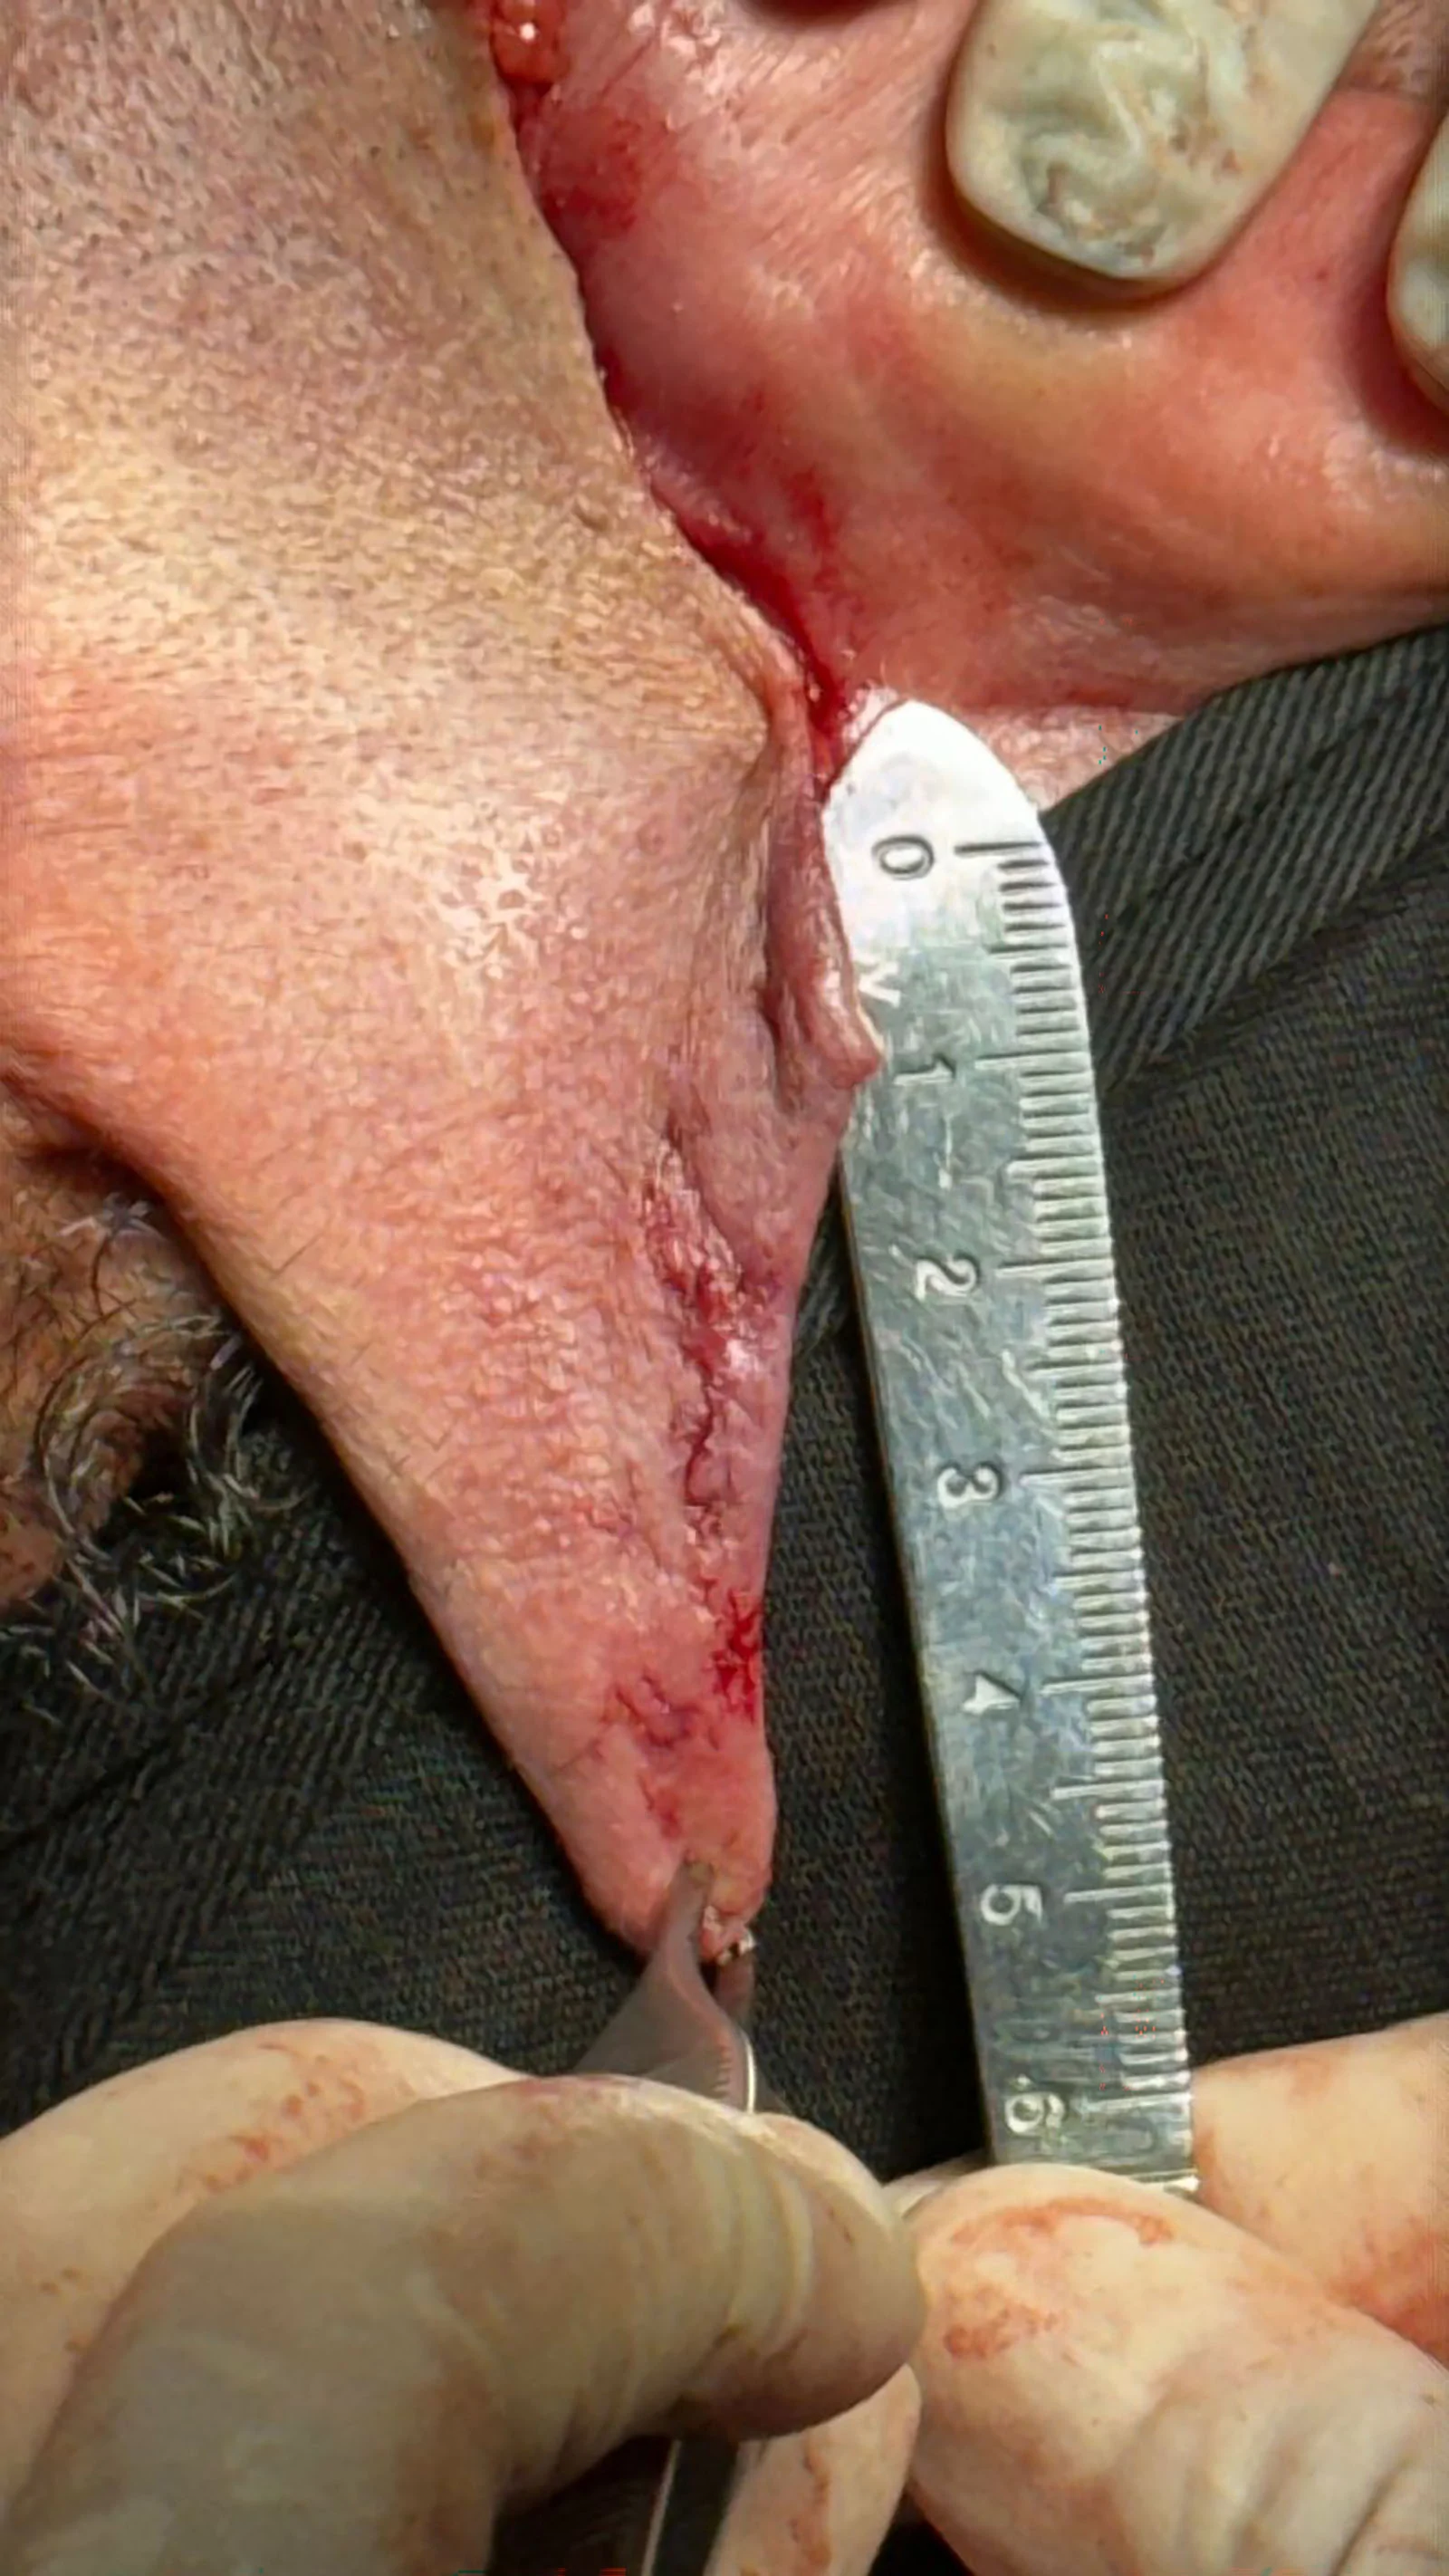
Fig. 1. Measurement of excess skin. This photograph displays the retroauricular region to show the residual skin after the TDL procedure.
Informed consent for surgical procedure, use of images, and use of data for research was signed before surgery by each patient; participants were informed that they could refuse to participate in the study or to withdraw consent to participate at any time. This research was conducted in accordance with the Declaration of Helsinki.
Descriptive statistics were used to show the patient information results. To demonstrate differences between preoperative and postoperative measures, the Student t test was used. The level of significance for the P value was less than 0.05. Jamovi statistical software (The jamovi project, Australia; version 2.5; retrieved from https://www.jamovi.org) was used for both univariate and multivariate analyses.
A sample of 93 patients was obtained, with a mean age of 52.9 years (SD 8.13 y) and a mean body mass index of 26.8 kg/m 2 (SD, 1.4 kg/m 2 ). Regarding sex, 85 patients were women (90%), and 8 patients were men (10%); the ethnicity of the patients was mostly Hispanic (76%), and the rest of the patients were White (24%) (Table 4 ).
Table 4. Demographic Characteristics
| Variable | Measure of Central Tendency or % | Dispersion Measurement |
|---|---|---|
| Age, y | Mean: 52.9 | SD: 8.13 |
| Sex, n (%) | Total: 93 | NA |
| Female | 85 (91.39) | |
| Male | 8 (8.60) | |
| BMI, kg/m 2 | Mean: 26.8 | SD: 1.4 |
| Ethnicity, n (%) | Total: 93 | NA |
| Hispanic | 76 (81.72) | |
| White | 17 (18.27) |
Of the 93 patients, 41 individuals (64%) were reported to have a medical history, with a total of 62 diagnoses. The most common conditions found were dyslipidemia (27.41%), hypothyroidism (25.8%), and hypertension (17.74%) (Table 5 ). Additionally, 36 subjects (38.70%) reported having undergone previous facial procedures, with a total of 50 surgical interventions in the facial region. The most frequent procedures were blepharoplasty (38%), rhinoplasty (36%), and face lift (12%). However, only 14 (15.05%) patients had undergone surgery involving the lower third of the face before TDL (Table 5 ).
Table 5. Patient Medical History
| Variable | Measure of Central Tendency or % |
|---|---|
| Medical history, n (%) | Total: 93 |
| Yes | 41 (44.08) |
| No | 52 (55.91) |
| Medical diagnoses, n (%) | Total: 62 |
| Dyslipidemia | 17 (27.41) |
| Hypothyroidism | 16 (25.80) |
| Hypertension | 11 (17.74) |
| Gastritis | 4 (4.25) |
| Aneurism | 1 (1.61) |
| Anxiety | 1 (1.61) |
| Arthrosis | 1 (1.61) |
| Crohn disease | 1 (1.61) |
| Eclampsia | 1 (1.61) |
| Endometriosis | 1 (1.61) |
| Facial paralysis | 1 (1.61) |
| Headache | 1 (1.61) |
| Hemorrhoids | 1 (1.61) |
| Hypoglycemia | 1 (1.61) |
| Hypotension | 1 (1.61) |
| Kidney stones | 1 (1.61) |
| Leucopenia | 1 (1.61) |
| Mitral valve prolapse | 01 (1.61) |
| Face surgery (patients), n (%) | Total: 93 |
| Yes | 36 (38.70) |
| No | 57 (61.29) |
| Facial surgery (previous procedures), n (%) | Total: 50 |
| Blepharoplasty | 19 (38) |
| Rhinoplasty | 18 (36) |
| Facial lifting | 6 (12) |
| Chin surgery | 4 (08) |
| Eye surgery | 2 (04) |
| Neck lifting | 1 (02) |
Regarding previously performed nonsurgical procedures on the patients’ faces, it was found that 3 of 93 patients had received facial fillers, 18 of 93 had undergone thread lifts, and 58 of 93 had received Botox injections. Thus, 71 of 93 (76.34%) patients had undergone a nonsurgical facial rejuvenation procedure (Table 6 ).
Table 6. Patient Facial Nonsurgical Procedures
| Variable | Measure of Central Tendency or % |
|---|---|
| Facial filler, n (%) | Total: 93 |
| Yes | 3 (3.22) |
| No | 90 (96.77) |
| Tension threads, n (%) | Total: 93 |
| Yes | 18 (19.35) |
| No | 75 (80.64) |
| Botox, n (%) | Total: 93 |
| Yes | 58 (62.36) |
| No | 35 (37.63) |
| Any nonsurgical procedure, n (%) | Total: 93 |
| Yes | 71 (76.34) |
| No | 22 (23.65) |
Regarding the surgical procedure, the average duration was 298 minutes (SD 29 min). All patients underwent general anesthesia. Preoperatively, most patients had facial laxity of grade 4 (52.68%) and grade 3 (32.25%), and neck laxity of grade 2 (50.53%) and grade 3 (38.70%). After the procedure, most patients improved to grade 1 on facial and neck laxity scales (Figs. 2 – 5 ). The mean amount of excess skin was 3.1 cm, and no patients experienced complications (Table 7 ).
Table 7. Surgical and Clinical Information
| Variable | Measure of Central Tendency or % | Dispersion Measurement |
|---|---|---|
| Surgical time, min | Mean: 298 | SD: 29 |
| Anesthesia, n (%) | Total: 93 | NA |
| General | 93 (100) | |
| Local | 0 (0) | |
| Facial laxity scale, n (%) | Presurgery; total: 93 | Postsurgery; total: 93 |
| 1 | 2 (2.15) | 76 (81.72) |
| 2 | 12 (12.90) | 17 (18.27) |
| 3 | 30 (32.25) | 0 (0) |
| 4 | 49 (52.68) | 0 (0) |
| Neck laxity scale, n (%) | Presurgery; total: 93 | Postsurgery; total: 93 |
| 1 | 1 (1.07) | 74 (79.56) |
| 2 | 47 (50.53) | 19 (20.43) |
| 3 | 36 (38.70) | 0 (0) |
| 4 | 09 (09.67) | 0 (0) |
| Excess skin after the suspension, cm | Mean: 3.1 | SD: 1.43 |
| Complications, n (%) | Total: 50 | NA |
| Yes | 0 (0) | |
| No | 93 (100) |
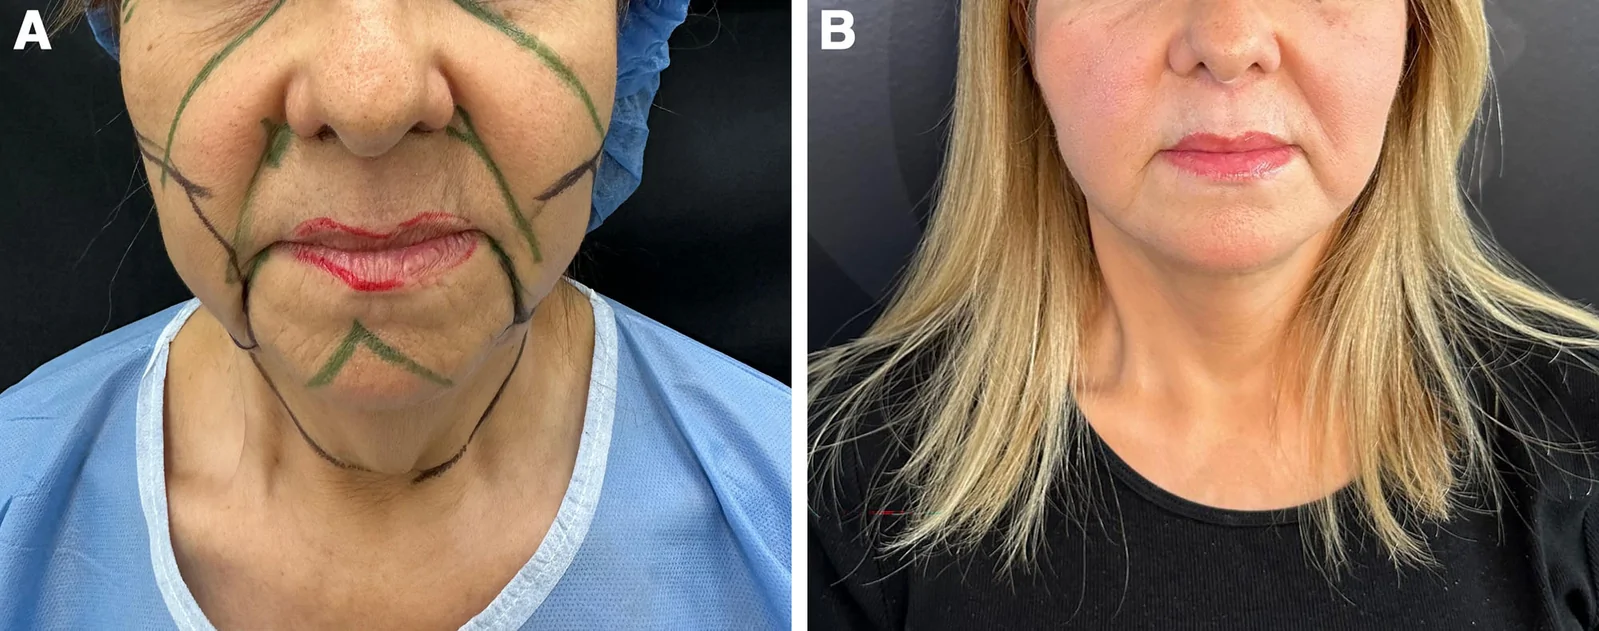
Fig. 2. Female patient 1. A, Preoperative frontal view. B, One‑year comparison shows elimination of marionette folds, platysmal banding, and lower face skin laxity with preservation of natural facial expression.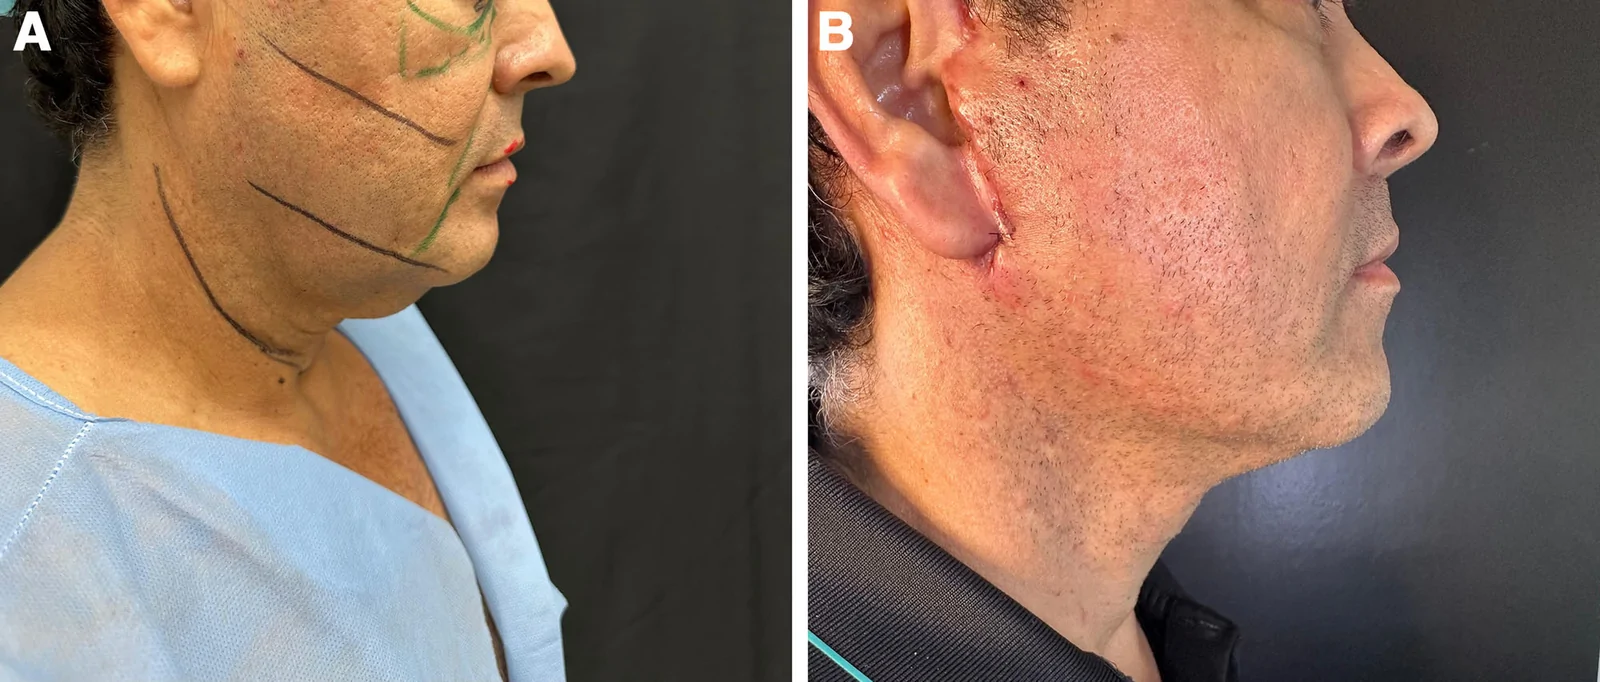
Fig. 3. Male patient 1. A, Preoperative right‑lateral view. B, Twelve‑month postoperative image revealing marked improvement of the jawline, submental fullness, and neck skin redundancy following the TDL and platysma suspension.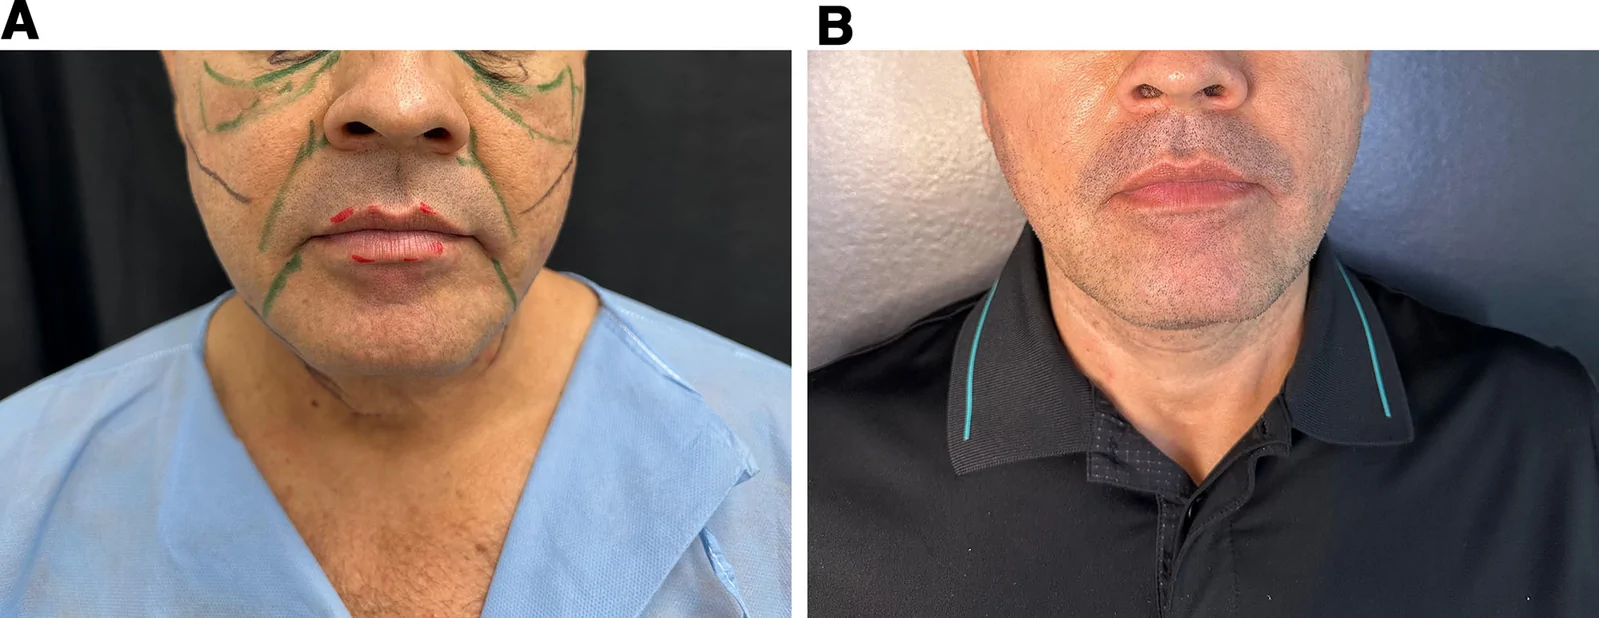
Fig. 4. Same patient as in Figure 3. A, Preoperative frontal view. B, At 1-year follow-up, lower face tightening and reduction of the labiomandibular folds are evident, with maintenance of normal male facial proportions.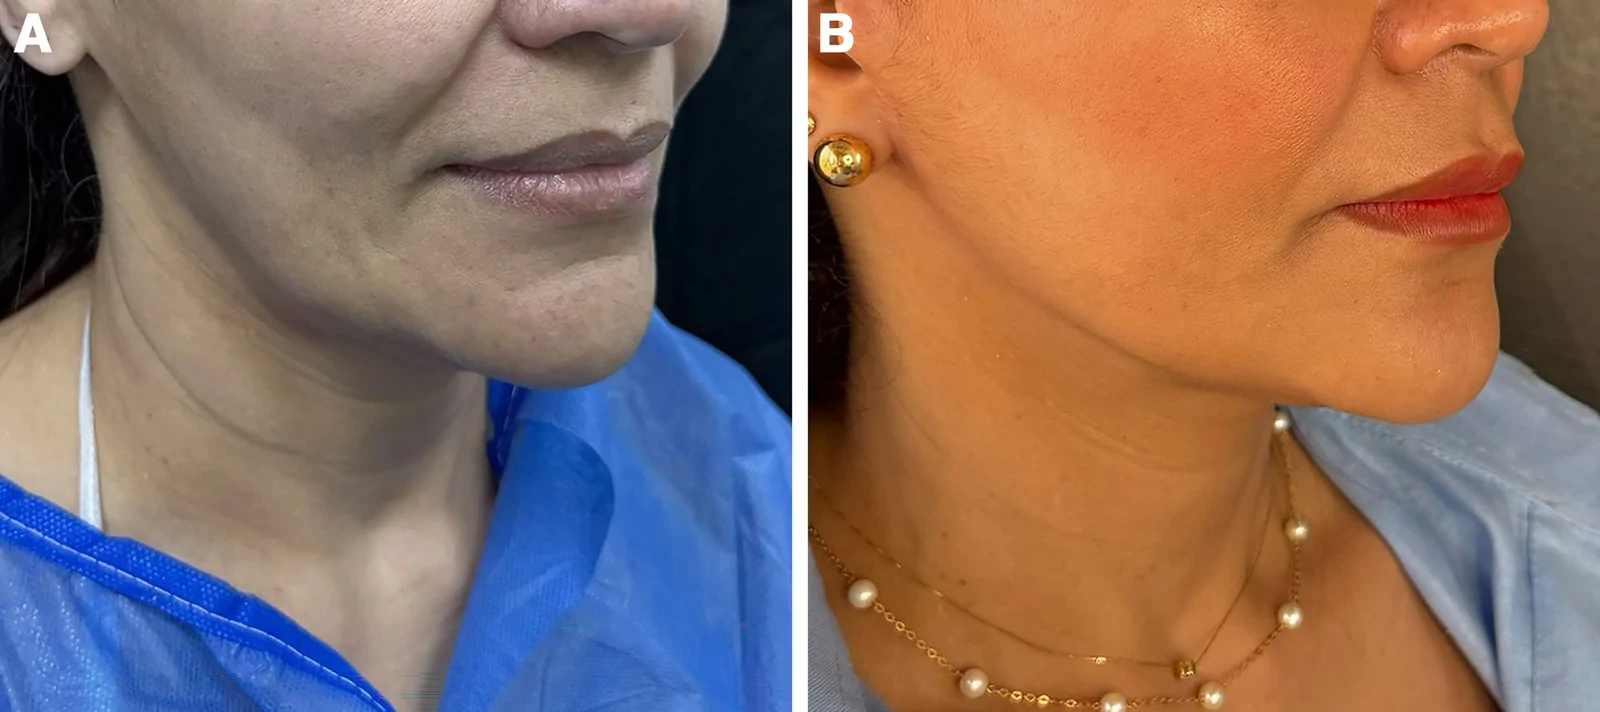
Fig. 5. Female patient 2. A, Preoperative right‑oblique view. B, Twelve-month postoperative photograph illustrating the maintenance of the desired V‑shaped facial silhouette and improved cervicomandibular contour.Patient satisfaction with the procedure was very high. Based on the FACE-Q scale, satisfaction with the appearance of their own face increased from low satisfaction (14.2 out of 100) to high satisfaction (85.1 out of 100). This difference was statistically significant (Student t = −22.8; P < 0.001) (Table 8 ).
Table 8. TDL Satisfaction Score
| Variable | Measure of Central Tendency | Dispersion Measurement | Test |
|---|---|---|---|
| FACE-Q score | Mean | SD | Student t |
| Before TDL | 14.2 | 13 | t = −22.8 |
| After TDL | 85.1 | 11.8 | P < 0.001 |
The present study introduces the TDL technique, which modifies lower facial laxity and neck laxity through a tunneled method that integrates principles from both deep-plane and plication techniques. This minimally invasive approach ensures natural and effective results and is applicable to younger patients.
Facial aging is a natural process in which gravity, over time, causes descent of the soft tissues, loss of skin elasticity, and volume loss due to decreased fat volume or tissue redistribution. 6 Therefore, a thorough preoperative assessment is crucial not only to determine the optimal surgical approach but also to guide the patient through the procedure and manage expectations. Essential preoperative requirements include smoking cessation, skin optimization, and stable weight (with no significant planned weight loss in the coming months). 7 , 8
The TDL procedure stands out for several reasons: it involves manipulation and repositioning of deep facial tissues and plication of the SMAS and platysma, performed in real time based on the most impactful mobile tissue points. The tunneled nature of the technique reduces the risk of nerve injury by manipulating fewer tissues within the sub-SMAS layers, including facial nerve branches and the auricular nerve close to the platysma-auricular ligament. Dissection within the fourth layer leads to minimal blood loss due to its low vascularity, and careful preservation of the true retaining ligaments of the face is ensured. Additionally, deep neck planes are avoided, reducing the risk of injury to major blood vessels and lymphatic pathways. 9
The TDL technique, combining deep-plane and plication approaches, provides immediate and sustained results. It offers an advantage over the limited durability of SMAS plication procedures. 2 , 10 The manipulation of the SMAS and platysma, similar to the biplane face lift, allows for improved results in modifying laxity and appearance of the lower third of the face and neck, achieving a natural look without excess skin. 11
In this patient sample undergoing TDL, no complications were reported, indicating a high safety profile for the procedure. This result is better than the complication rates reported for SMAS plication and deep-plane face lifts: temporary facial nerve injury (0.69% and 0.69%), permanent facial nerve injury (0% and 0%), seroma (1.46% and 4%), hematoma (0.73% and 1.22%), infection (0.53% and 0.73%), and skin necrosis (0.69% and 0.49%). 12 Additionally, immediate postoperative results did not show marked contour deformities, as the tunneled technique produces less bruising and edema than the deep–plane technique. 13
The SMAS plication technique has demonstrated good results in patients aged between 50 and 60 years, in whom facial aging processes are not as pronounced in the deep tissues, and manipulation of the SMAS yields satisfactory outcomes. On the other hand, the deep-plane face lift, which involves manipulating the deep tissues of the face, has proven to be superior in patients aged 60–70 years. 4 However, the TDL technique, by combining both approaches, performs well in both age groups, offering the benefits of both techniques by extending the TDL to the midface. Moreover, being a tunneled technique, it can be used in younger patients between the ages of 30 and 50 years who seek to correct facial and neck laxity with less severity, aiming to maintain the V-shaped contour of the lower facial border without requiring significant facial surgery.
Currently, most patients seeking facial rejuvenation surgery have previously undergone nonsurgical procedures to mitigate the effects of facial aging. Evidence of this is that 81.6% of the patients in this study had undergone some nonsurgical procedure in the facial region before surgery. The utility of fillers lies in replenishing facial areas that experience fat atrophy over time, thus reversing these age-related facial changes. 14 It has been shown that fat atrophy is more pronounced in the lateral cheek and deep midface regions, 15 which correspond to the midface. Therefore, TDL is an ideal procedure for these patients with good facial volume in the midface, as the manipulation of the midface during the procedure is minimal or unnecessary, thus avoiding postoperative deformity in this area in patients with adequate volume (this is a common complaint among young patients and those who have fillers in this region) (Figs. 6 – 9 ).
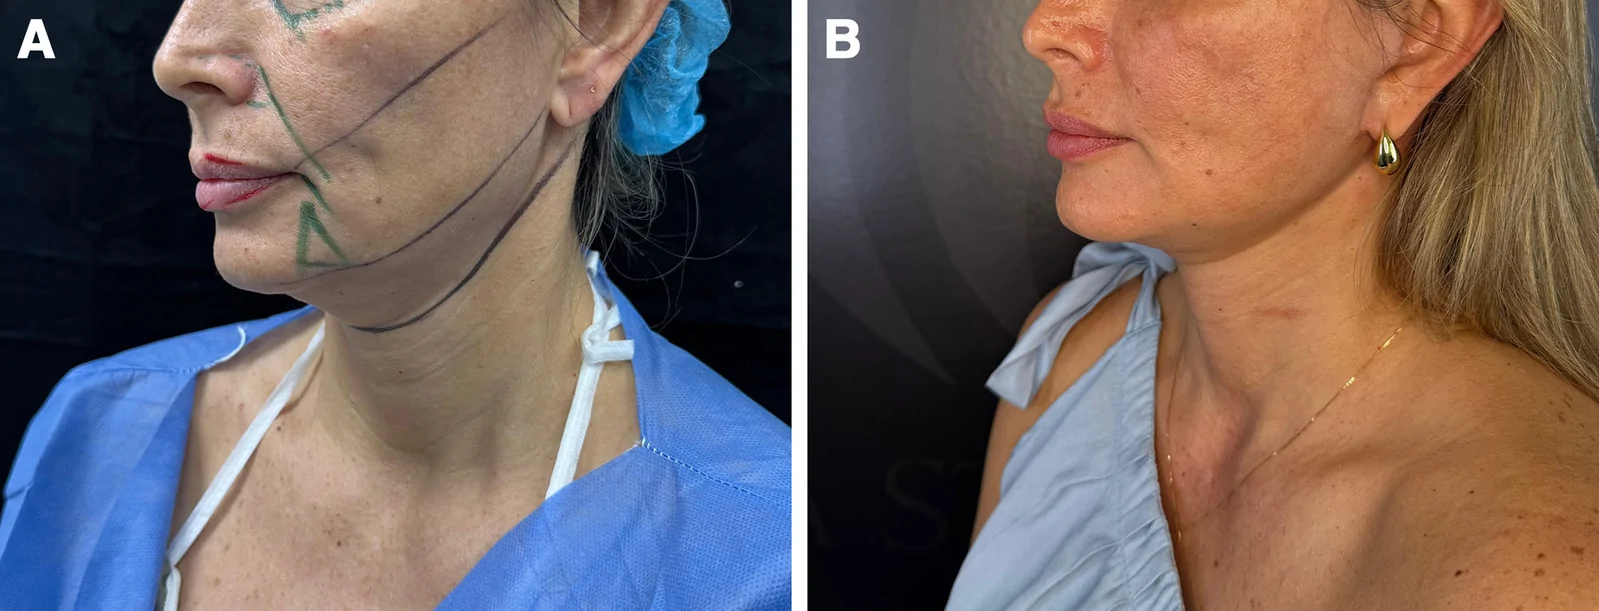
Fig. 6. Female patient 3. A, Preoperative right‑oblique view. B, One‑year follow‑up confirms maintenance of the desired V‑shaped facial silhouette and improved cervicomandibular contour.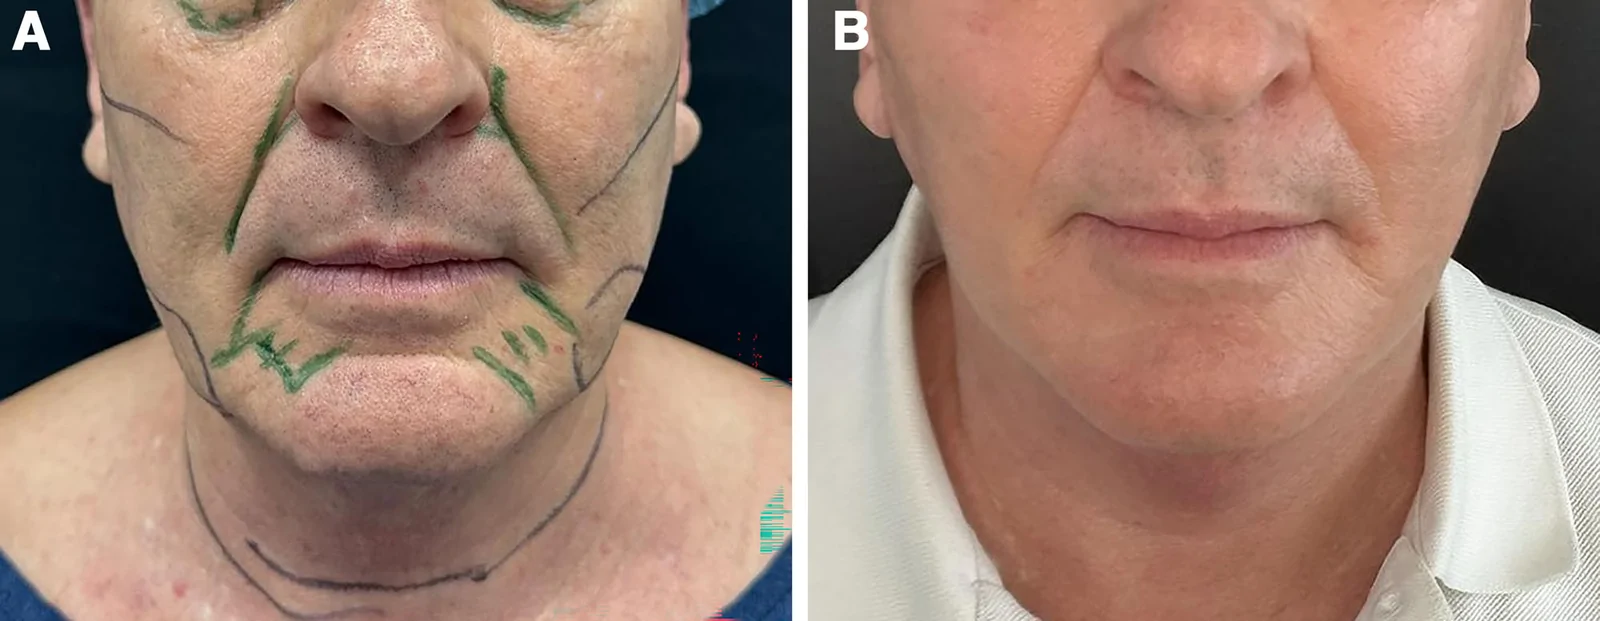
Fig. 7. Male patient 2. A, Preoperative frontal view. B, Twelve‑month postoperative image demonstrating resolution of laxity and labiomental heaviness with a more youthful, balanced lower third.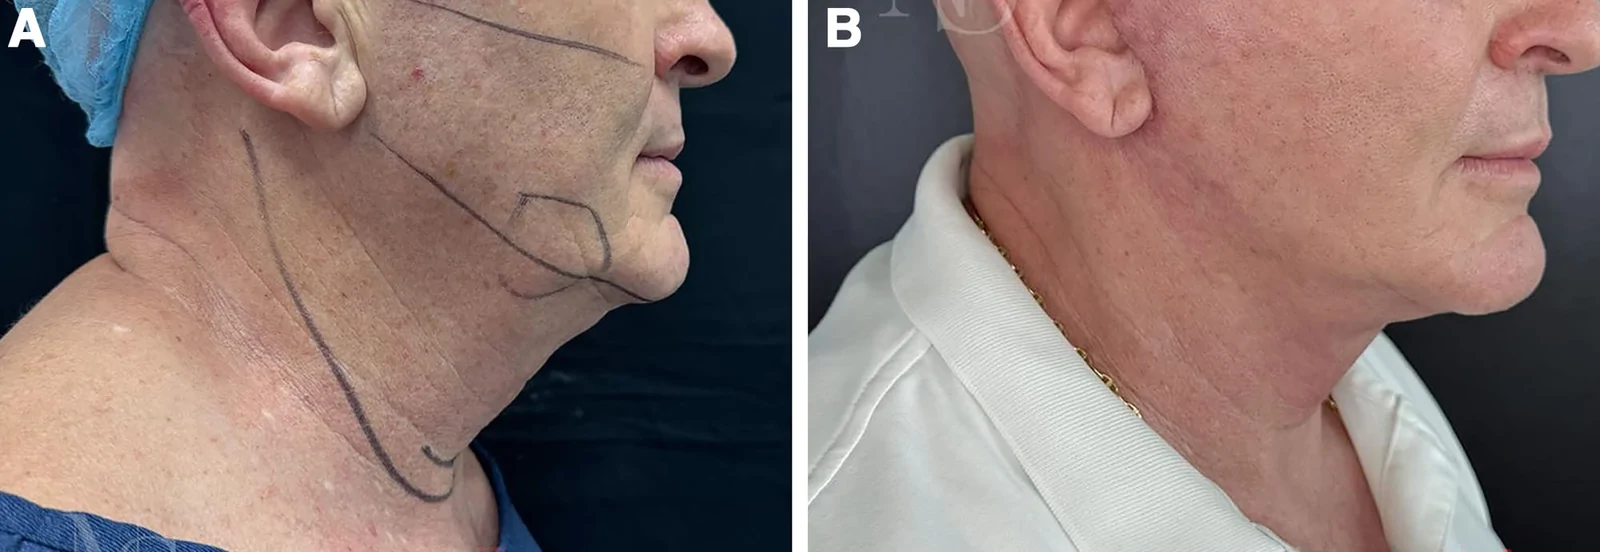
Fig. 8. Same patient as Figure 7. A, Preoperative right‑lateral view. B, Twelve‑month comparison showing correction of subplatysmal banding and a smoother cervicomental transition.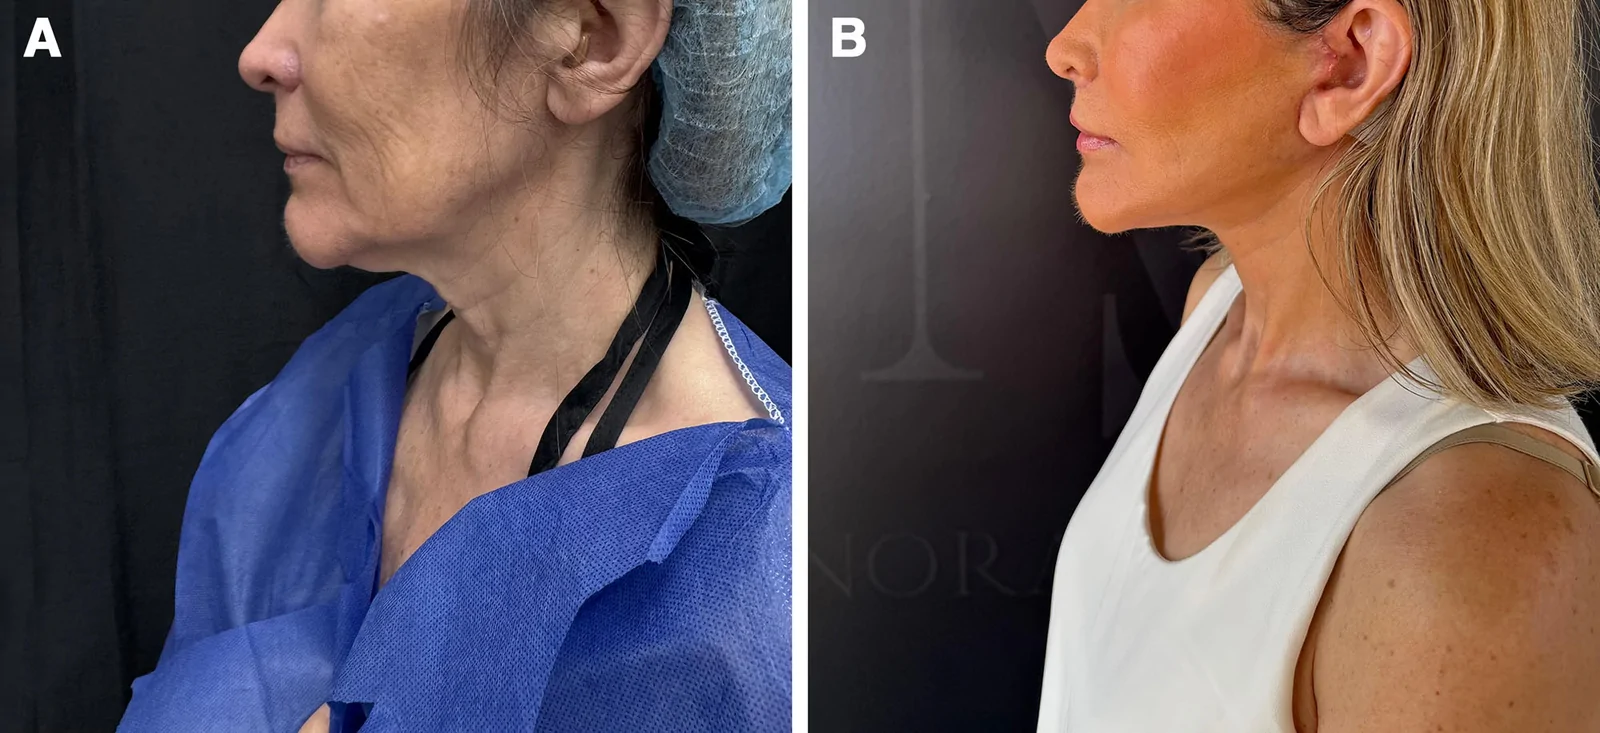
Fig. 9. Female patient 4. A, Preoperative lateral view. B, Twelve‑month image comparison showing correction of subplatysmal banding and a smoother cervicomental transition.Additionally, the TDL technique benefits from adjunctive measures that contribute to its excellent outcomes and low complication rate. First, tumescent preinfiltration has been shown to provide several benefits by reducing procedural complications, including skin flap tension (intraoperative tissue expansion), postoperative swelling, and hematomas. 16 Second, the use of subdermal radiofrequency—whose waves produce mechanical and thermal effects—disrupts cellular membranes in the deep dermis. This heat (40–84°C) in the tissue triggers a wound healing cascade that helps fibroblast differentiation and neocollagenesis, leading to collagen remodeling, which decreases skin laxity and improves the signs of skin aging. 17 , 18
Moreover, in our experience, we have found that the lateral neck corset performed in TDL has advantages over midline mandibular plication, as this new approach provides better definition of the mandibular angle, the midline mandibular region, the cervicofacial angle, and the jawline. However, future studies are needed to demonstrate these observations and assess the duration of these changes with each technique.
Our study has limitations, including the lack of a large sample size and follow-up extending beyond 2 years to assess long-term outcomes and safety of the procedure. Future research involving other surgeons who have adopted the TDL technique is needed to confirm its reproducibility, as well as studies comparing the results of deep plane, SMAS plication, and TDL.
In conclusion, the TDL is a novel technique that effectively corrects laxity of the lower third facial zone and the neck. This tunneled approach, which manipulates deep facial tissues such as the deep-plane technique and involves plication of the SMAS and platysma, provides immediate and noticeable results that are sustained throughout 1 year of follow-up. The technique is suitable for both patients aged 50–70 years and younger individuals, including those aged 30–50 years. The adjunctive use of subdermal radiofrequency enhances results by improving skin laxity and signs of skin aging (eg, expression marks, papules, nodes, scars, and skin spots). The intervention has demonstrated effectiveness, showing great outcomes and, at the same time, safety for patients, with no intraoperative or postoperative complications and a high satisfaction rate.
The authors have no financial interest to declare in relation to the content of this article.
Patients provided written consent for the use of their images.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
回顾性队列研究,纳入93例哥伦比亚患者(2023.6–2025.7,随访≥1年),平均52.9岁(SD 8.13),女85例(90%)、男8例(10%),平均BMI 26.8 kg

隧道式深层平面提升术(TDL)融合深层平面提升与 SMAS 折叠,为下面部与颈部松弛的改良术式;本研究为回顾性队列,纳入 2023–2025 年哥伦比亚 93 例随访≥1 年患者。
单中心7年系列:96例单次联合除皱+脂肪移植+全面部等离子换肤