耳成形术(Otoplasty)技术与临床结局的系统综述与荟萃分析
2026年10月20日33 min read
Plastic and Reconstructive Surgery Global Open
Plastic and Reconstructive Surgery Global Open

结论与实践要点
本篇为实用型系统综述与荟萃分析,聚焦招风耳(prominent ear)矫正。耳畸形影响全球约5%-10%人口,常见于抗耳轮折叠发育不良和/或耳甲腔过深。手术机制依技术路线不同分为:缝合保留软骨法(如Mustardé耳甲-耳舟褥式缝线重建抗耳轮、Furnas将耳甲软骨固定于乳突骨膜)、软骨弱化/切开法(前 scoring 或全层切开重塑),以及新兴的激光辅助软骨重塑(LACR)与经皮微创固定。综述提示软骨保留技术凭借可预期的稳定性仍是主流,但无单一技术被证明 universally 占优。
汇总并发症以缝线外露(5.4%)为主,其次感染/愈合问题(2.6%)、不对称(2.1%)、血肿(1.3%);无切口技术的起疱(22.6%)与缝线外露(21.9%)比例明显更高。复发与修复率均较低(pooled 2.8%与2.1%)。主要局限:94.4%为回顾性、仅1项随机试验;66.7%研究来自土耳其,人群与外推性受限;各研究对复发的定义不一致,且平均随访24.5月不足以评估长期;异质性高(I² 76%-81%),存在潜在发表偏倚(复发 Egger P=0.0138)。
本证据为间接证据(综述+荟萃分析,非单一在体临床试验),证据等级受纳入研究设计限制。须注意:文中'动物模型、CO2激光、 electromechanical reshaping'等仅出现在创新/未来方向章节,属背景介绍,所纳入18项研究均为人体(非人体研究已被排除),故临床结局数据来源为人体;但动物实验结论不可外推为人体疗效。未来需更多样化、长期、标准化前瞻性研究以提升论证强度。
Background:Otoplasty corrects auricular deformities, which affect 5%–10% of the global population and can significantly impact psychological well-being, especially in children. This review examined various otoplasty surgical techniques, clinical outcomes, complications, and emerging innovations, with a focus on prominent ear correction.
Methods:A literature search was conducted in November 2024 on PubMed/MEDLINE and Web of Science using the query “otoplasty,” identifying 1397 studies from 1915 to 2024. Studies were included if they detailed operative techniques, patient data (population >30), and mastoid-to-helical rim measurements. Exclusions included nonhuman studies, case reports, and incomplete data. Data extracted study characteristics, operative techniques, and complication rates. The Oxford Centre for Evidence-Based Medicine framework classified studies by evidence level.
Results:Eighteen studies with 1590 patients and 3060 ears were included. The average patient age was 16.0 years, with a mean follow-up of 24.5 months. The average preoperative mastoid-to-helical rim measurement was 27.1 mm, reduced to 15.4 mm postoperatively. Suture extrusion (5.4%) was the most common complication. Meta-analysis showed a pooled recurrence rate of 2.8% and revision rate of 2.1%. Cartilage-sparing techniques, as well as 4-0 polypropylene (Prolene) and 4-0 braided polyester (Ethibond) cartilage fixation sutures, showed favorable outcomes.
Conclusions:This review summarizes decades of research, highlighting effective techniques such as modified Mustardé–Furnas methods and cartilage-sparing approaches. Innovations and advancements in otoplasty, such as lasers, minimally invasive surgery, and postoperative care, demonstrate the field’s evolution. Future research should focus on refining techniques and exploring animal models to improve otoplasty procedures.
Takeaways
Question: Which otoplasty techniques provide safe, durable, and effective correction of ear prominence?
Findings: Historical and contemporary otoplasty techniques remain vast. Cartilage-sparing techniques, particularly Mustardé–Furnas and posterior approaches, effectively reduce ear prominence with low recurrence (2.8%) and revision rates (2.1%). The overall complication rate was 14.4%, with suture extrusion being the most common. Postauricular flaps improve long-term stability, and emerging minimally invasive or laser-assisted techniques show promise. Otoplasty also provides significant cosmetic and psychosocial benefits.
Meaning: Cartilage-sparing techniques offer reliable, effective correction of ear prominence with low complication and recurrence rates.
Otoplasty corrects the shape and position of the ears, addressing congenital and acquired auricular deformities. Between 5% and 10% of the global population is affected by prominent ears or other anomalies, with prevalence varying across demographics and ethnic groups. 1 Common conditions treated by otoplasty include prominent ears, constricted ears, lop ears, and Stahl ear deformity, all of which can significantly impact an individual’s aesthetic appearance and psychological well-being. Affected individuals, particularly children, may endure bullying, social anxiety, and diminished self-esteem, which can adversely affect their overall quality of life. 2 , 3 Otoplasty is instrumental in mitigating the psychological and social consequences associated with ear deformities in all age groups. 4
Ear prominence, the most common deformity, usually results from an underdeveloped antihelical fold and/or increased conchal bowl depth. 5 , 6 Although hundreds of techniques have been developed, no consensus exists regarding their objective effectiveness or long-term outcomes.
This practical review examined surgical techniques, clinical outcomes, complication rates, postoperative protocols, and quantitative metrics such as mastoid-to-helical rim distances. It also highlights recent advances including animal models, minimally invasive techniques, and laser-assisted cartilage reshaping (LACR) that suggest future directions for this evolving field.
Otoplasty traces its origins to the Sushruta Samhita (c. 500 ad), which influenced reconstructive techniques in Asia. 7 – 10 Modern advancements began in the late 19th century with Dieffenbach’s skin and cartilage excision. 11 In the early 20th century, Ely and Luckett refined techniques with cartilage scoring and suturing. 12 , 13 Mid-20th-century innovations by Mustardé 14 and Furnas 15 introduced suture-based methods to preserve cartilage integrity. Mustardé 14 technique, using conchoscaphal mattress sutures to recreate the antihelical fold, remains widely used but risks suture pull-through in firm cartilage. 16 , 17 Furnas 15 secured conchal cartilage to the mastoid periosteum to address deep conchal bowls, whereas Hilger et al 18 optimized contour with temporary anterior sutures before posterior fixation. 19 , 20
Cartilage-breaking methods, such as Stenström 21 and Chongchet 22 anterior scoring, reduce recurrence but risk overcorrection. 23 , 24 Beasley and Jones 25 used posterior conchal excision, whereas Bauer et al 26 and Elliott 27 introduced anterior conchal excision with skin strip removal to prevent folding. Cartilage-cutting methods, such as Converse and Wood-Smith 28 full-thickness incisions, reshape rigid cartilage by forming a thinned strip sutured to create an antihelical fold. 29 , 30 The Pitanguy 31 “island technique” and Farrior 32 combined excision further refined contouring. 33 , 34
Lobule prominence, often overlooked, requires individualized correction. Techniques include fish-tail, Z-plasty, and elliptical excisions, with some incorporating fat resection. 35 – 38 Modifications by Goulian, 39 Webster, 40 and Siegert 37 reposition the lobule through various skin and cartilage excisions. 41
Animal studies have driven minimally invasive otoplasty. Endoscopic rabbit models in 1998 showed long-term stability with fibrocartilage formation, 42 whereas CO 2 laser ablation in 2009 stimulated chondrocyte proliferation and cartilage regeneration. 43 Transcutaneous laser cartilage reshaping using a 1450-nm diode laser and cryogen spray cooling preserved cartilage viability, 44 and electromechanical reshaping produced significant auricular changes with minimal injury, including promising applications to costal cartilage. 45 – 47 These studies highlight minimally invasive approaches as safer, effective alternatives to traditional techniques.
Clinically, minimally invasive otoplasty integrates elements of cutting (Converse 48 ), scoring (Stenström’s 21 ), and suturing (Mustardé’s 14 ). 49 Outcomes demonstrate high satisfaction, minimal morbidity, and optimal results in patients with well-defined antihelix and limited conchal hypertrophy. 50 – 52
LACR provides a noninvasive option. Studies on 1.54-μm erbium-doped yttrium aluminum garnet and Er/Glass lasers report stable reshaping with few complications, 53 , 54 whereas CO 2 LACR reduces ear protrusion while preserving perichondrium. 55 A 2020 study combining laser with cryogen cooling further improved satisfaction and outcomes. 56 LACR offers smoother contours, reduced scarring, and potential applications in pediatric otoplasty and other cartilage corrections.
A thorough understanding of auricular anatomy is essential for optimal otoplasty. The auricle, auditory canal, and middle ear develop from the first 2 branchial arches by week 4 of gestation, with incomplete fusion causing deformities such as prominent, lop, or Stahl ear. 57 Siliprandi et al 58 divided the ear into 4 surgical subunits—helical/scaphal, antihelical, conchal, and lobular—each requiring tailored strategies. A 21-year study of 274 cases validated this system, demonstrating high patient satisfaction and low complication rates. 58 Normative guidelines recommend a helical rim-mastoid distance of 10–12 mm at the superior pole, 16–18 mm at the mid-third, and 20–22 mm at the cauda helix, with an auriculomastoid angle of 15–30 degrees (Fig. 1 ). 60 Ear position also influences auditory perception, affecting speech reception and sound directionality. 61
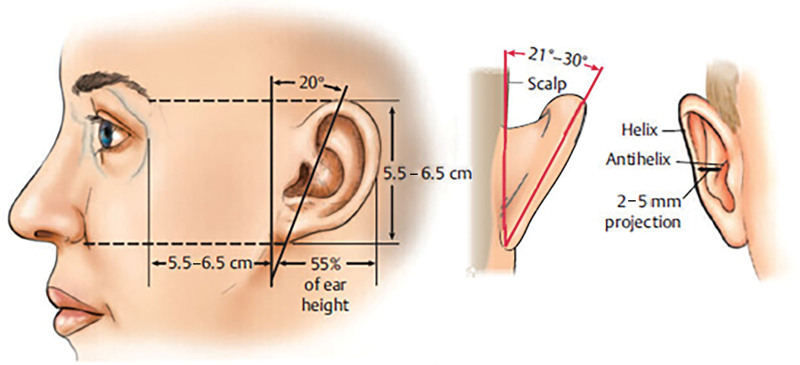
Fig. 1. Key measurements for helical rim projection and auriculomastoid angle. Reproduced with permission from Thieme (Janis JE, ed. Essentials of Plastic Surgery. 3rd ed. 2022; Fig 33.4.)59Population and gender-specific considerations are important. Ninety percent of auricular growth occurs by age 11–12 years, with prominence greater than 21.5 mm in boys and greater than 17.5 mm in girls. 62 – 66 Asymmetry greater than 3 mm occurs in 19.3% of normal ears, challenging rigid correction criteria. 67 Cartilage stiffness peaks at 35 years and declines after 40 years, impacting surgical results. Younger patients (5–14 y) achieve near-normative distances with high satisfaction, whereas older patients retain stiffer cartilage and report lower satisfaction, emphasizing age-specific approaches. 68
Optimal timing balances growth, cartilage pliability, psychological effects, and patient preference. Although ear growth is nearly complete by age 6, procedures before age 4 may not disrupt development due to softer cartilage. 41 , 69 Nonsurgical approaches, such as newborn auricular molding, leverage early cartilage plasticity with promising outcomes. 70 – 73
Although auricular deformities are not physiologically harmful, they can cause significant psychosocial distress, particularly in children. Protruding ears attract visual attention, but do not affect perceived intelligence or likability. 74 Otoplasty improves emotional, physical, and social well-being in children and adults alike, enhancing body image and reducing social anxiety. 75 – 79 Overall, it provides lasting quality-of-life benefits.
A systematic search of PubMed/MEDLINE and Web of Science was conducted in November of 2024 using the query “otoplasty,” identifying 1397 studies published between 1915 and 2024. Inclusion criteria encompassed studies detailing operative techniques to correct prominent ears, patient populations greater than 30, and documented mastoid-to-helical rim measurements. To ensure diagnostic homogeneity, only studies that specifically addressed the correction of prominent ears were included in this analysis, and studies involving other auricular anomalies were excluded. Exclusion criteria included nonhuman studies, nonclinical papers, inconsistent or sparse operative details, incomplete data, case reports, letters, and non-English publications. Studies were categorized into single-population operative techniques and comparative studies (Fig. 2 ).
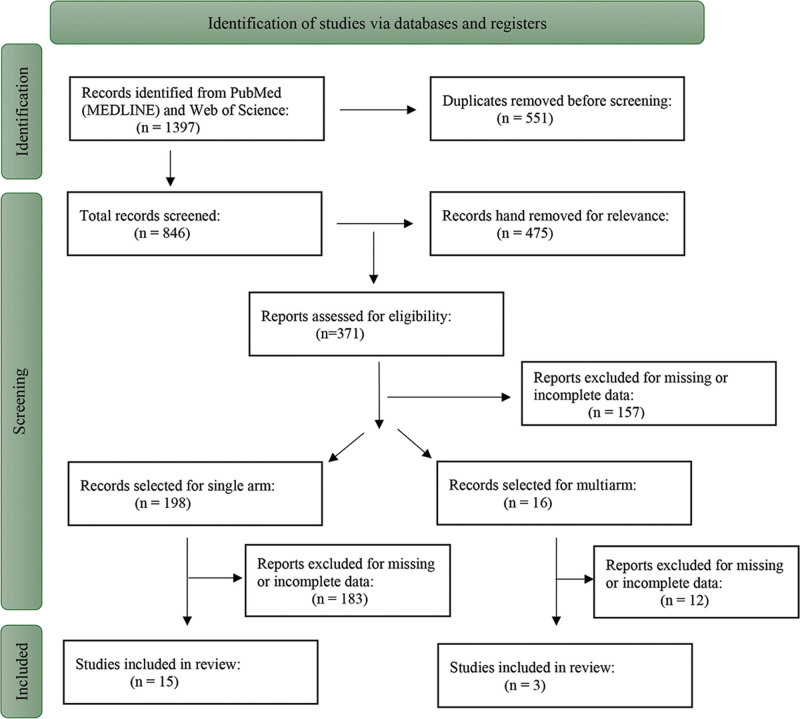
Fig. 2. Flow chart of studies included in the practical review.Data were extracted using a standardized data form, including author(s), year, country, and Oxford level of evidence. 80 Variables collected included patient number and mean age, follow-up, unilateral/bilateral procedures, total ears, technique, complication rates, and revision and recurrence rates. Recurrence and revision rates were recorded according to the definition used in each primary study; no independent reinterpretation of recurrence criteria was applied. Procedural specifics such as cartilage manipulation, surgical approach, fixation method, preoperative/postoperative measurements, and statistical significance were also recorded. As this study analyzed previously published data, institutional review board approval was not required.
Descriptive statistics (mean, frequency, SD, range) were calculated. Ear prominence measurements reported in degrees were converted to millimeters using trigonometric formulas for standardization. A meta-analysis was performed using Stata/BE 18.0, using single proportion estimation for effect size calculation. Heterogeneity was assessed via the I ² index, and publication bias was evaluated with the Egger test and funnel plots. A leave-one-out meta-analysis assessed effect size stability. Subgroup analyses were conducted on recurrence and revision rates based on cartilage techniques, surgical approach, and fixation methods. Bias was further analyzed using trim-and-fill methods to account for publication bias.
After applying inclusion and exclusion criteria, 18 studies (1996–2023) were included (Table 1 ), comprising 15 single-technique and 3 multitechnique comparative studies. A total of 1590 patients (3060 ears) underwent 1254 bilateral and 73 unilateral procedures; 2 studies did not specify laterality. The cohort included 944 men and 746 women, with study populations ranging from 30 to 375 patients (mean: 76). The average patient age was 16.0 years (range: 8.2–28.3 y), and follow-up averaged 24.5 months (range: 6–75 mo). One study was a randomized clinical trial, whereas 17 (94.4%) were retrospective cohorts. Most studies were from Turkey (66.7%), followed by the United Kingdom (11.1%), Canada, Egypt, Switzerland, and Pakistan (5.6% each).
Table 1. Clinically Effective Otoplasty Techniques
| First Author | Year | LOE | Country | Total Patients | Total Ears Operated | Mean Age, y | Unilateral | Bilateral | Follow–up, mo | Mastoid–Helix Rim Reduction, mm |
|---|---|---|---|---|---|---|---|---|---|---|
| Messner 81 | 1996 | III | Canada | 51 | 100 | 8.2 | 2 | 49 | 44.4 | 8.90 |
| Foda 82 | 1999 | III | Egypt | 39 | 76 | 9.3 | 2 | 37 | 28.4 | 8.40 |
| Horlock 83 | 2001 | III | United Kingdom | 51 | 96 | 10.0 | 6 | 45 | 11.0 | 10.00 |
| Schaverien 84 | 2010 | III | United Kingdom | 60 | 112 | 8.5 | — | — | 46.8 | 10.60 |
| Schlegel-Wagner 85 | 2010 | III | Switzerland | 222 | 421 | 11.0 | — | — | 75.0 | 14.60 |
| Sahin 86 | 2015 | III | Turkey | 30 | 60 | 14.5 | 0 | 30 | 12.0 | 10.62 |
| Haytoglu 87 | 2015 | I | Turkey | 30 | 55 | 7.8 | 5 | 25 | 6.0 | 13.30 |
| 30 | 57 | 8.7 | 3 | 27 | 12.80 | |||||
| Gümüş 88 | 2016 | III | Turkey | 42 | 84 | 16.0 | 0 | 42 | 12.0 | 16.60 |
| Basat 89 | 2016 | III | Turkey | 47 | 88 | 14.5 | 6 | 41 | 33.0 | 10.89 |
| Temel 90 | 2016 | III | Turkey | 87 | 163 | 21.0 | 5 | 79 | 22.0 | 12.00 |
| 69 | 128 | 22.0 | 0 | 64 | 39.0 | 9.00 | ||||
| Ersen 91 | 2019 | III | Turkey | 162 | 322 | 28.3 | 2 | 160 | 22.5 | 18.20 |
| Ors 92 | 2020 | III | Turkey | 375 | 725 | 24.2 | 25 | 350 | N/A | 10.70 |
| Mutaf 93 | 2020 | III | Turkey | 44 | 76 | N/A | 12 | 32 | 54.0 | 13.00 |
| Iqbal 94 | 2021 | III | Pakistan | 47 | 94 | 22.0 | 0 | 47 | 6.0 | 8.00 |
| Mehmet 95 | 2021 | III | Turkey | 42 | 80 | 18.6 | 4 | 38 | 19.2 | 10.00 |
| Ciloglu 96 | 2022 | III | Turkey | 49 | 97 | 14.6 | 1 | 48 | 14.8 | 10.51 |
| Duran 97 | 2023 | III | Turkey | 61 | 122 | 24.0 | 0 | 61 | 13.0 | 12.00 |
| Uyar 98 | 2023 | III | Turkey | 27 | 54 | 13.9 | 0 | 54 | 12.0 | 11.94 |
| 25 | 50 | 14.6 | 0 | 25 | 13.62 |
Cartilage-sparing techniques were most common (77.8%). The most frequent fixation sutures were 4-0 polypropylene (Prolene; Ethicon, Raritan, NJ) and 4-0 braided polyester (Ethibond; Ethicon) (26.3% each), whereas the most common skin closure suture was 5-0 Prolene (53.8%), followed by 4-0 poliglecaprone 25 (Monocryl; Ethicon) (15.4%). Preoperative mastoid-to-helical rim measurements averaged 27.1 ± 3.3 mm, decreasing to 15.4 ± 2.8 mm postoperatively, with a mean reduction of 11.7 ± 3.0 mm. Eight studies reported statistically significant reductions, whereas the remaining 10 lacked statistical analysis.
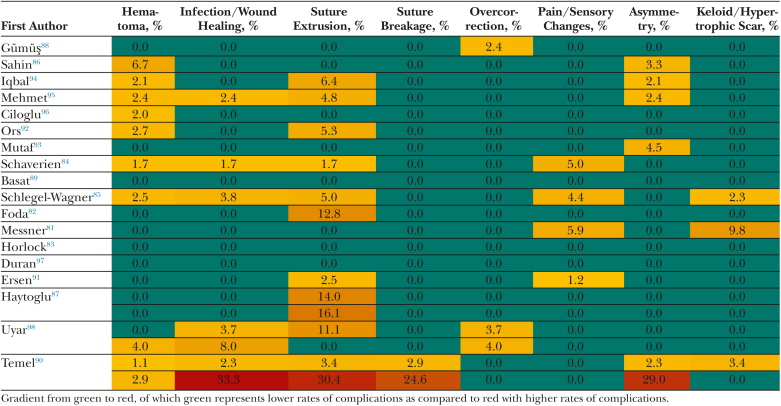
The cumulative complication rate across studies averaged 14.4%, with suture extrusion being the most common (5.4%), followed by infection and wound healing issues (2.6%), asymmetry (2.1%), hematoma (1.3%), and suture breakage (1.3%) (Table 2 ). Minor complications, including overcorrections/undercorrections, sensory changes, necrosis, hearing impairment, and keloid or hypertrophic scars, occurred in less than 1% of cases.
Table 2. Heatmap of Specific Complications Across All Studies
Postoperative care protocols for otoplasty vary across studies (Table 3 ). Immediate postoperative measures range from occlusive and bolster dressings to the use of Penrose drains and gauze applications, with removal times differing from 1 to 10 days. Extended postoperative care generally involves headband usage, with durations varying from 1 to 6 weeks, typically transitioning from full-time wear to nighttime use.
Table 3. Immediate and Extended Postoperative Protocols Across All Studies
| First Author | Year | Immediate Postoperative Care | Extended Postoperative Care |
|---|---|---|---|
| Messner 81 | 1996 | Occlusive dressing left intact for 2 d, then replaced with light gauze dressing worn for 2 wk | Velcro headband worn at night for a month |
| Foda 82 | 1999 | Penrose drain, light-pressure dressing applied with vaselinized ribbon | Not specified |
| Horlock 83 | 2001 | Not specified | Head bandage applied for 1 wk |
| Schaverien 84 | 2010 | Standard head bandage applied and is replaced | Headband worn at night for 6 wk |
| Schlegel-Wagner 85 | 2010 | Soft dressing removed after 1 wk | Headband for an additional 4 wk during sleep and sports |
| Sahin 86 | 2015 | Turban dressing for 6 d | Bandage at night for 30 d |
| Haytoglu 87 | 2015 | Not specified | Not specified |
| Gümüş 88 | 2016 | Gauze pads placed over the anterior and posterior surface for 7 d | After removal, an elastic band is worn for 10 d |
| Basat 89 | 2016 | Anterior and posterior parts of auricular cartilage covered with petroleum gauze and elastic head bandage used for 1 d | Elastic bandage used for the entire day for 1 wk and at night for 3 wk |
| Temel 90 | 2016 | Penrose drain placement; bacitracin and neomycin–containing dressing is applied; sutures removed on 10th postoperative day | Headband usage for 2 wk following |
| Ersen 91 | 2019 | Gauze used and elastic head bandages removed on the fourth day | Headbands until the 21st day and bandages worn overnight for an additional 3 wk |
| Ors 92 | 2020 | Passive drain placed in posterior region, serum-impregnated cotton strips, and pressure dressing applied; drain removed after 1 d | Not specified |
| Mutaf 93 | 2020 | Bactigras impregnated with soft paraffin BP, containing 5% w/w chlorhexidine acetate BP. Mastoid dressing removed after 1 d, and the ear left open with topical bacitracin and neomycin sulfate | Headband used only at night for 1 wk postoperatively |
| Iqbal 94 | 2021 | Not specified | Circumferential crepe bandage applied for 4 wk |
| Mehmet 95 | 2021 | Gauze soaked in antibiotic ointment for 1 d | Headband all day for 1 wk |
| Ciloglu 96 | 2022 | Bolster dressing, changed after 1 wk | Tennis player headband used for 4 wk |
| Duran 97 | 2023 | Bandages opened 3 d after surgery and rebandaged, removed on the 10th day | Headband usage at all times for 2 wk, followed by only during nights for 1 wk |
| Uyar 98 | 2023 | Dressings applied every other day for 1 wk | Bandaging applied day and night for 1 mo |
Two meta-analyses synthesized data from 18 studies investigating cumulative recurrence and revision rates. Comparative studies were divided into respective techniques as individual studies. The pooled recurrence rate across the 21 included studies was 2.8% (95% confidence interval [CI]: 0.9%–5.6%, P < 0.0001), with substantial heterogeneity ( I ² = 81.05%, Q = 95.40, P < 0.0001), as estimated using a random-effects model (Fig. 3 ). The pooled revision rate was 2.1% (95% CI: 0.6%–4.3%, P < 0.0001), also with substantial heterogeneity ( I ² = 76.13%, Q = 106.63, P < 0.0001) (Fig. 4 ).
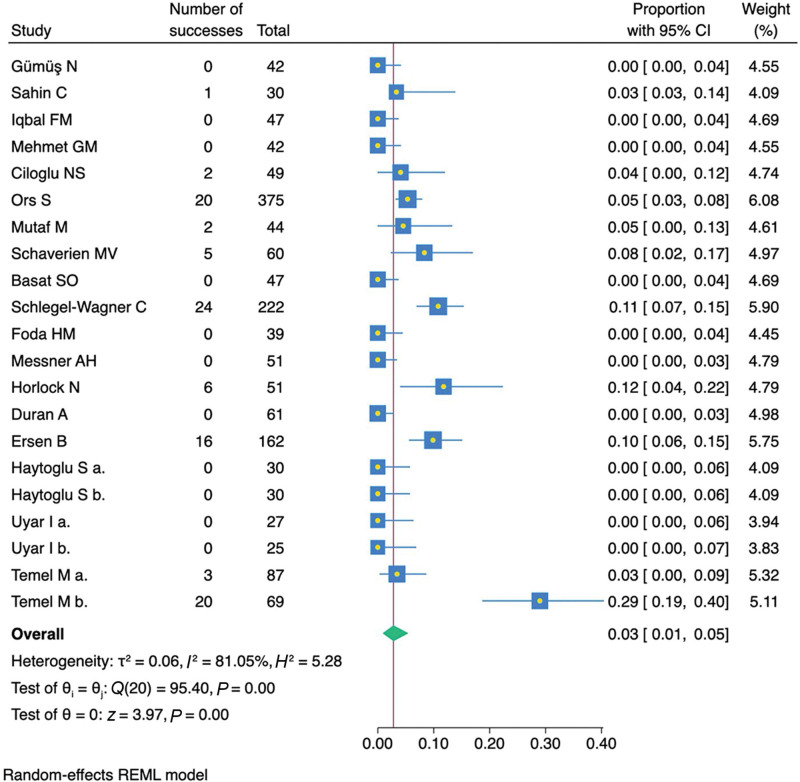
Fig. 3. Recurrence rate forest plot of studies included in the practical review. REML, restricted maximum likelihood.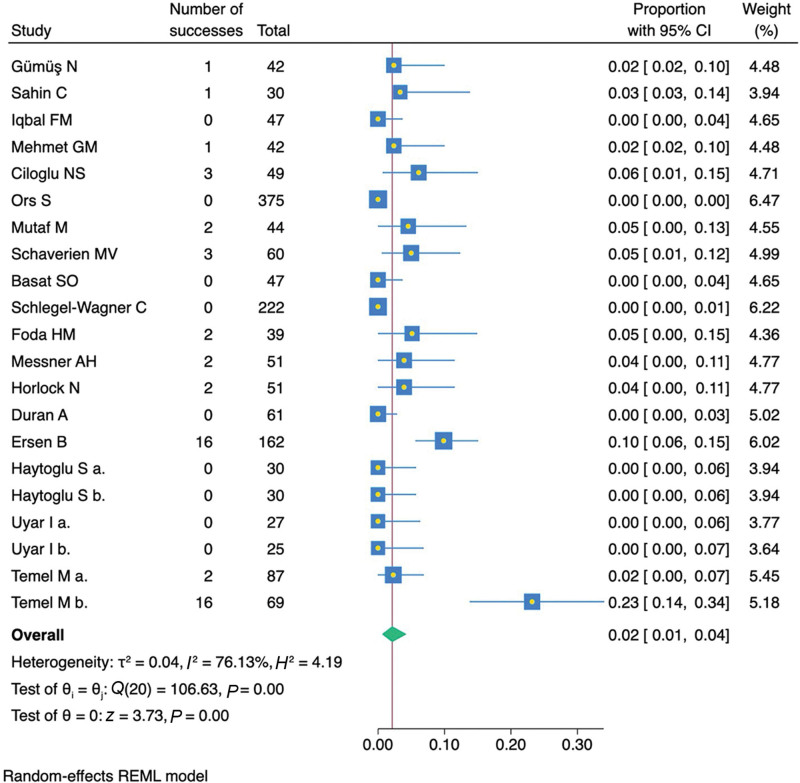
Fig. 4. Revision rate forest plot of studies included in the practical review. REML, restricted maximum likelihood.Two leave-one-out sensitivity analyses were performed, which confirmed stable estimates for both recurrence (2.2%–3.1%) and revision rates (1.5%–2.5%), with all P values remaining significant. Subgroup analyses by surgical approach, cartilage manipulation, and suture materials showed a pooled recurrence rate of 3.2% (95% CI: 1.0%–6.3%, P < 0.001) and a revision rate of 2.4% (95% CI: 0.7%–4.9%, P < 0.001) (Figs. 5 , 6 ).
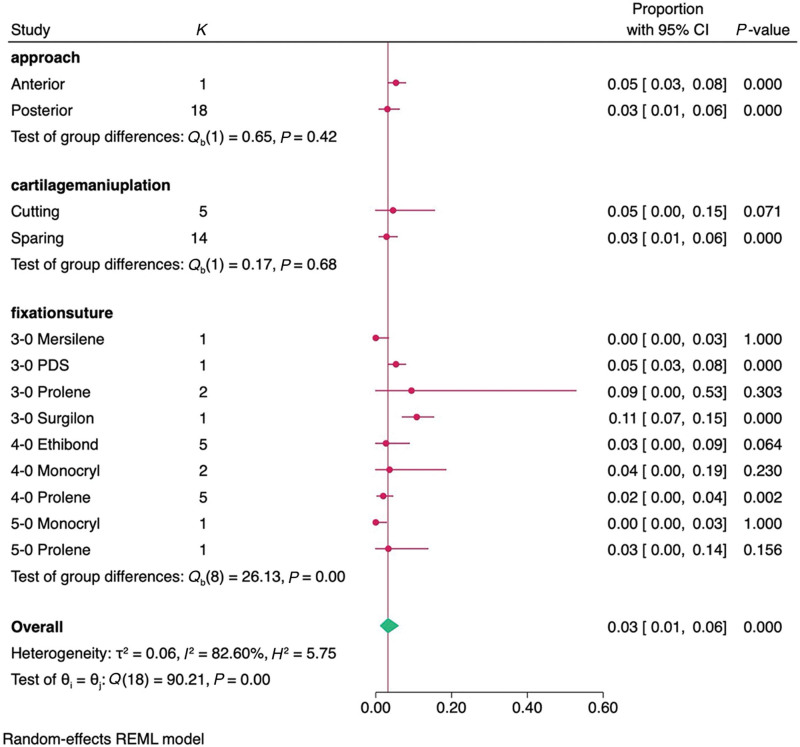
Fig. 5. Recurrence rate subgroup meta-analysis forest plot of studies included in the practical review. REML, restricted maximum likelihood.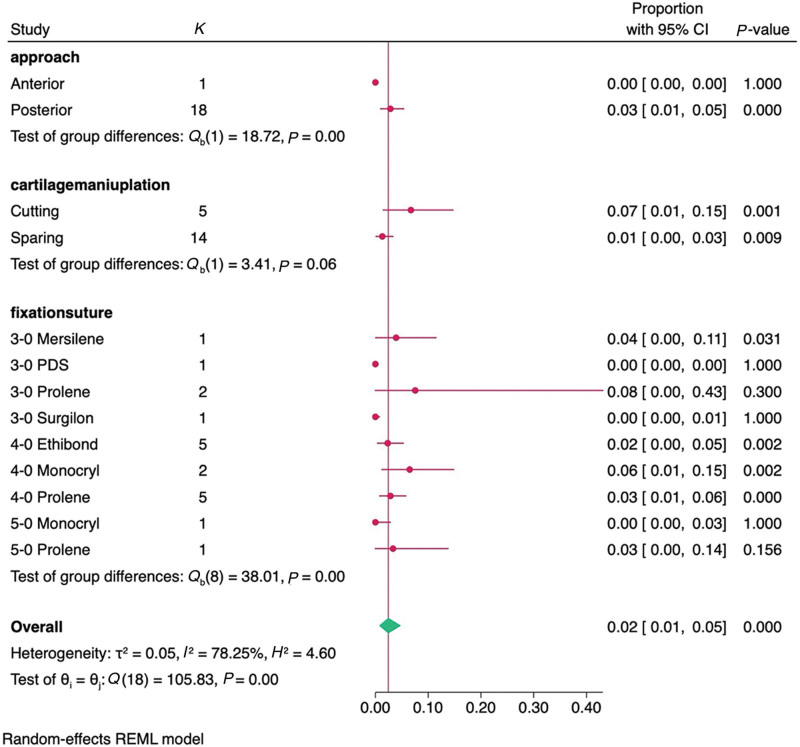
Fig. 6. Revision rate subgroup meta-analysis forest plot of studies included in the practical review. REML, restricted maximum likelihood.The posterior approach had a recurrence rate of 3.1% (95% CI: 0.8%–6.4%, P < 0.001) and a revision rate of 2.8% (95% CI: 1.0%–5.4%, P < 0.001), whereas the anterior approach had a higher recurrence rate of 5.3% (95% CI: 3.3%–7.9%).
Cartilage-sparing techniques had a lower recurrence rate (2.9%, P < 0.001) and revision rate (1.3%, P < 0.001) compared with cartilage-cutting techniques (recurrence: 4.6%, P = 0.062; revision: 6.7%, P = 0.011).
For suture materials, 4-0 Prolene had the lowest recurrence (2.0%, P = 0.007) and revision rates (2.9%, P = 0.005), whereas 3-0 Prolene showed a higher revision rate (7.5%, P = 0.408). Small-study effects and publication bias were assessed, with recurrence showing potential bias ( P = 0.0138), whereas no bias was found for revision ( P = 0.876). Corresponding Galbraith and funnel plots are represented by Figures 7 – 10 .
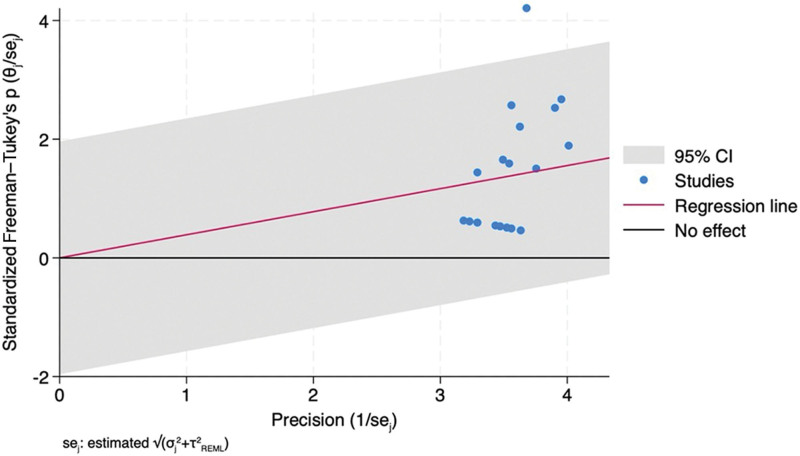
Fig. 7. Recurrence rate Galbraith plot. REML, restricted maximum likelihood.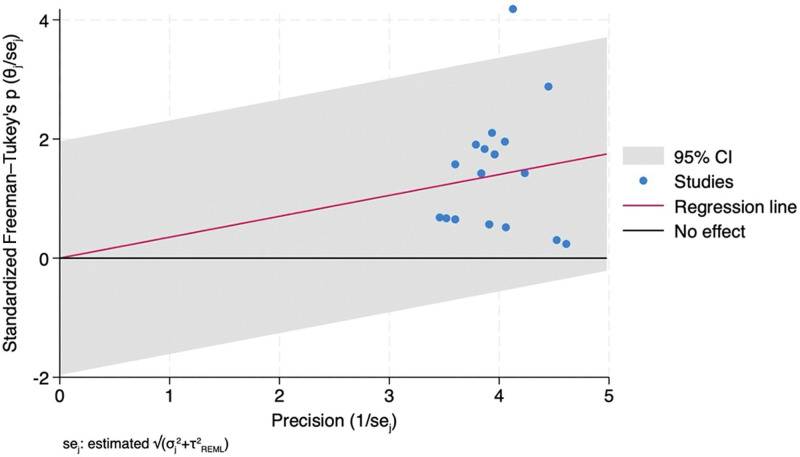
Fig. 8. Revision rate Galbraith plot. REML, restricted maximum likelihood.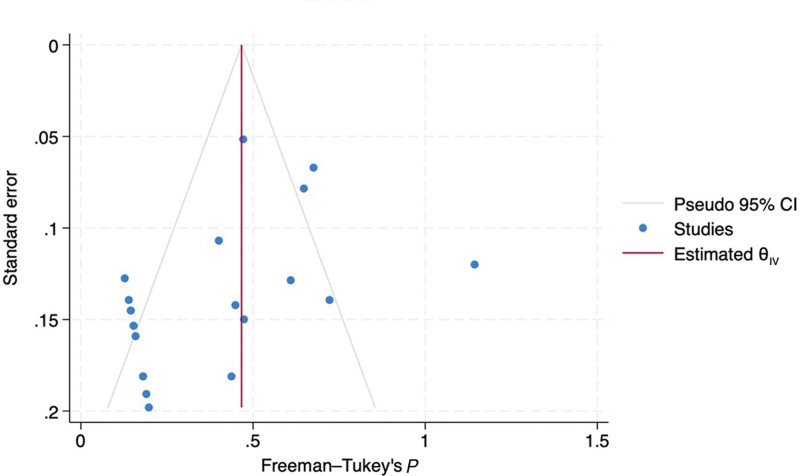
Fig. 9. Recurrence rate funnel plot.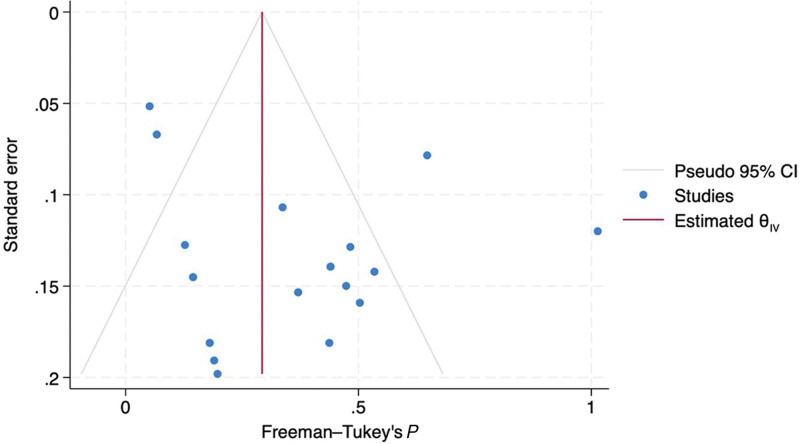
Fig. 10. Recurrence rate funnel plot.
Early studies validated foundational techniques, with Messner and Crysdale 81 showing that Mustardé 14 and Furnas 15 sutures achieved good or excellent results in 78% of pediatric cases, despite some relapse in the superior auricle. Foda 82 enhanced outcomes by incorporating cartilage-weakening maneuvers, though minor correction loss occurred during 6 months. Modifications of traditional methods further improved results. Schlegel-Wagner et al 85 demonstrated that combining antihelixplasty with postauricular sutures provided consistent, long-term correction. Sahin and Turker 86 used cartilage thinning with a diamond drill and Mustardé 14 sutures to achieve precise reshaping with low complication rates. Mehmet and Baklaci 95 refined the Mustardé–Furnas technique by tailoring postauricular tissue removal and muscle repositioning, reducing recurrence. Gümüş and Yilmaz 88 developed a posterior method avoiding anterior skin dissection, minimizing complications while ensuring symmetry. Mutaf and Temel 93 developed the dermal anchor technique, which relied on dermal adhesion instead of cartilage manipulation, yielding a low 2.63% recurrence rate. Ors 92 introduced controlled anterior cartilage tunneling combined with strategic suturing, achieving robust outcomes across 375 patients. Iqbal et al 94 refined anterior cartilage scoring to improve antihelical fold recreation, enhancing conchomastoid distances and patient satisfaction. These studies showcase the evolution of otoplasty, blending traditional and innovative methods to optimize aesthetics, minimize complications, and reduce recurrence. Table 4 summarizes key advancements.
Table 4. Conventional and Modified Techniques Used in Otoplasty
| Author | Technique | Cartilage Manipulation | Study Details | Fixation Suture | Recurrence Rate, % | Revision Rate, % |
|---|---|---|---|---|---|---|
| Messner 81 | Mustardé–Furnas | Sparing | Classical technique, standard Mustardé 14 and Furnas 15 cartilage-sparing | 3-0 Mersilene | 0.0 | 3.9 |
| Foda 82 | Modified Mustardé–Furnas | Cutting | Classical technique, standard Mustardé 14 and Furnas 15 cartilage-sparing | 4-0 Prolene | 0.0 | 5.1 |
| Schlegel-Wagner 85 | Lucerne | Sparing | Lucerne technique; anterior cartilage scoring with double-ended rasp | 3-0 Surgilon | 10.9 | 0.0 |
| Sahin 86 | Modified Mustardé 14 | Sparing | Cartilage thinning with a 2-mm diamond burr | 5-0 Prolene | 3.3 | 3.3 |
| Mehmet 95 | Modified Mustardé–Furnas | Sparing | Postauricular muscle relocation and fibrofatty tissue excision | 4-0 Ethibond | 0.0 | 2.4 |
| Gümüş 88 | Modified Mustardé 14 | Cutting | Sequential partial cartilage incisions in the shape of a greater-than mark to soften and manipulate the cartilage | 4-0 Monocryl | 0.0 | 2.3 |
| Mutaf 93 | Modified Mustardé 14 | Sparing | Dermal anchor technique | 4-0 Prolene | 4.5 | 4.5 |
| Ors 92 | Modified Mustardé–Furnas | Sparing | Use of a specialized 1-mm tooth rasp | 3-0 PDS | 5.3 | 0.0 |
| Iqbal 94 | Modified Chongchet–Furnas | Sparing | Lazy S-shaped incision for precise cartilage reshaping and optimized exposure | 5-0 Prolene | 0.0 | 0.0 |
The effectiveness of postauricular fascial and dermal flaps combined with cartilage-sparing otoplasty techniques has been examined in several studies (Table 5 ). In 2001, a refined method incorporating Mustardé 14 and Furnas 15 sutures with a postauricular fascial flap achieved an 8% recurrence rate, with no suture extrusions or hematomas over a median follow-up of 19 months in 51 patients. 83 Horlock et al 83 highlighted that the fascial flap provided vascularized protection, reducing extrusion and recurrence rates, while preserving aesthetics. Schaverien et al 84 reported a 4.5% recurrence rate in 60 pediatric patients with a follow-up of more than 3.9 years, with minimal medialization loss and high satisfaction. More recently, in 2016, Basat et al 89 investigated a laterally based postauricular dermal flap combined with cartilage-sparing techniques, demonstrating significant improvements in helix–mastoid distance and concha–mastoid angle at 1 and 12 months postoperatively, with no recurrences. This approach effectively mitigated common complications, offering a stable, vascularized alternative to cartilage-cutting methods.
Table 5. Postauricular Fascial Flaps Studies in Otoplasty
| Author | Cartilage Manipulation | Study Details | Fixation Suture | Recurrence Rate, % | Revision Rate, % |
|---|---|---|---|---|---|
| Horlock 83 | Sparing | Subcutaneous tissue on the posterior aspect of the auricular cartilage as the fascial flap | 4-0 Ethibond | 11.8 | 4.0 |
| Schaverien 84 | Sparing | Postauricular composite flap of postauricular SMAS and perichondrium | 4-0 Ethibond | 8.3 | 5.0 |
| Basat 89 | Sparing | Laterally based postauricular dermal flap | 3-0 Prolene | 0.0 | 0.0 |
The integration of perichondrio-adipo-dermal (PAD) flaps with traditional otoplasty to enhance correction has been explored in recent studies (Table 6 ). In 2019, Ersen 91 introduced a modified posterior PAD flap technique, which improved ear symmetry, reduced operation time, and provided long-lasting cosmetic results. By narrowing the flap width to 8–10 mm and preserving the skin between the helix and mastoid, this technique allowed for precise control over the helix–mastoid distance, with significant improvements in ear position. In 2022, Ciloglu et al 96 combined suture otoplasty with PAD flaps, showing a reduction in the mean helix–mastoid distances. More recently, in 2023, Duran et al 97 introduced a 3-layer PAD flap technique combined with Mustardé 14 and Furnas 15 sutures, which demonstrated significant improvements in auricular dimensions and patient satisfaction.
Table 6. PAD Flaps Studies in Otoplasty
| Author | Cartilage Manipulation | Study Details | Fixation Suture | Recurrence Rate, % | Revision Rate, % |
|---|---|---|---|---|---|
| Ersen 91 | Sparing | Laterally based PAD flap fixed to the mastoid bone periosteum | 4-0 Monocryl | 9.9 | 9.9 |
| Ciloglu 96 | Cutting | PAD flap, conchal crescentic excision, conchomastoid suture, and Bauer et al 26 squid incision | 4-0 Prolene | 4.1 | 6.1 |
| Duran 97 | Sparing | Three PAD flap technique | 5-0 Monocryl | 0.0 | 0.0 |
Several studies have explored comparative analyses of otoplasty techniques that reveal distinct advantages and limitations (Table 7 ). A 2015 randomized study of 60 patients found Haytoglu 87 modification and Fritsch 99 incisionless suture techniques equally effective in reducing auriculocephalic distances with high patient satisfaction. A 2016 study showed that the consolidative technique otoplasty had superior long-term outcomes during a 13-month follow-up, with a 96% success rate versus 72% for incisionless otoplasty, due to better structural support from conchal cartilage resection and Mustardé 14 sutures. 90 A 2023 retrospective study of 156 patients found the transcutaneous fixation-assisted method reduced operative time (80.37–60.40 min, P < 0.05) while maintaining comparable outcomes at 12 months. 98 Although the Haytoglu 87 method prioritizes speed, consolidative technique otoplasty offers durability, and the transcutaneous technique enhances efficiency; all 3 effectively correct prominent ear deformities.
Table 7. Comparative Otoplasty Technique Studies
| Author | Cartilage Manipulation | Study Details | Fixation Suture | Recurrence Rate, % | Revision Rate, % |
|---|---|---|---|---|---|
| Haytoglu 87 | Sparing | Haytoglu modification of incisionless | Not specified | 0.0 | 0.0 |
| Sparing | Fritsch modification of incisionless | Not specified | 0.0 | 0.0 | |
| Temel 90 | Cutting | Consolidative technique otoplasty | 4-0 Prolene | 3.4 | 2.3 |
| Sparing | Incisionless otoplasty | 3-0 Prolene | 29.0 | 23.2 | |
| Uyar 98 | Sparing | Classical needle-assisted approach | 4-0 Ethibond | 0.0 | 0.0 |
| Sparing | Transcutaneous fixation-assisted method | 4-0 Ethibond | 0.0 | 0.0 |
This practical review of the otoplasty literature spanning more than 100 years, from 1915 to 2024, synthesized findings from 18 studies meeting inclusion criteria (1996–2023) covering 1590 patients and 3060 ears. Cartilage-sparing techniques, particularly the Mustardé–Furnas approach, remain central due to their reliability. Despite refinements, no single technique proved universally superior. Postauricular fascial and dermal flaps showed enhanced long-term stability, while emerging techniques, such as LACR and electromechanical reshaping, offer promising alternatives with reduced morbidity and faster recovery. Further advances in hybrid approaches, suture selection, and postoperative care continue to shape the field toward safer, more predictable outcomes.
A meta-analysis of the included otoplasty studies demonstrated effective reduction in ear prominence, with the mean mastoid-to-helical rim distance decreasing from 27.1 ± 3.3 mm preoperatively to 15.4 ± 2.8 mm postoperatively. The most used sutures for fixation were 4-0 Prolene and 4-0 Ethibond, whereas 5-0 Prolene and 4-0 Monocryl were used for skin closure. Prolene and Nylon sutures, favored for smooth handling and low tissue reactivity, performed comparably to more expensive alternatives. 100 , 101 Recurrence rates were lower with cartilage-sparing methods, whereas cutting techniques had higher revision rates.
The variability in postoperative care protocols following otoplasty reflects a lack of standardized guidelines across different studies. Although most approaches involve an initial dressing, the type and duration of its application vary widely, ranging from occlusive and pressure dressings to gauze pads or bolster dressings, typically removed within a few days to a week. Extended postoperative care predominantly includes headband use, though the duration and frequency differ significantly, with some protocols recommending continuous wear for several weeks and others limiting usage to nighttime. Some studies incorporate adjunctive measures such as passive drains, antibiotic dressings, or compression techniques. However, prolonged headband use beyond 24 hours may not provide additional benefits and could increase complications. 102 , 103
Overall complication rates averaged 14.4%, with suture extrusion (5.4%) being the most common, followed by infection (2.6%), asymmetry (2.1%), and hematoma (1.3%). Severe complications were rare (<1%). Many studies and prior meta-analyses confirmed otoplasty’s safety, though incisionless techniques had higher blistering (22.6%) and suture extrusion (21.9%). 104 – 108 Although advancements continue to refine techniques, optimizing material selection and anchoring methods remain key to improving outcomes and patient safety.
This meta-analysis has several limitations. Most studies (94.4%) were retrospective, with only 1 randomized trial, limiting the strength of conclusions. The predominance of studies from Turkey (66.7%) and inconsistent demographic data (ethnicity, age, aesthetic preferences) restricts generalizability and subgroup analyses. Consequently, the applicability of these results to other populations or auricular deformities beyond prominent ears remains limited.
Publication bias was suggested by Egger test and trim-and-fill analysis. Heterogeneity in recurrence and revision rates persisted, likely due to differences in populations, techniques, and materials. Additionally, recurrence rates were reported according to each study’s own definitions, which introduces variability but preserves fidelity to the original data and allows for transparent, study-level comparison. The average follow-up of 24.5 months limits insight into long-term outcomes. Future research should prioritize diverse, long-term studies with standardized techniques to improve statistical rigor and strengthen conclusions.
This practical review consolidated decades of otoplasty research, summarizing techniques, materials, outcomes, and limitations. The predominance of retrospective studies highlights the need for prospective research. Widely used methods, such as the modified Mustardé–Furnas technique, remain effective, with cartilage-sparing approaches enhancing durability. Advances in sutures, postoperative care, and minimally invasive or laser-assisted techniques reflect the field’s progression. Future work should refine less invasive methods and use animal models to improve surgical precision.
Dr. Janis receives royalties from Springer Publishing and Thieme Medical Publishers. Joseph D. Kaleeny has no financial interest to declare in relation to the content of this article.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
系统检索1915-2024年共1397篇文献,经筛选最终纳入18项研究(1996-2023),合计1590例患者、3060只耳。
的临床回顾/7288867_fig1.jpg)
回顾性纳入12个月内191例连续面部提升术,110例随访≥100天符合纳入(女性107例、男性3例),平均随访404.5天。
前瞻性单盲随机对照试验,30例按Simon分型分为两组各15例。