11点注射联合超声血管定位提升唇部填充安全性与美学
2026年10月21日33 min read
Plastic and Reconstructive Surgery Global Open
结论与实践要点
本研究将 11 点注射技术(11-PIT)与注射前高频超声血管定位相结合,用于透明质酸唇部填充,通过对上、下唇动脉走行与深度的个体化测绘,在高血管风险区(如上红唇缘)优化进针层次与位点,以期在取得自然美学效果的同时降低血管并发症风险。
本研究为单中心前瞻性自身前后对照研究,样本量较小(25 例女性,年龄 21–65 岁),随访 6 月,缺少与传统唇部填充技术的随机或配对队列对照,亦未使用 FACE-Q 等验证量表。文中“较安全、有效”的结论基于本研究观察,长期(>6 月)效果与相对于常规技术的安全性优势仍需更大规模、对照研究进一步验证。
Background:Lip augmentation using hyaluronic acid fillers is a popular cosmetic procedure; however, vascular complications remain a concern. The 11-point injection technique (11-PIT), combined with sonographic vascular mapping, enhances safety by guiding precise filler placement while achieving optimal aesthetic outcomes.
Methods:A prospective study was conducted on 25 female patients (21–65 y) undergoing lip augmentation with Cleviel Volume hyaluronic acid filler. High-frequency ultrasound (Aplio-i700, Canon Medical Systems) was used to measure the depth of superior and inferior labial arteries at 6 key points before injection. The 11-PIT was performed to enhance specific lip landmarks while minimizing vascular risks. Postprocedure assessments included 3-dimensional imaging for volume changes, sonographic analysis for lip thickness and projection, and Global Aesthetic Improvement Scale surveys at 1, 3, and 6 months.
Results:The mean arterial depth at the midline of the upper and lower lips was 2.54 ± 1.89 and 1.91 ± 1.58 mm, respectively, increasing laterally. Lip volume increased immediately postinjection (0.96 ± 0.24 mL) and gradually declined to 0.58 ± 0.17 mL at 6 months. Upper lip thickness increased from 8.94 ± 1.16 to 10.98 ± 1.03 mm at 1 month before regressing. Lip corner elevation was measured at 1.21 ± 0.35 mm at 1 month. Global Aesthetic Improvement Scale scores remained favorable (3.28 ± 0.75 at 6 mo). No major complications occurred.
Conclusions:The 11-PIT, combined with sonographic vascular mapping, provides a safe and effective approach for lip augmentation. This method minimizes vascular risks, enhances aesthetic outcomes, and offers reproducible results, supporting its adoption for safer lip enhancement procedures.
Question: Can sonographic vascular mapping combined with an 11-point injection technique (11-PIT) using Cleviel Volume hyaluronic acid filler improve safety, lip volume, wrinkle reduction, and philtrum projection in Korean patients?
Findings: In this prospective study of 25 participants, preinjection ultrasound mapping improved injection precision, and the 11-PIT demonstrated better aesthetic outcomes than conventional methods, with 3D imaging and sonography confirming sustained lip volume, reduced wrinkle roughness, and philtrum projection at 1 month.
Meaning: Sonographic guidance with 11-PIT offers a safer, more effective, and aesthetically superior method for upper lip rejuvenation using hyaluronic acid filler.
Traditional lip augmentation techniques, such as depot or serial puncture methods, often lack consistency in filler placement and carry a higher risk of vascular compromise due to anatomical variability and blind injections. 1 , 2 Achieving symmetrical outcomes and maintaining natural-looking contours is particularly challenging in the upper lip, given its thin vermilion border and proximity to the superior labial artery. 3 Hyaluronic acid (HA) fillers remain popular for enhancing lip volume and aesthetics due to their safety, reversibility, and effectiveness, 1 – 3 but complications such as vascular occlusion can still occur. 4 – 7 A thorough understanding of lip vascular anatomy and precise injection techniques is therefore essential. 8 , 9
The 11-point injection technique (11-PIT) was developed to provide a reproducible, anatomically guided approach targeting key aesthetic landmarks, including the Cupid bow, vermilion tubercles, philtral columns, and oral commissures. By incorporating preinjection sonographic vascular mapping, 11-PIT minimizes vascular risks and enhances safety in high-risk zones while allowing tailored volumization, philtral projection, and commissure elevation—outcomes often difficult to achieve with conventional methods. 4 , 5 The fixed-point strategy enables greater control, symmetry, and predictability across different patient anatomies.
This prospective study evaluated the 11-PIT combined with high-frequency ultrasound mapping to identify the depth and position of the superior and inferior labial arteries before filler placement. Outcomes were assessed with 3-dimensional (3D) imaging for volume changes and the Global Aesthetic Improvement Scale (GAIS) at 1, 3, and 6 months, offering a practical and standardized approach for consistent, natural results.
Twenty-five female patients undergoing lip augmentation were selected at a single clinic for this prospective study. All patients received detailed preprocedure counseling regarding the 11-PIT combined with ultrasound-guided vascular mapping. Counseling included an explanation of the need for at least 2 sonographic assessments (preinjection mapping and postinjection evaluation), the associated additional costs, and the benefits of improved procedural safety, accuracy, and reduced risk of complications. Patients provided informed consent after understanding these factors, ensuring transparency in both medical and financial aspects. Exclusion criteria included patients with lip skin diseases, prior permanent filler injections, hypersensitivity to lidocaine or HA fillers, bleeding disorders, severe allergies, immunodeficiency, mental health disorders, illiteracy, pregnancy or breastfeeding, and any condition deemed unsuitable by the researcher. Ethical approval was granted by the public institutional review board designated by the Ministry of Health and Welfare, Republic of Korea (approval no. P01-202404-01-047), and all participants provided written informed consent.
Cleviel Volume HA filler (Pharma Research, Seoul, Korea), a monophasic high-cohesivity filler with a high elastic modulus ( G ′ ~ 470 Pa), was used for lip augmentation. This property allows precise shaping and projection, particularly for defining the vermilion border and philtrum ridges. Patients agreed to avoid other lip filler procedures during the study and to attend 4 follow-ups. Sonographic assessments at 1, 3, and 6 months evaluated filler presence, volume, and location, with findings correlating to clinical retention and 3D imaging. GAIS and 3D volume analyses were performed by an independent, blinded evaluator.
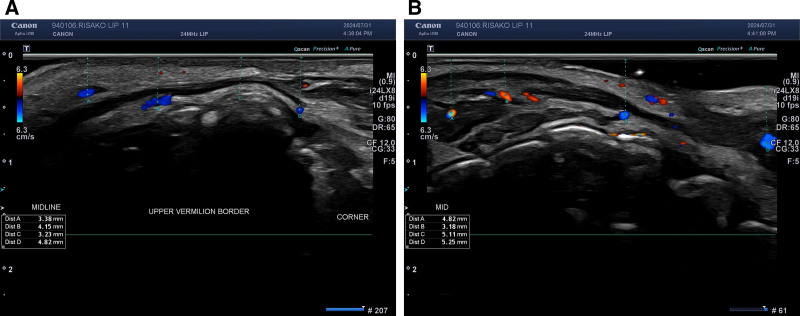
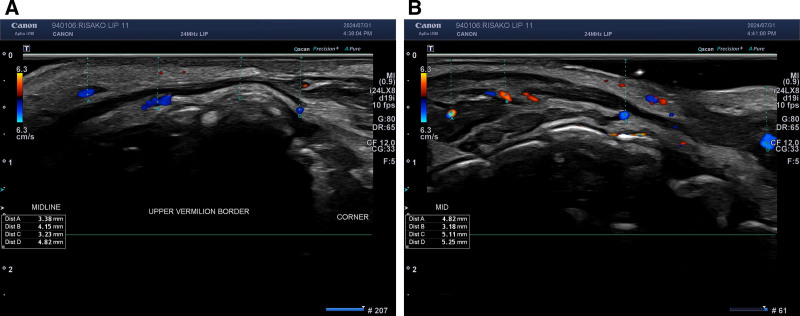
Before filler injection, the depth of the superior and inferior labial arteries was measured using a high-resolution ultrasound (Aplio i700, Canon Medical Systems, Japan) with a 24-MHz, 41-mm linear PLI-2004BX probe. 10 Preinjection vascular mapping, conducted with a certified ultrasound expert from Canon Medical Korea, ensured measurement accuracy and minimized operator bias. Measurements from the upper and lower vermilion borders to the respective labial arteries were obtained to create a detailed arterial depth map for safer injection planning (Fig. 1 ):
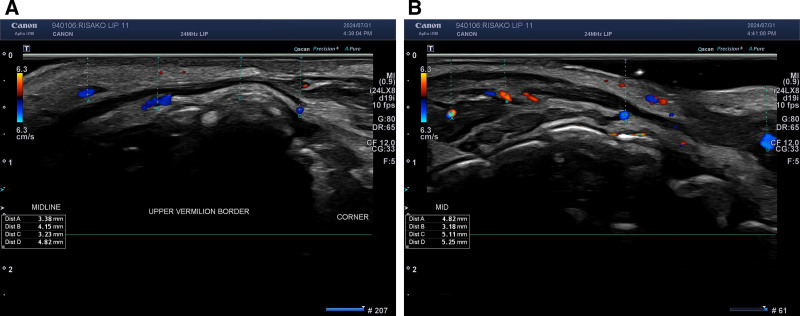
Fig. 1. Ultrasound vascular mapping of the superior and inferior labial artery along the vermilion border. Before the filler injection, the depth of the superior (A) and inferior labial artery (B) was measured using a high-resolution ultrasound machine. Measurements were taken from the upper vermilion border to the superior labial artery and from the lower vermilion border to the inferior labial artery at 6 points.- Midline (A1): Center of the lip.
The 11-PIT is designed to enhance lip aesthetics while minimizing risks. The procedure involves specific injection points and methods. ( See figure, Supplemental Digital Content 1 , which displays the 11-PIT, which is designed to enhance lip aesthetics while minimizing risks. Point 1: upper vermilion border enhancement on the right side. Point 2: upper vermilion border enhancement on the left side. Point 3: upper central tubercle enhancement. Point 4: right upper lateral tubercle enhancement. Point 5: left upper lateral tubercle enhancement. Point 6: right lower lip tubercle enhancement. Point 7: left lower lip tubercle enhancement. Point 8: right oral commissure support. Point 9: left oral commissure support. Point 10: right philtrum column and Cupid bow enhancement. Point 11: left philtrum column and Cupid bow enhancement, https://links.lww.com/PRSGO/E686.) ( See Video 1 [online] , which displays the step-by-step guide to the 11-PIT for lip augmentation.) The 11-point technique is an evolution of the previously validated 9-point method, with the addition of 2 philtral injection points to enhance vertical lip projection and upper lip rejuvenation.
补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)gox-14-e7520-s001.mp4Video 1. This video demonstrates the 11-Point Injection Technique (11-PIT), including targeted injections along the upper vermilion border, central tubercle, lower lip tubercles, oral commissures, and philtral columns. The structured sequence highlights how each point contributes to balanced lip shaping while minimizing vascular risk and preventing filler migration.
Each subject received 1.0 mL of Cleviel Volume (22 mg/mL HA) via the 11-PIT using a 29G 1-inch needle in a slow submucosal LT fashion. The endpoint was satisfactory projection and symmetry without blanching, excessive resistance, or vascular compromise; minimal molding was performed only if needed. Volume distribution: points 1 and 2: 0.1 mL each; point 3: 0.05 mL; points 4 and 5: 0.05 mL each; points 6 and 7: 0.2 mL each; points 8 and 9: 0.05 mL each; points 10 and 11 (philtrum): 0.05 mL each. No botulinum toxin was administered during the study.
Lip volume was measured before and after the procedure at each follow-up using the LifeViz Mini 3D camera system (QuantifiCare, France). This system provides high-resolution standardized images for accurate volume assessment, with software calculating changes by comparing pre- and postinjection lip outlines. 11 – 15 The noncontact 3D scanning method is safe, noninvasive, and cost-efficient.
Lip corner lifting was evaluated using the 3D camera system, 3 which captures high-resolution standardized images for precise volumetric and spatial analysis. Lip corner height, measured relative to the commissures and adjacent vermilion border, was recorded at baseline and at 1, 3, and 6 months. Vertical displacement in millimeters was calculated by comparing pre- and postinjection images.
Upper vermilion border height at 3 points (A2, A3, A4) was measured using high-resolution 3D imaging. 3 , 16 The software calculated augmentation by comparing pre- and postinjection values under standardized positioning, lighting, and angle conditions.
Volumetric changes in the lower lip tubercle were measured at 3 time points using high-resolution 3D imaging with standardized lighting, angle, and distance settings. 11
The distance from the upper vermilion border to the upper central incisor and from the lower vermilion border to the lower central incisor was measured using ultrasound imaging. These measurements were taken pre- and postfiller injection to assess changes in lip thickness and projection. 17 , 18
HA filler was injected into the philtrum to improve height and projection. Elevation was measured at the lower one-third using high-resolution ultrasound and validated with volumetric 3D imaging at baseline and at 1, 3, and 6 months to ensure precision and reproducibility.
Fine wrinkle depth on the upper and lower lips was evaluated using high-resolution 3D imaging and Gwyddion 2.62 roughness analysis at baseline and at 1, 3, and 6 months postinjection. Measurements were taken along imaginary lines from the midline to the mouth corner under standardized lighting, distance, and environmental conditions. Roughness analysis quantified wrinkle depth in micrometers, capturing surface topography to assess temporal changes. 19 – 24
Patient satisfaction with lip fullness and shape was assessed using the GAIS immediately postprocedure and at 1, 3, and 6 months. Additional surveys evaluated perceived changes in lip corner elevation and philtrum prominence.
The depth measurements of the superior and inferior labial arteries provided critical data for safe injection planning. SDs ranged from ±1.23 to ±2.21 mm, indicating variability in arterial depth among patients. This variability underscores the importance of individualized vascular mapping (Fig. 2 ) (Table 1 ). The average arterial depths at key points were as follows:
Table 1. Depth of Superior and Inferior Labial Artery
| A1 | A2 | A3 | A4 | A5 | A6 | |
|---|---|---|---|---|---|---|
| Superior labial artery | ||||||
| mm | 2.549 | 3.396 | 3.074 | 3.695 | 4.375 | 6.620 |
| SD | 1.898 | 1.438 | 1.236 | 1.292 | 2.097 | 2.118 |
| Inferior labial artery | ||||||
| mm | 1.914 | 3.406 | 3.954 | 3.846 | 4.492 | 5.785 |
| SD | 1.585 | 1.756 | 1.961 | 1.644 | 2.014 | 2.014 |
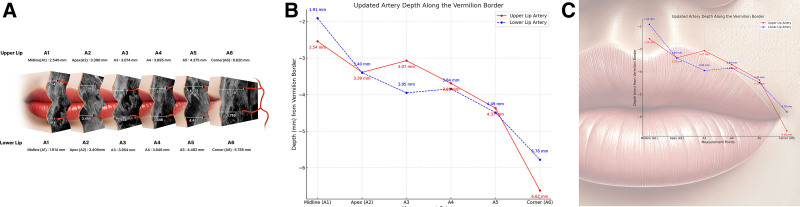
Fig. 2. Sonographic depth analysis of superior and inferior labial arteries along the vermilion border. A, Sonographic measurements of the superior and inferior labial arteries at 6 key points—midline (A1), Apex (A2), A3, A4, A5, and corner (A6)—demonstrate individual variability in arterial depth relative to the vermilion border. B and C, Depth values are shown in millimeters, with the superior labial artery indicated by a red line and the inferior labial artery by a blue dashed line, providing essential anatomical guidance for safe injection planning.- Upper lip:Midline (A1): 2.54 ± 1.89 mmApex (A2): 3.39 ± 1.43 mmA3: 3.07 ± 1.23 mmA4: 3.69 ± 1.29 mmA5: 4.37 ± 2.09 mmCorner (A6): 6.62 ± 2.11 mm
At 1 month postinjection, the average lip volume increased by 0.96 ± 0.24 mL, reflecting a noticeable enhancement. At 3 months, the volume reduced slightly to 0.86 ± 0.27 mL, indicating some natural regression. By 6 months, the volume further declined to 0.58 ± 0.17 mL. These results demonstrate an immediate increase in lip volume postprocedure, with a gradual decline during the 6-month period, consistent with the typical behavior of HA fillers as they integrate with the tissue and degrade naturally (Table 2 ) (Figs. 3 , 4 ). ( See Video 2 [online] , which displays the real-time 3D and sonographic assessment of lip augmentation in a 33-year-old woman.)
Table 2. Lip Volume Changes in 3D Imaging Analysis
| 1 mo | 3 mo | 6 mo | |
|---|---|---|---|
| 3D volume, mL | 0.96 | 0.86 | 0.58 |
| SD | 0.24 | 0.27 | 0.17 |
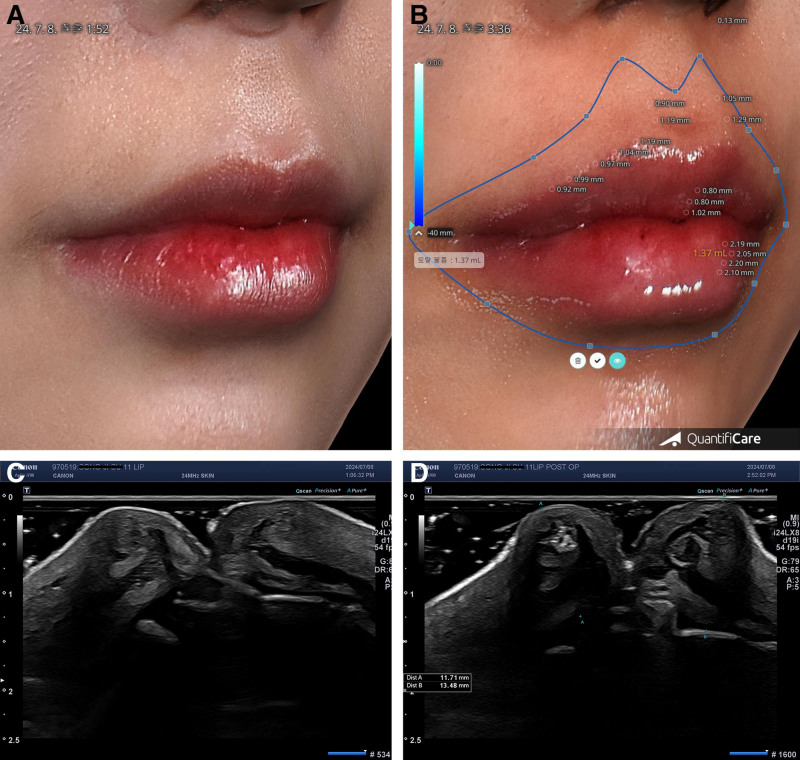
Fig. 3. Lip volume changes in 3D imaging analysis and lip thickness and projection in sonography for a 33-year-old woman (see Video 2 [online]). A, Pretreatment 3D imaging of the lips. B, Volume analysis in a 3D image immediately after HA filler injection, showing an increase in total lip volume to 1.37 mL. C, Preinjection sonographic image of the lips. D, After HA filler injection, the upper lip thickness, measured from the incisor to the upper vermilion border, was 11.71 mm, whereas the lower lip thickness was 13.48 mm, confirming successful volumization and projection enhancement postinjection.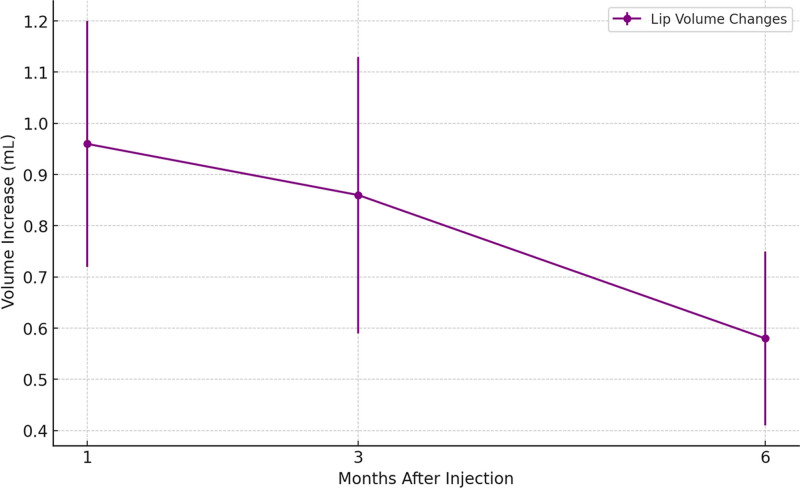
Fig. 4. Lip volume, assessed using 3D volumetric analysis, demonstrated a progressive decrease over time following HA injection. The mean volume increase was 0.96 mL at 1 month, 0.86 mL at 3 months, and 0.58 mL at 6 months. SDs were 0.24, 0.27, and 0.17 mL, respectively.补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)gox-14-e7520-s002.mp4Video 2. This video demonstrates the volumetric and structural changes in the lips following HA filler injection using 3D imaging and high-frequency ultrasound. The 3D analysis visualizes the enhanced lip contour and increased volume immediately post-injection. The sonographic imaging confirms the precise placement of the filler in the submucosal layer, with upper lip thickness measured at 11.71 mm and lower lip thickness at 13.48 mm. This combined imaging approach provides an objective evaluation of the augmentation effects, highlighting the safety and efficacy of the procedure.
Upper vermilion border augmentation demonstrated a gradual decrease over time but maintained significant improvements compared with baseline. At 1 month postinjection, the mean augmentation was 1.40 ± 0.40 mm. By 3 months, this decreased slightly to 1.23 ± 0.37 mm, and at 6 months, the height was 1.07 ± 0.74 mm. These data underscore the efficacy of HA injection in achieving and maintaining aesthetic improvement of the upper vermilion border over time (Table 3 ) (Figs. 3 B, 5 ).
Table 3. Upper Vermilion Border Augmentation Assessment in 3D Imaging Analysis
| 1 mo | 3 mo | 6 mo | |
|---|---|---|---|
| Upper vermilion border augmentation, mm | 1.40 | 1.23 | 1.07 |
| SD | 0.40 | 0.37 | 0.74 |
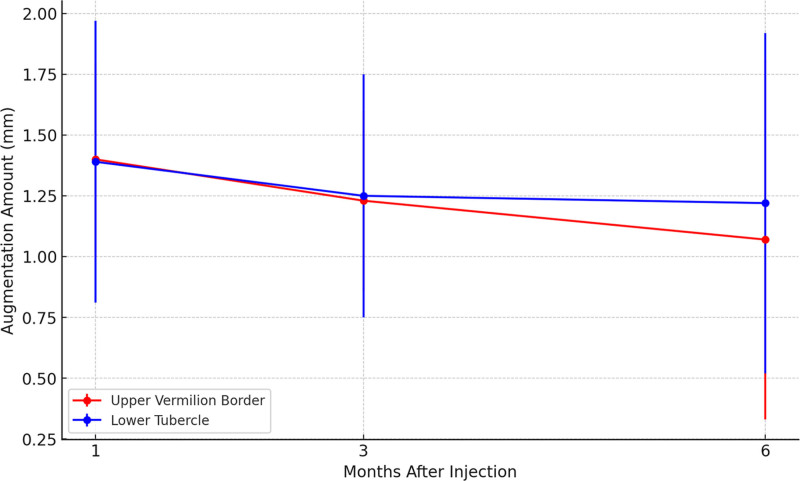
Fig. 5. The augmentation amounts of the upper vermilion border and lower tubercle were analyzed using 3D imaging. The upper vermilion border showed a decrease in augmentation from 1.40 mm at 1 month to 1.23 mm at 3 months and 1.07 mm at 6 months, with SDs of 0.40, 0.37, and 0.74 mm, respectively. Similarly, the lower tubercle showed values of 1.39, 1.25, and 1.22 mm at 1, 3, and 6 months, with corresponding SDs of 0.58, 0.50, and 0.70 mm. These findings indicate a gradual reduction in augmentation during the 6-month period.
The lower lip tubercle showed significant augmentation at all time points compared with baseline. At 1 month postinjection, the mean augmentation was 1.39 ± 0.58 mm. By 3 months, the augmentation slightly decreased to 1.25 ± 0.50 mm, and at 6 months, it measured 1.22 ± 0.70 mm (Table 4 ).
Table 4. Lower Lip Tubercle Augmentation Assessment in 3D Imaging Analysis
| 1 mo | 3 mo | 6 mo | |
|---|---|---|---|
| Lower lip tubercle augmentation, mm | 1.39 | 1.25 | 1.22 |
| SD | 0.58 | 0.50 | 0.70 |
Interestingly, the pattern of augmentation observed in the lower lip tubercle aligns with the trends noted in the upper vermilion border, further supporting the reliability of the 3D imaging method used for these analyses (Figs. 3 B, 5 ).
At baseline, the upper lip thickness was measured at 8.94 ± 1.16 mm, which increased to 10.98 ± 1.03 mm at 1 month. At 3 months, the thickness slightly decreased to 10.44 ± 1.04 mm, and by 6 months, it measured 9.67 ± 2.21 mm. These findings indicate an initial increase in lip thickness postinjection, with gradual regression during the 6-month follow-up period.
For the lower lip, baseline thickness was 10.30 ± 1.29 mm, increasing to 12.25 ± 1.54 mm at 1 month. At 3 months, the thickness was maintained at 12.16 ± 1.62 mm, and at 6 months, it decreased slightly to 11.52 ± 1.54 mm. This pattern suggests that the filler provided sustained enhancement of lower lip projection over the observation period (Table 5 ) (Figs. 3 , 6 , 7 ).
Table 5. Lip Thickness and Projection Amount in Sonography
| Upper Lip | Lower Lip | |
|---|---|---|
| Before | 1 mo | |
| Lip (mm) thickness | 8.94 | 10.98 |
| SD | 1.16 | 1.03 |
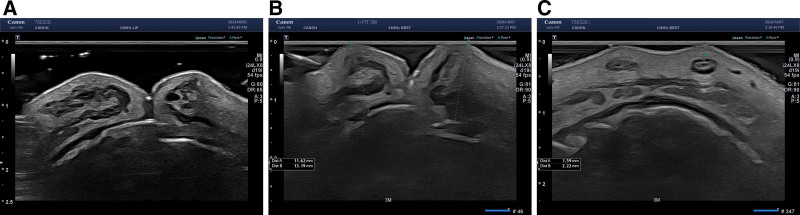
Fig. 6. Sonographic analysis of lip thickness and philtrum projection after HA filler injection in a 35-year-old woman. A, Preinjection. B, Three months postinjection, the upper lip thickness measured 11.62 mm, whereas the lower lip thickness reached 13.19 mm, indicating substantial augmentation following the procedure. C, Philtrum augmentation assessment at 3 months postinjection, where the right philtrum height was 1.59 mm, and the left philtrum height was 2.22 mm, demonstrating filler integration and structural enhancement.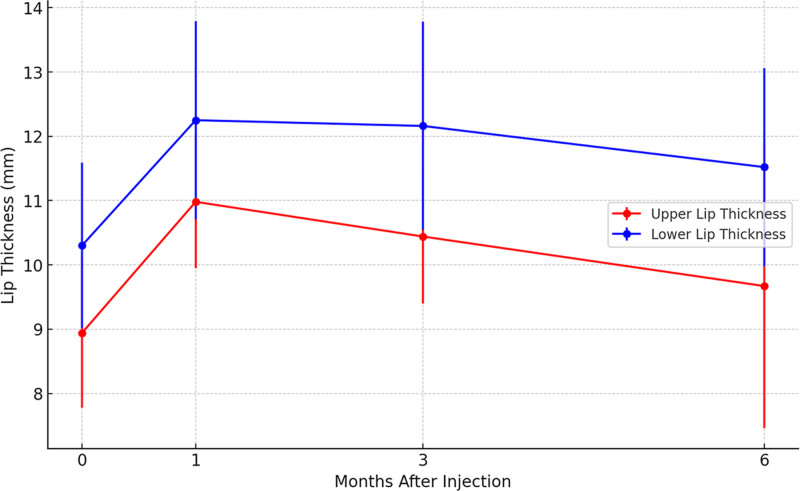
Fig. 7. Sonographic evaluation revealed changes in lip thickness following HA injection. The upper lip thickness increased from 8.94 mm at baseline to 10.98 mm at 1 month, followed by a slight decrease to 10.44 mm at 3 months and 9.67 mm at 6 months. The corresponding SDs were 1.16, 1.03, 1.04, and 2.21 mm, respectively. Similarly, the lower lip thickness increased from 10.30 mm at baseline to 12.25 mm at 1 month, slightly decreasing to 12.16 mm at 3 months and 11.52 mm at 6 months, with SDs of 1.29, 1.54, 1.62, and 1.54 mm. These results highlight a transient increase in lip thickness that diminishes over 6 months.
Lip corner lifting was objectively quantified through 3D imaging analysis. The average vertical displacement of the lip corners was measured to be 1.21 ± 0.35 mm at 1 month, 1.08 ± 0.64 mm at 3 months, and 0.82 ± 58 mm at 6 months postinjection compared with baseline. These results indicate an aesthetic improvement in lip corner positioning using only HA filler injection, contributing to a more youthful and lifted appearance. The consistent elevation observed across follow-up visits underscores the effectiveness of HA fillers in addressing structural lip changes ( P > 0.05) (Table 6 ).
Table 6. Lip Corner Lifting Amount in 3D Imaging Analysis
| 1 mo | 3 mo | 6 mo | |
|---|---|---|---|
| Lifting amount, mm | 1.21 | 1.08 | 0.82 |
| SD | 0.35 | 0.64 | 0.58 |
The philtrum height showed significant elevation following HA filler injection, as assessed by ultrasound imaging. The average height at 1 month postinjection was 1.88 ± 0.58 mm, decreasing to 1.51 ± 0.56 mm at 3 months and 1.08 ± 0.41 mm at 6 months. These values indicate a gradual regression over time while maintaining noticeable enhancement compared with baseline (Table 7 ) (Fig. 7 ).
Table 7. Philtrum Enhancement Amount in Sonography
| 1 mo | 3 mo | 6 mo | |
|---|---|---|---|
| HA height on philtrum, mm | 1.88 | 1.51 | 1.08 |
| SD | 0.58 | 0.56 | 0.41 |
Validation: the 3D imaging results closely aligned with ultrasound findings, demonstrating philtrum elevations of 0.91 ± 0.64 mm at 1 month, 0.86 ± 0.45 mm at 3 months, and 0.61 ± 0.40 mm at 6 months. This consistency across modalities confirms the sustained effects of the filler and the reliability of the measurements (Table 8 ) (Figs. 3 B, 9 ).
Table 8. Philtrum Enhancement Amount in 3D Imaging Analysis
| 1 mo | 3 mo | 6 mo | |
|---|---|---|---|
| Philtrum enhancement amount, mm | 1.04 | 0.89 | 0.66 |
| SD | 0.54 | 0.45 | 0.40 |
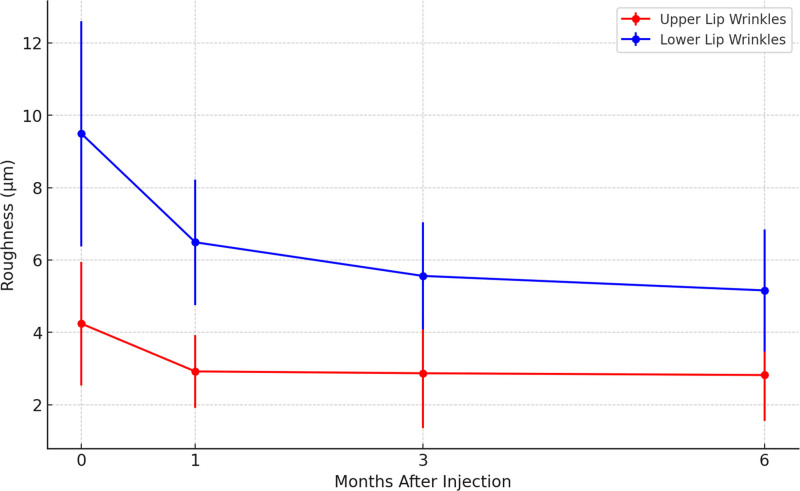
Fig. 8. Improvement of fine wrinkles on the upper and lower lips using roughness analysis. The mean roughness of the upper lip decreased from 4.24 μm at baseline to 2.92 μm at 1 month, 2.87 μm at 3 months, and 2.82 μm at 6 months, with corresponding SDs of 1.71, 1.01, 1.52, and 1.27 μm, showing roughness reduction. Similarly, lower lip roughness decreased from 9.49 μm at baseline to 6.49 μm at 1 month, 5.56 μm at 3 months, and 5.16 μm at 6 months, with SDs of 3.11, 1.73, 1.48, and 1.69 μm.
Following HA injection, upper lip wrinkle depth decreased from 4.24 μm at baseline to 2.92 at 1 month, 2.87 at 3 months, and 2.82 at 6 months. Lower lip depth improved from 9.49 μm at baseline to 6.49, 5.56, and 5.16 μm at 1, 3, and 6 months, respectively. Despite gradual filler volume reduction, wrinkle roughness (Rz) continued to improve, likely due to HA-induced hydration, fibroblast activation, and superficial dermal remodeling. Measurements were obtained via Gwyddion 3D analysis software, with “roughness” used synonymously with wrinkle depth to indicate surface topography rather than histological depth (Fig. 8 ) (Table 9 ).
Table 9. Fine Wrinkle Improvement by Roughness Statistical Analysis
| Upper Lip | Lower Lip | |
|---|---|---|
| Before | 1 mo | |
| Roughness, µm | 4.24 | 2.92 |
| SD | 1.71 | 1.01 |
Mean GAIS scores for lip shape satisfaction were highest immediately postprocedure (4.35 ± 0.49) and decreased to 3.89 ± 0.83 at 1 month, 3.50 ± 0.51 at 3 months, and 3.28 ± 0.75 at 6 months. At 6 months, 88% of patients remained satisfied. Improvements in lip corner elevation and philtrum prominence contributed to overall satisfaction, suggesting both aesthetic and functional benefits (Figs. 9 , 10 ). ( See Video 3 [online] , which displays the comparison of lip augmentation results at 1 and 6 mo posttreatment.)
补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)gox-14-e7520-s003.mp4Video 3. This video illustrates the changes in lip volume and structure following HA filler injection, comparing results at 1 month and 6 months post-procedure. The 3D imaging analysis quantifies volumetric retention over time, showing an initial enhancement at 1 month with gradual integration and natural regression by 6 months. The sonographic evaluation confirms the filler placement within the submucosal layer, providing objective evidence of sustained augmentation effects. This dynamic assessment highlights the longevity and efficacy of HA fillers in lip enhancement.
No major adverse events occurred. Minor reactions, such as transient swelling and bruising at injection sites, resolved spontaneously within 2–3 days, and no palpable nodules, prolonged edema, or tenderness were noted. The use of ultrasound mapping likely contributed to the absence of vascular complications (Fig. 11 ).
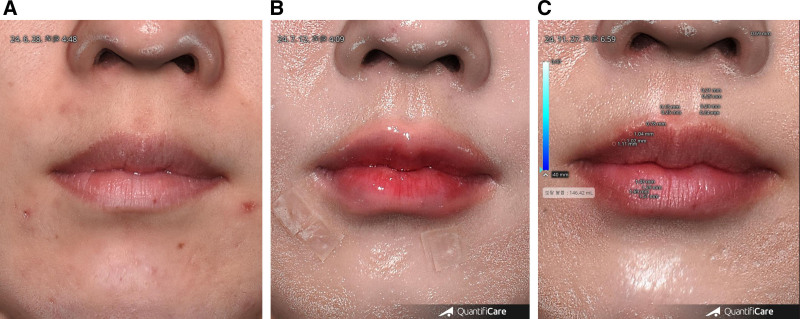
Fig. 9. Longitudinal evaluation of lip augmentation: 3D volume analysis and sonographic confirmation for a 36-year-old woman (see Video 3 [online]). A, Pretreatment. B, One month postinjection, significant volume enhancement is observed with improved lip contour. C, Six months postinjection, the augmentation effect is still evident but shows gradual regression consistent with the natural HA degradation.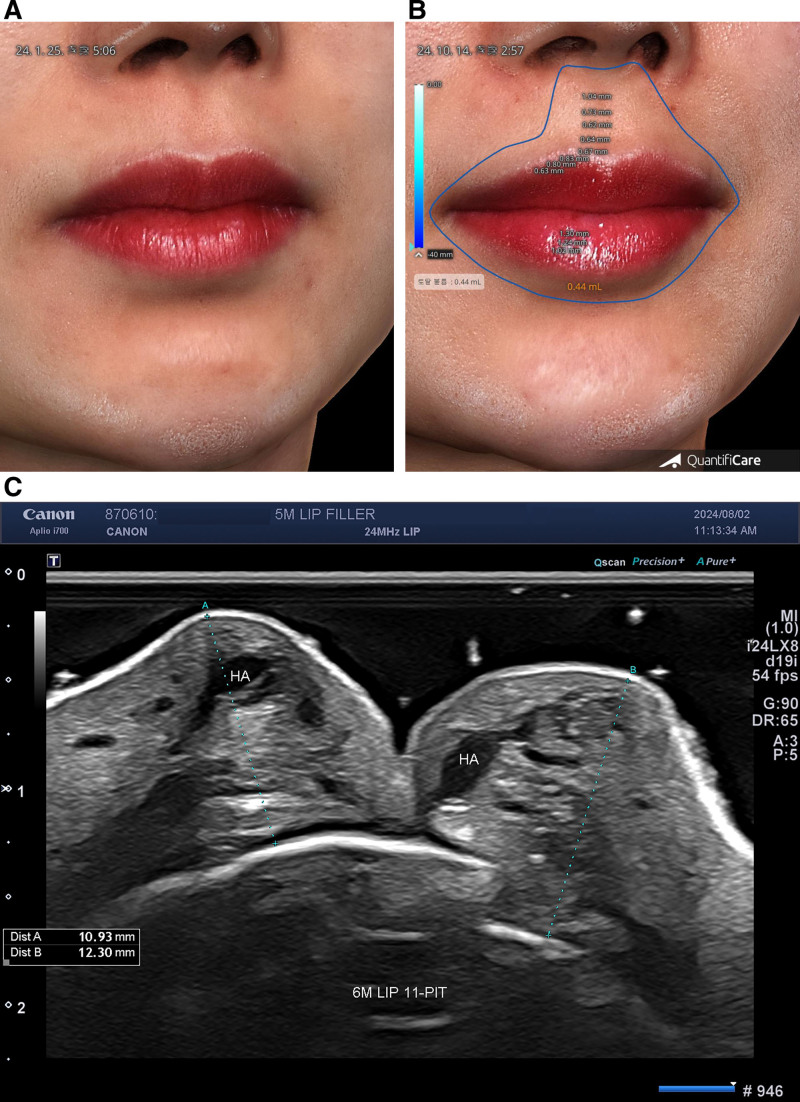
Fig. 10. Long-term effects of HA fillers in lip augmentation: 3D and ultrasound analysis at 6 months in a 37-year-old woman. A, Pretreatment. B, Six months posttreatment, 3D imaging analysis demonstrates sustained augmentation effects in both the upper and lower lips, with maintained volume enhancement. C, Ultrasound imaging at 6 months posttreatment reveals persistence of injected HA filler within the submucosal layer of both the upper and lower lips.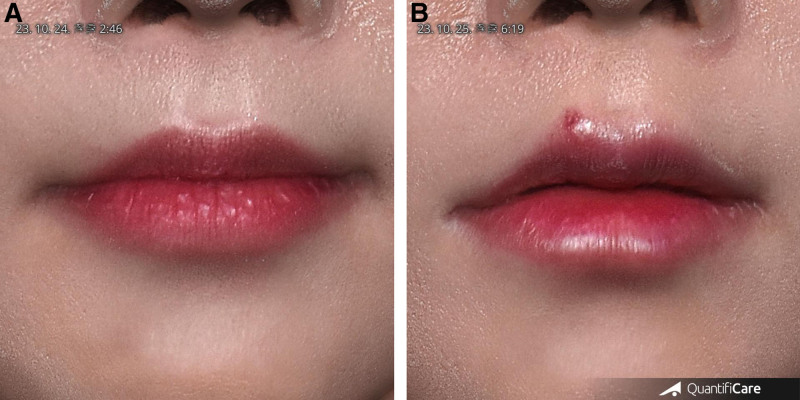
Fig. 11. Mild bruising on the upper lip after injection in a 32-year-old woman, resolving within a week. A, Before. B, One-day postinjection, a mild bruising developed on the upper lip following HA filler injection, and the bruise gradually subsided and fully resolved within a week without intervention.One 31-year-old woman experienced delayed swelling of both lips approximately 6 months postinjection, triggered by a COVID-19 infection. The reaction, lasting several weeks, was presumed to result from an immune-mediated inflammatory response between the severe acute respiratory syndrome coronavirus 2 spike protein and the existing HA filler. Similar delayed-type hypersensitivity reactions have been reported after systemic triggers, including viral infections or vaccinations. This case highlighted the need for continued monitoring and individualized risk–benefit assessment in filler-treated patients during infectious disease outbreaks. The delayed swelling was managed conservatively with oral corticosteroids and antihistamines, without the need for hyaluronidase, as symptoms gradually resolved. In similar cases, hyaluronidase could be considered if persistent or severe.
The lips possess a dense and variable vascular network, and inadvertent intravascular injection can cause severe complications such as necrosis or embolism. High-frequency ultrasound enabled accurate mapping of the superior and inferior labial arteries, whose depth and course differ between individuals. Measuring arterial depth at key points allowed for tailored injection planning to minimize vascular injury risk. 25 – 29 Although no control group using conventional lip filler techniques was included, future within-subject or matched-cohort studies are needed to compare the safety, reproducibility, and aesthetic outcomes of 11-PIT with standard protocols. Clinical injection depth was individualized based on real-time ultrasound findings to accommodate anatomical variability.
The 11-PIT is a structured, anatomically guided method for lip augmentation, targeting the tubercles, oral commissures, and philtrum. Developed through anatomical dissections, sonographic mapping, and clinical experience, it combines individualized planning, vascular safety, and natural results. Lip corner elevation was achieved by volumizing points 8 and 9. Despite HA degradation, improvements over 6 months suggest added benefits from structural support and fibroblast activation. Compared with traditional techniques, the 11-PIT yields reproducible results and reduces vascular risk. Limitations include the need for vascular sonoanatomy familiarity and the absence of comparative trials. Larger randomized studies are needed to confirm its long-term efficacy.
Combining ultrasound vascular mapping with the 11-PIT minimized risks in lip augmentation. Preinjection mapping improved anatomical awareness, particularly in high-risk zones such as the upper vermilion border, enabling safer site and depth selection to reduce vascular occlusion risk. Controlled filler placement avoided overfilling and ensured even distribution, preventing unnatural outcomes. No nodules, inflammation, or filler hardening occurred during follow-up, underscoring the safety, reliability, and natural aesthetic results achieved with the HA filler used in this study. 4 , 30 , 31
Traditional lip augmentation often overlooks anatomical variation. This study demonstrated that personalized planning with advanced imaging improves safety and outcomes. 1 , 3 , 32 – 35 Although GAIS measured satisfaction, future research should include validated tools such as the FACE-Q. Although Cleviel Volume, a biphasic HA filler, was used here, the 11-PIT principles can be applied to other fillers with rheological adjustment. The author’s prior 9-point technique with a monophasic filler also achieved favorable results, underscoring the versatility of tailored injection designs. Comparative studies across filler types are warranted. Future randomized controlled or matched-cohort studies comparing the 11-PIT with conventional techniques are warranted.
The combination of sonographic vascular mapping and the 11-PIT provides a safe, anatomically informed, and aesthetically effective approach to lip augmentation. This method minimizes vascular risk while achieving natural, youthful results, and is straightforward enough for broad clinical adoption. High patient satisfaction, reliable 6-month outcomes—particularly in upper lip enhancement and philtral projection—and minimal complications support its efficacy. Larger, controlled studies are warranted to further validate these findings and inform standardized guidelines.
The author has no financial interest to declare in relation to the content of this article.
The author thanks all the patients who participated in this study and the staff at Kim Jong Seo Plastic Surgery Clinic for their support. The author also expresses gratitude to all doctors in the Botox-Filler-Thread lifting of the Korea Plastic and Reconstructive Surgery Society for their support.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
前瞻性研究纳入 25 例 21–65 岁女性,接受 Cleviel Volume 透明质酸(1.0 mL,22 mg/mL)的 11 点注射(11-PIT)并联合高频超声血管定位进
研究类型:回顾性单臂观察性研究(单作者、单中心),共纳入 20 例水平颈纹患者(女 14 例、男 6 例),平均年龄 35.4 岁(27–59 岁),Fitzpatrick II–
本研究为一项前瞻性研究,纳入25例韩国女性,采用透明质酸(Cleviel Volume)行唇部填充,结合注射前高频超声对上下唇动脉深度进行6点测绘。