基于影像解剖的男性乳腺发育内镜微创手术要点
2026年10月6日30 min read
Aesthetic Plastic Surgery
结论与实践要点
解剖要点: 男性乳腺血供以胸外侧动脉(41.9%)与胸廓内动脉穿支为主,约25%无明确优势动脉;NAC 灌注高度依赖乳头下浅静脉丛(本组54例缺血中67.9%术中未见该丛)。吸脂与切除中应保留乳腺边缘、避免损伤浅静脉系统,并以约3 mm 厚度经浅筋膜返折处理乳晕下组织——过薄易损及 NAC 真皮血供或致乳头内陷。
神经与美学: 第4肋间神经外侧支(乳腺4点/8点方位)是 NAC 感觉主要来源;避免下外侧象限过度吸脂、保留足够外侧皮瓣厚度可维护感觉,本组未出现显著感觉缺失,住院期麻木多在3个月后改善。吸脂沿“双平面”深层(Scarpa 筋膜深面)保留均匀脂肪垫,利于皮肤回缩与自然轮廓。
局限与沟通: 本研究为单中心、单臂、初步报告,缺乏客观神经感觉测量与长期随访;NAC 坏死虽罕见(0.3%),但需警惕术后加压过紧叠加静脉淤滞。建议结合术前影像标记关键血管,对重度(Simon III)者重视下皱襞韧带释放以防皮褶,并在知情同意中如实说明感觉恢复所需时间。
BackgroundTraditional surgical approaches for gynecomastia are associated with significant trauma and insufficient protection of anatomical structures. Currently, endoscopic glandular excision has emerged as the primary treatment modality. A refined anatomical approach for endoscopic minimally invasive surgery is proposed, with evaluation of postoperative complications and aesthetic outcomes.
MethodsThis study is a single-center, single-arm prospective investigation that collected and analyzed clinical data from patients who underwent endoscopic mastectomy at The First Hospital of Hebei Medical University, aiming to evaluate postoperative complications and patient recovery outcomes with an emphasis on the refined anatomical approach.
ResultsA total of 786 patients were included. The mean operative time was 117.8 ± 20.0 minutes, and the mean discharge time was 3.0 ± 0.7 days. Major complications included hematoma ( n = 4, 0.5%) and nipple-areolar complex ischemia ( n = 54, 6.9%). Among these, 52 cases of nipple-areolar complex ischemia resolved during follow-up, while 2 case progressed to necrosis (0.3%). Nipple-areolar complex sensation scores were 8.5 ± 2.0 (unilateral) and 8.0 ± 1.8 (bilateral). All procedures were completed without conversion to open surgery or significant intraoperative bleeding.
ConclusionEndoscopic glandular excision, through meticulous vascular and neural preservation, effectively restores the natural contour of the male chest while minimizing complications. This approach offers a safe and aesthetically favorable solution for gynecomastia patients.
Level of Evidence IIIThis journal requires that authors assign a level of evidence to each article. For a full description of these Evidence-Based Medicine ratings, please refer to the Table of Contents or the online Instructions to Authors www.springer.com/00266.
Supplementary InformationThe online version contains supplementary material available at https://doi.org/10.1007/s00266-026-06124-3.
Keywords: Case series、Gynecomastia、Refined anatomy、Endoscopic minimally invasive surgery、Nipple-areolar complex sensation
Current surgical options for gynecomastia include liposuction with rotary resection, periareolar open excision, liposuction with periareolar open excision, and endoscopic glandular excision [ 1 – 5 ]. Traditional methods often neglect critical anatomical structures, increasing postoperative risks. In contrast, endoscopic excision provides enhanced visualization, minimal trauma, concealed incisions, and thorough gland removal, establishing it as a common surgical approach for gynecomastia management in current clinical practice.
With the widespread adoption of ultra-high-definition endoscopic systems and advancements in surgeons’ technical expertise in endoscopic breast surgery, optimizing precise fascial anatomical principles to enhance operative refinement has emerged as a pressing challenge in contemporary breast surgery. Drawing on our institutional experience of over 2000 endoscopic glandular excision procedures for gynecomastia, this study elucidates the clinical significance of vascular preservation, neural protection, and layered fascial dissection in achieving surgical refinement through the clinical application of meticulous fascial anatomy in endoscopic male breast surgery.
The sample size was determined using the formula for single-arm study design. Based on a previous meta-analysis of surgical approaches for gynecomastia [ 6 ], the success rate with a complication-free outcome exceeded 87%. The significance level (α) was set at 0.025, and statistical power (1-β) at 80%. With these parameters, the calculated required sample size was n = 316.
This study included clinical records of patients who underwent endoscopic mastectomy between January 2024 and December 2024 at the Breast and Thyroid Disease Center of The First Hospital of Hebei Medical University. Data included general clinical information, operative details (duration, complications).
Inclusion criteria: preoperative diagnosis of gynecomastia via breast ultrasound or chest CT. Exclusion criteria: incomplete records or loss to follow-up.
Patient follow-up was conducted via telephonic interviews or outpatient clinic reviews. Nipple-areolar complex(NAC) sensation was self-assessed using a 0-10 numerical scale (0: complete anesthesia; 10: normal sensation). The follow-up period concluded on February 28, 2025.
All participants underwent standardized preoperative physician-patient communication, with surgical approaches collaboratively determined by both patients and surgeons. Written informed consent was obtained prior to all procedures. This case series has been reported in line with the PROCESS Guideline [ 7 ]. This study was approved by the Ethics Committee of The First Hospital of Hebei Medical University. The research adheres to the revised version of the Declaration of Helsinki.
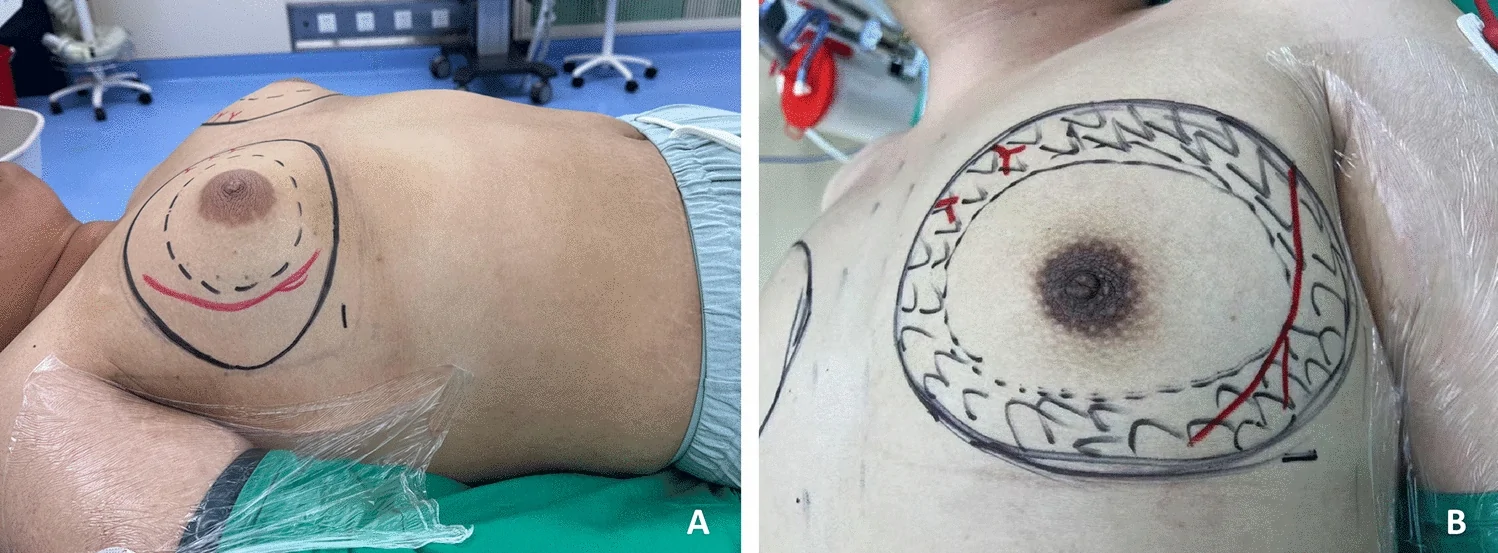
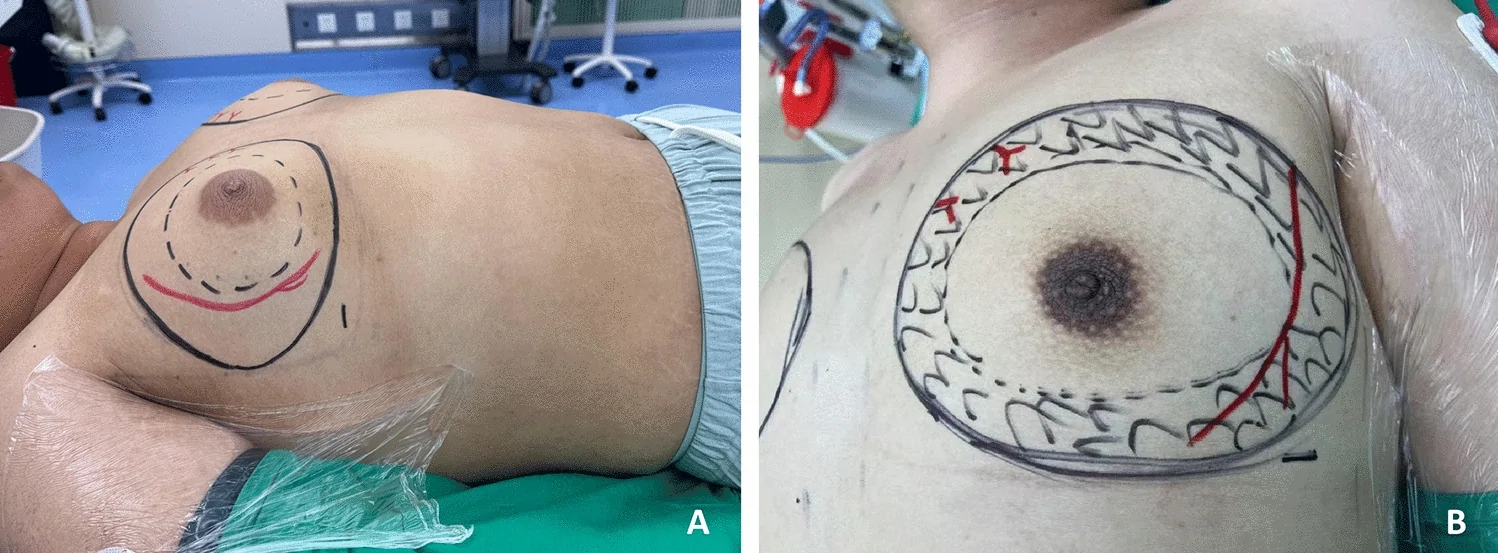
Step 1: Anesthesia and Positioning: General anesthesia with endotracheal intubation. Patients were placed supine with arms adducted and elbows flexed to expose the anterior axillary line (Fig. 1 A).
Step 2: Preoperative Marking: Mapping was systematically performed to delineate glandular excision area and liposuction boundaries as the “dual-ring” zones, with particular focus on mapping the anatomical courses of predominant vasculature including the lateral thoracic arteries/veins and internal thoracic arteries/veins (Fig. 1 B).
Step 3: Surgical Planes: A 1-cm incision was made at the intersection of the inframammary fold and anterior axillary line. Lipolytic solution was evenly injected into both the anterior mammary space and posterior mammary space. Twenty minutes later, liposuction was performed using standard liposuction apparatus. During liposuction of the anterior and posterior mammary space, a “dual-plane” architecture is established. The “dual-plane” of the liposuction apparatus is demonstrated in Fig. 2 . Dissection was carried out along the deep aspect of the superficial layer of the superficial fascia, within the avascular plane. The cannula was oriented with its lateral port facing the glandular surface to maintain optimal flap thickness (Fig. 3 A). Aspiration of the fat adherent to the glandular surface (anterior lamina fat) revealed the capsule of the corpus mammae. During aspiration of the posterior mammary space, position the side port facing the basal surface of the gland to preserve a uniform layer of fat on the posterior lamina fascia, while aspirating the deep adipose tissue adhering to the gland. This technique aims to retain the fat pad (posterior lamina fat) overlying the posterior lamina fascia. (Fig. 3 C). The liposuction extent was required to reach the periphery of the outer ring. Particular attention was paid to preserving adequate lateral flap thickness to prevent injury to the cutaneous branches of intercostal nerves.
Step 4: Glandular Resection: After liposuction, a 10-mm trocar was introduced through the 1-cm inframammary fold incision to establish the operative cavity with CO₂ insufflation at 8 mmHg. A 3-mm axillary stab incision accommodated a needle-tip electrosurgical device for complete transection of superficial fascial suspensory ligaments overlying the glandular surface along the superficial aspect of the “dual plane” framework. During superficial dissection, meticulous preservation of mammary margins was prioritized to prevent injury to major vascular trunks. During the dissection of the superficial lateral layer, the constant thoracolateral vein is frequently visualized (Fig. 4 A), while internal thoracic vein perforators are rarely encountered (Fig. 4 D). For severely hypertrophic breasts with redundant skin, it is essential to release the horizontal ligament along the inferior mammary fold to enhance skin compliance and prevent postoperative skin folds. Particular attention should be paid to preserving the transverse neural branches, especially the cutaneous branches of intercostal nerves along the lateral glandular margin (Fig. 4 B).
The ligaments along the inferior border of the gland were further resected following the deep aspect of the “dual-plane” layer. Complete excision of the glandular tissue within the inner ring was performed. During deep glandular dissection, meticulous preservation of the main trunks of the intercostal vessels perforating through the pectoralis major muscle and the lateral thoracic vessels was ensured. The schematic diagram of the surgical field is illustrated in Fig. 2 .
Step 5: Subareolar dissection: After thorough liposuction of the subareolar adipose tissue, the reflection of the superficial fascia at the areolar region was fully exposed (Fig. 3 B). The needle-tip electrosurgical device was utilized in low-power mode to transect the subareolar tissue, leaving a uniform thickness of 3 mm. Special attention was paid to preserving the subareolar plexus of veins (Fig. 4 C). Following complete glandular resection, the mammary gland was extracted through a 1 cm incision at the inframammary fold. Meticulous hemostasis was achieved, and the procedure concluded with standard wound closure.
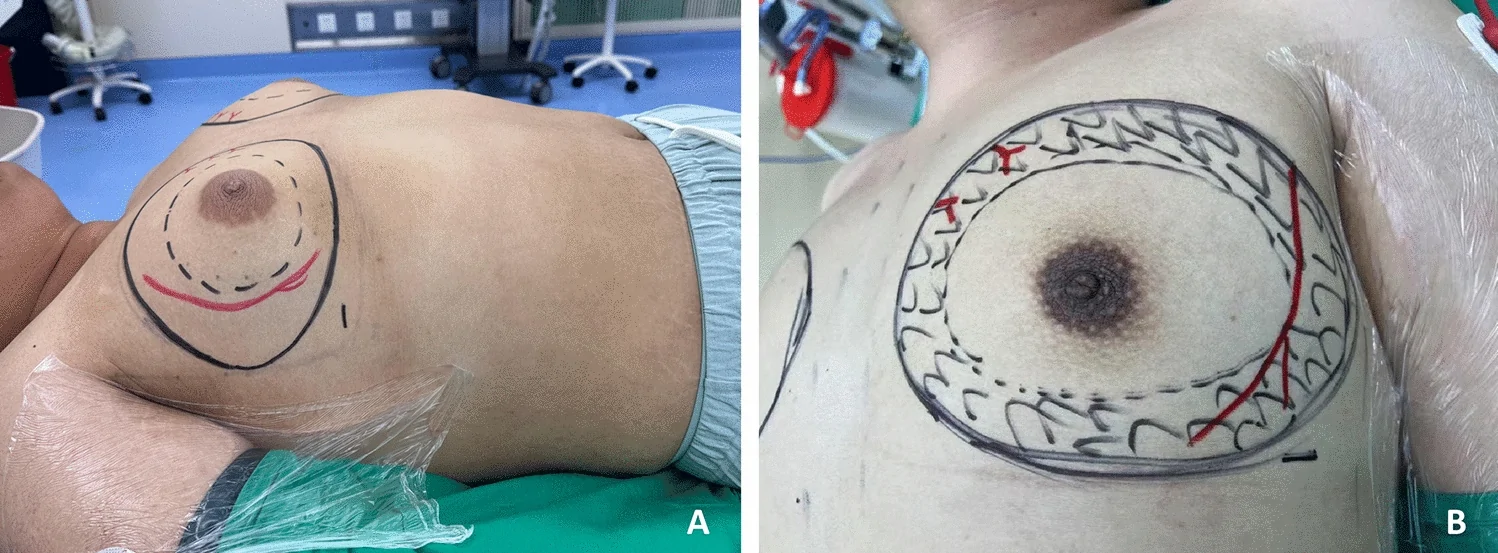
Fig. 1 A Patient positioning. B Preoperative marking of liposuction zones and critical neurovascular structures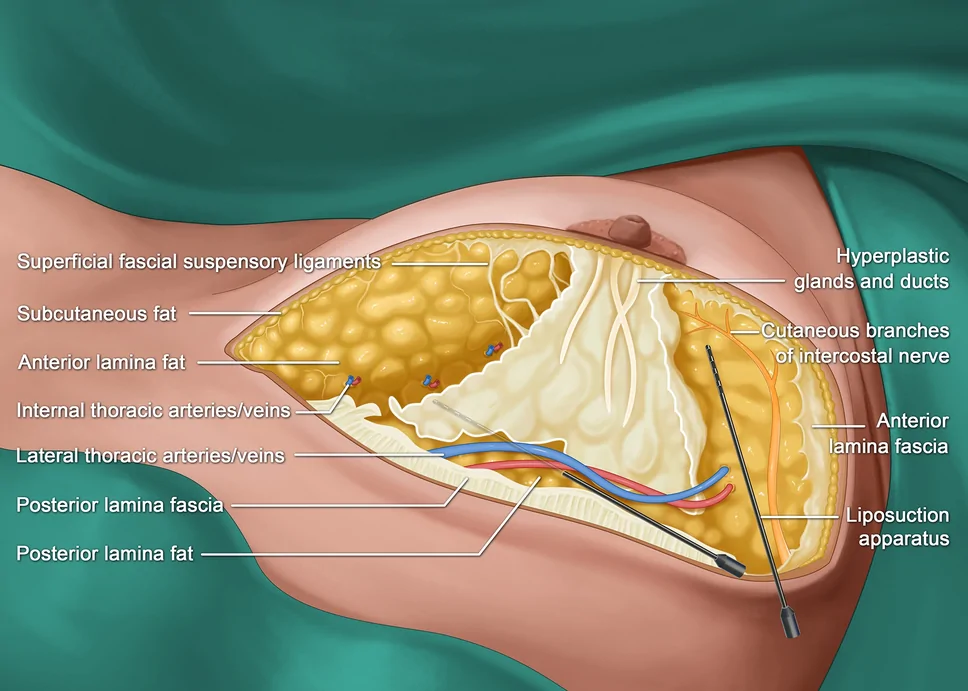
Fig. 2 Inferior view of the neurovascular structures and fascial system in the male breast, concurrently depicting the surgical field schematic for endoscopic glandulectomy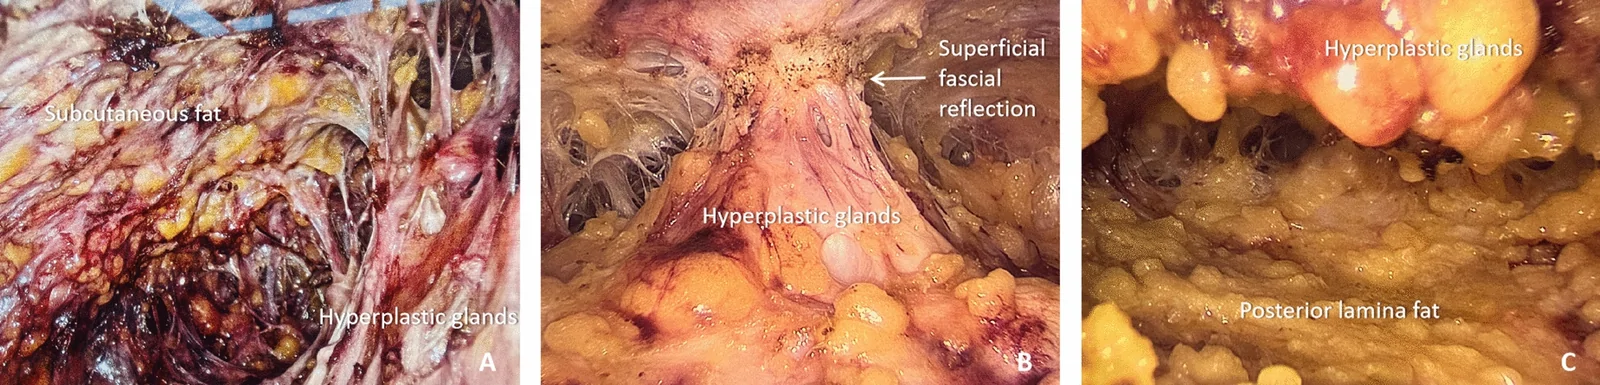
Fig. 3 A Intact preservation of subcutaneous fat overlying the superficial layer of the superficial fascia. B Subareolar suspension of hyperplastic ducts and glands, with arrows highlighting the fascial reflection of the superficial fascia. C Uniform fat retention on the deep layer of the superficial fascia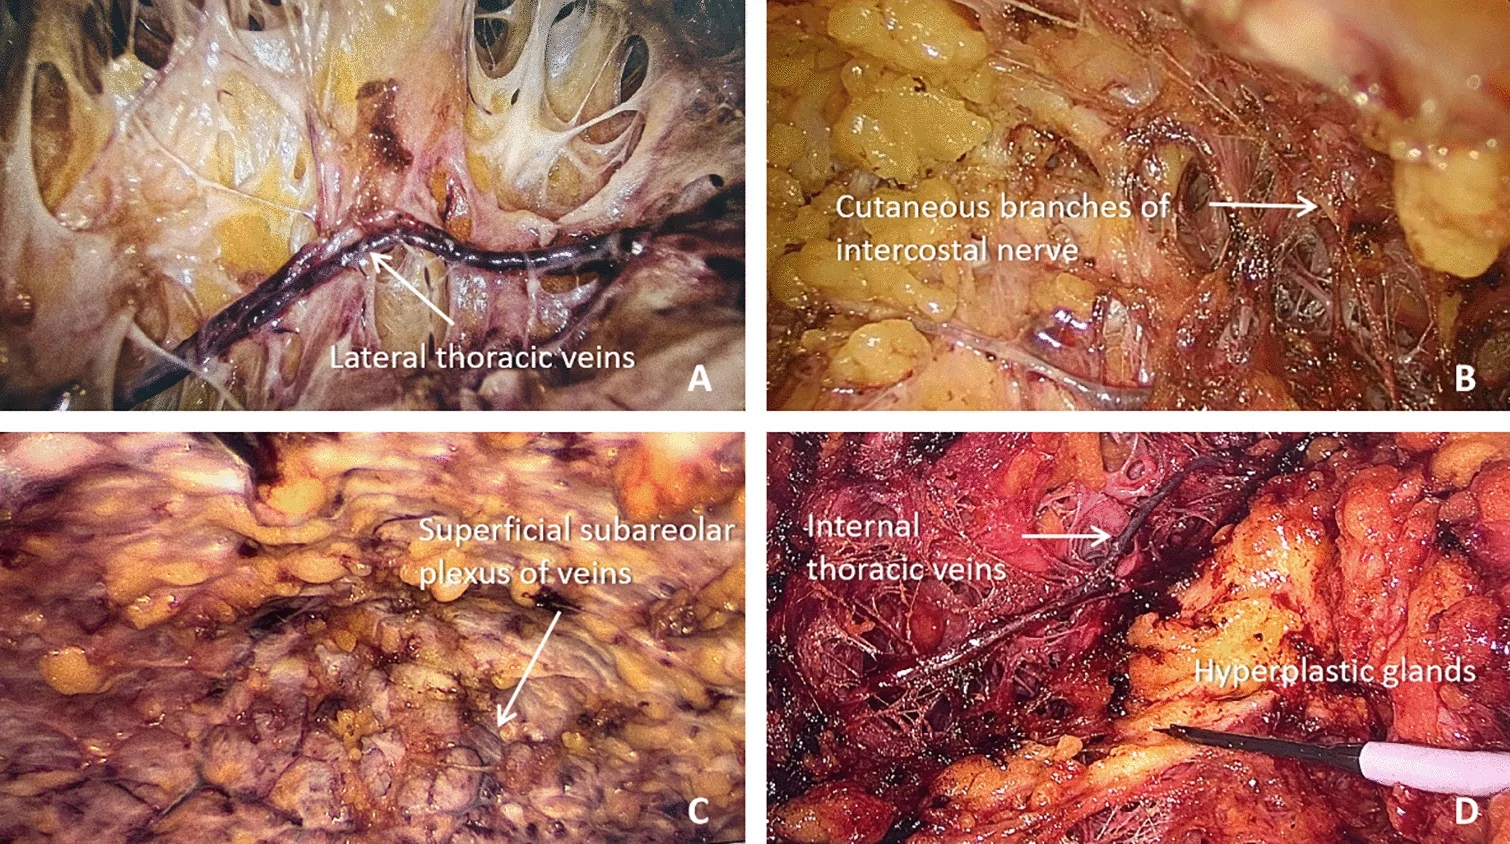
Fig. 4 A Preserved lateral thoracic vein. B Exposed cutaneous branches of intercostal nerves. C Superficial subareolar plexus of veins with branches converging laterally and medially into superior venous tributaries. D Perforating branches of the internal thoracic vein
Data were analyzed using SPSS 25.0. Continuous variables are expressed as mean ± SD and categorical variables are described using frequencies and percentages. Continuous variables were analyzed using the two-tailed Student’s t-test, and categorical variables were analyzed using the χ2 test or Fisher’s exact test, as appropriate. A P-value < 0.05 was considered statistically significant.
A total of 786 male patients were enrolled, including 13 unilateral cases and 773 bilateral cases. The mean age was 28.0 ± 9.6 years. The mean BMI was 26.8 ± 4.0. Simon classification was as follows: Grade I ( n = 114, 14.5%), Grade IIa ( n = 178, 22.6%), Grade IIb ( n = 416, 53.0%), and Grade III ( n = 65, 8.3%).
All procedures were successfully performed with no conversion to open surgery, no massive hemorrhage during surgery and no closed drains placed. The mean operative time was 117.8 ± 20.0 minutes, and the mean discharge time was 3.0 ± 0.7 days (Table 1 ). Postoperative complications included hematoma ( n = 4, 0.5%) and nipple-areolar ischemia ( n = 54, 6.9%). Of the 54 ischemic cases, 52 resolved spontaneously during follow-up, while two progressed to partial nipple-areolar necrosis (0.3%). Sensory evaluation scores for the NAC were 8.5 ± 2.0 (unilateral) and 8.0 ± 1.8 (bilateral), respectively (Table 2 ). The compression garment was worn for one month after the operation, and the mean follow-up time was 96.5 ± 5.0 days.
Table 1 Surgical characteristics of patient cohort (N = 786)
| Characteristic | n (%) |
|---|---|
| Laterality | |
| Bilateral | 773 (98.3%) |
| Unilateral | 13 (1.7%) |
| Mean age ± SD | 28.0 ± 9.6 |
| Simon | |
| Ia | 114 (14.5%) |
| IIa | 178 (22.6%) |
| IIb | 416 (52.9%) |
| III | 65 (8.3%) |
| Mean operative time ± SD | 117.8 ± 20.0 |
| Mean discharge time ± SD | 3.0 ± 0.7 |
Table 2 Surgical outcomes of patient cohort (N = 786)
| Characteristic | n (%) |
|---|---|
| NAC sensation | |
| Mean bilateral sensation | 8.0 ± 1.8 |
| Mean unilateral sensation | 8.5 ± 2.0 |
| Hematoma | 4 (0.5%) |
| NAC superficial necrosis | 2 (0.3%) |
| NAC ischemia | 54 (6.9%) |
| Infection | 0 |
| Open surgery | 0 |
Over the past few decades, various surgical approaches for gynecomastia have been explored, with substantial evidence comparing their advantages and limitations. We retrieved the literature on surgical methods for gynecomastia and their complications, as detailed in Table 3 . Among them, Xu et al. compared the periareolar incision excision and axillary approach endoscopic excision. The results showed that the rate of hematoma complications in endoscopic surgery was significantly lower than that in open excision [ 12 ]. The possible reason for the analysis might be that, under the same surgical scope as laparoscopic surgery, the incision of open surgery is larger, which leads to greater damage. Moreover, laparoscopy offers a magnified view several times that of open surgery, making the exposure of key structures clearer. Sim et al. evaluated differences among microdebrider excision and liposuction technique, liposuction only, open excision only and liposuction and open excision technique. The microdebrider excision and liposuction technique approach demonstrated advantages in reducing hematoma (4.5%) and scarring (1.9%), though its main disadvantage was glandular remnant (11.5%) [ 1 ]. In contrast, laparoscopic surgery can more thoroughly remove the gland. Yang et al. reported transaxillary single-incision endoscopic mastectomy combined with liposuction, observing unilateral subcutaneous seromas in 3 out of 89 breasts (3.4%) and unilateral hematomas in 5 cases (5.6%) [ 5 ]. The reported complication rate is also higher than that of the 1-cm single-port laparoscopic technique we have presented. Chen et al. compared the clinical efficacy of subcutaneous gland resection through an areolar incision, liposuction combined with single-hole endoscopic subcutaneous gland resection, and liposuction combined with three-hole endoscopic subcutaneous gland resection. Complication rates for hemorrhage and hematoma were 1 (5%), 1 (3.6%), and 0 (0%) across the three groups, respectively, while abnormal sensation of nipple and chest skin occurred in 4 (20%), 7 (25%), and 9 (31%) cases [ 2 ]. Overall, these previous studies largely corroborate our findings, demonstrating that endoscopic glandular resection exhibits advantages in preventing complications such as hematoma, nipple-areolar sensory loss, and scarring, and has refined the surgical procedures. The following discussion addresses critical operative steps based on these anatomical refinements.
Table 3 Comparison of different surgical methods
| Author | Year | Surgical Technique | Samplesize | Follow-up(months) | Complications(%) | Hospital stay |
|---|---|---|---|---|---|---|
| Hematoma | Hypoesthesia | NAC necrosis | Scar | Others | ||
| Sim et al. [ 1 ] | 2020 | Microdebrider excisionand liposuctiontechnique (MELT) | 156 | 12 | 4.5 | – |
| Liposuction only (LO) | 52 | 12 | 5.8 | – | ||
| Excision only (EO) | 48 | 12 | 8.3 | – | ||
| Liposuction and openexcision technique (LET) | 48 | 12 | 8.3 | – | ||
| Yao et al. [ 3 ] | 2019 | Vacuum-assistedmastectomy | 22 | 6.1 | 3.0 | 3.0 |
| Chen et al. [ 2 ] | 2024 | Areola incision + Liposuction | 20 | 2 | 5.0 | 20.0 |
| Liposuction + Single-port endoscopic glandectomy | 28 | 2 | 3.6 | 25.0 | – | – |
| Liposuction + Triple-port endoscopic glandectomy | 29 | 2 | – | 31.0 | – | – |
| Diyarbakirliogluet al. [ 8 ] | 2019 | Inferior pediclednon-vertical scarreduction technique | 58 | 4–12 | 3.4 | 1.7 |
| Qu et al. [ 9 ] | 2020 | Open surgery | 56 | 31.5 | 1.8 | 8.9 |
| Vacuum-assistedmastectomy usingMammotome | 13 | 31.5 | 7.7 | 7.7 | ||
| Vacuum-assistedmastectomy using Encor | 14 | 31.5 | 14.3 | 7.1 | ||
| Hasan [ 10 ] | 2020 | Subcutaneousmastectomy usingperiareolar incision withlateral and medialextension neededaccording to Webster | 100 | 6 | 31 | 10 |
| Proposed Modified Benelli Technique | 105 | 6 | 9 | 14 | ||
| Wang et al. [ 11 ] | 2019 | Traditional open surgery | 30 | 12 | – | – |
| Mammotome-assistedminimal invasiveresection | 30 | 12 | – | – | ||
| Xu et al. [ 12 ] | 2019 | Periareolar open excision | 27 | 9 | 7.4 | – |
| Endoscopic-assistedaxillary approach(endoscopic axillarysubcutaneousmastectomy) | 25 | 9 | 4.0 | – | ||
| Lee et al. [ 13 ] | 2019 | Subcutaneousmastectomy with liposuction + postoperative | 52 | 48 | 3.8 | – |
| Subcutaneousmastectomy withliposuction | 1621 | 47 | 2.5 | – | ||
| Lee et al. [ 14 ] | 2018 | Subcutaneousmastectomy withliposuction | 1156 | 30 | 2.6 | – |
| Ozalp et al. [ 15 ] | 2017 | Suction-assistedliposuction | 21 | 17.8 | 14.3 | 14.3 |
| Choi et al. [ 16 ] | 2017 | Subcutaneousmastectomy withpower-assistedliposuction | 71 | 18.6 | 2.8 | 5.6 |
| Khalil et al. [ 17 ] | 2016 | Liposuction pull-through technique | 52 | 6 | – | 19.2 |
| Kasielska-Trojan et al. [ 18 ] | 2017 | Adenectomy as perWebster’s technique | 50 | 6 | 6.0 | 8.0 |
| Kim et al. [ 19 ] | 2016 | Liposuction | 16 | 23.8 | – | – |
| Liposuction andsubcutaneousmastectomy | 48 | 33.1 | – | – | ||
| Ibrahiem [ 20 ] | 2016 | Combined ultrasound-assisted liposuction and subcutaneous mastectomy with preservation of the NAC on top of superior pedicle NAC flap through circumareolar incision | 27 | 48 | 3.7 | – |
| Schröder et al. [ 21 ] | 2015 | Liposuction | 53 | 6 | 3.8 | – |
| Liposuction through aninframammary-foldincision and bilateralexcision of the glandulartissue by a minimalperiareolar approach | 53 | 6 | 3.8 | – | ||
| Pilanci et al. [ 22 ] | 2014 | Gland excision + autologousfat injection | 52 | 16 | 1.9 | – |
| Fisher et al. [ 23 ] | 2014 | Subcutaneousmastectomy via a caudalsemi areolar incision | 11 | 34 | – | – |
| Subcutaneousmastectomy via a caudalsemi areolar incisionwith liposuction | 26 | 34 | – | – | ||
| Arvind et al. [ 24 ] | 2014 | Liposuction | 6 | 6 | 3.8 | – |
| Excision (semi-circularincision along theinferior margin of the | 37 | 6 | ||||
| Liposuction with excision(semi-circular incisionalong the inferior marginof the NAC | 10 | 6 | ||||
| Kasielska et al. [ 25 ] | 2013 | Subcutaneousmastectomy withcircumareolar approach | 94 | 6 | 3.2 | 2.1 |
| Subcutaneousmastectomy with skinexcision lateral wedge | 9 | 6 | 22.2 | 55.6 | ||
| Inverted T reductionmastopexy | 6 | 6 | 33.3 | 50.0 | ||
| Breast amputation withinframammary foldapproach | 4 | 6 | 25.0 | 25.0 | ||
| Blugermanet al. [ 26 ] | 2012 | Open RFAL with minimalaccess glandulartechnique,trans-mammillaryglandular resection | 12 | 12 | 16.7 | – |
| Closedradiofrequency-assistedliposuction RFAL | 47 | 12 | – | – | ||
| Li et al. [ 27 ] | 2012 | Mastectomy usingconcentric circumareolarapproach with nipplereposition | 41 | 7.5 | 9.8 | – |
| Subcutaneousmastectomy withpull-throughtechnique + ultrasound-assistedliposuction | ||||||
| Ultrasound-assistedliposuction | ||||||
| Cigna et al. [ 28 ] | 2010 | Power-assistedliposuction andmastectomy through asemi-circular subareolarincision | 37 | 12 | 2.7 | – |
| El-Sabbaghet al. [ 29 ] | 2016 | Liposuction (suction-assisted) and surgical excision through a periareolar incision | 14 | 24 | – | – |
| Cao et al. [ 30 ] | 2013 | Endoscopic subcutaneousmastectomy via threesmall skin incisions madeon the mid-axillary line | 58 | 36 | – | – |
| Taheri et al. [ 31 ] | 2016 | Periareolar incision withliposuction | 27 | 6 | – | 25.9 |
| Pfeiler et al. [ 32 ] | 2021 | Subcutaneousmastectomy | 60 | 69.6 | 5.0 | – |
| Subcutaneous mastectomy + ultrasound-assistedliposuction | 45 | 89.2 | 4.4 | – | ||
| Akhter et al. [ 33 ] | 2019 | Liposuction combinedwith open disc excision,via a periareolar incisionin the lower half of thenipple-areolar complex | 30 | 6 | 6.7 | – |
| Liposuction coupled withdisc excision viasuction-assistedarthroscopic shaver | 30 | 6 | 10.0 | – |
We observed that a fascial system analogous to the thyroid capsule can also be divided into two layers in the male breast: the superficial fascia surrounding the mammary gland and adipose tissue externally and the capsule of the corpus mammae closely adhering to the glandular parenchyma. The superficial fascia comprises superficial and deep layers, analogous to Camper’s fascia and Scarpa’s fascia of the abdominal wall [ 34 , 35 ]. The mammary gland suspended between the two layers of the superficial fascia, so the two layers of superficial fascia is also called the anterior lamina fascia and posterior lamina fascia. The anterior lamina fascia divides subcutaneous fat into a surface sheet that adheres to the dermis and a deep sheet with a trabecular pattern directed toward the glandular parenchyma [ 35 , 36 ]. This demonstrates the superficial aspect of the “dual-plane” framework during liposuction.
The posterior lamina fascia lies behind the gland. Between the posterior lamina fascia and the pectoral fascia, a loosely organized space termed the retromammary space allows natural breast mobility on the chest wall [ 36 ]. During surgery, liposuction and tissue dissection along the deep aspect of the “dual-plane” framework preserves a uniform layer of fat over the deep layer of Scarpa’s fascia, which we consider optimal for achieving natural aesthetic outcomes in clinical practice. Fig. 5 illustrates postoperative recovery at three month and 1 year in two patients with preoperative bilateral Simon Grade III hypertrophy and right-sided IIb hypertrophy, respectively. Postoperative breast skin contracted effectively, resulting in a natural and aesthetically pleasing contour.
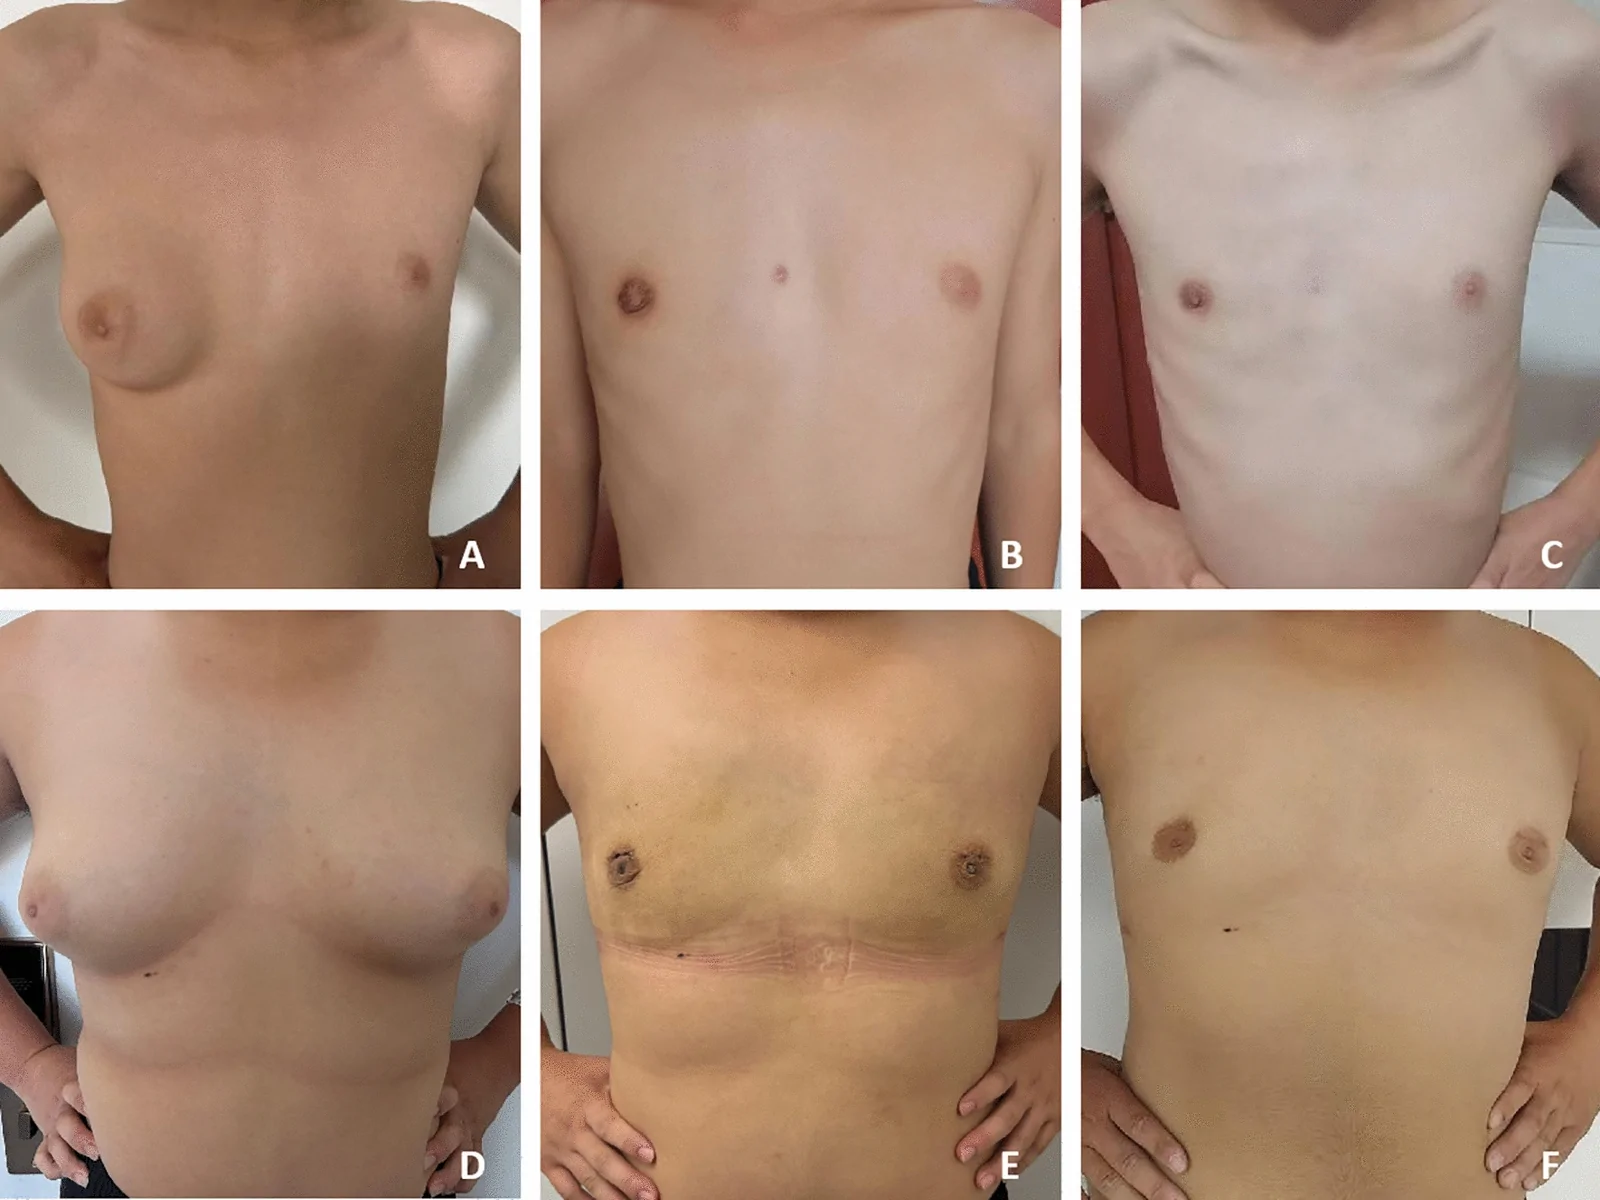
Fig. 5 A Preoperative Simon grade III gynecomastia. B Natural breast contour demonstrated at 3-month postoperative follow-up. C Natural breast contour demonstrated at 1-year postoperative follow-up. D Preoperative right-sided Simon grade IIb gynecomastia. E Bilateral symmetry achieved at 3-month postoperative follow-up. F Bilateral symmetry achieved at 1-year postoperative follow-up
A male-focused study evaluated 142 thoracic computed tomographic angiography and 284 breast vasculatures. The study revealed that 69.0% of breasts were supplied by a single artery, 6.0% were fed by vascular anastomosis formed by dual arteries. Notably, 25.0% of breasts lacked identifiable dominant arterial patterns. The lateral thoracic artery (LTA) was the most frequent single dominant artery of origin (41.9%) , followed by perforating branches of the internal thoracic artery (ITA;22.2%); 4.2% of male breasts were supplied mostly by the anterior intercostal artery (AICA). The most common anastomoses were formed by the ITA and LTA [ 37 ]. Preoperative marking of key vasculature and meticulous intraoperative preservation of critical arteries/veins were implemented to minimize perfusion compromise.
In female NAC vascular studies, ITA perforators predominated as the primary supply (81.8%), followed by LTA contributions (23.5%) and AIA perforators (15.9%), with minimal involvement from the superior thoracic artery (0.8%) [ 38 ]. Two additional studies corroborated ITA as the most prevalent dominant arterial source in female NACs, succeeded by LTA [ 39 , 40 ]. The areas where these vessels emerge through the thoracic wall (hypervascular zones/fixed skin areas) are constant and include the parasternal border, submammary fold, and the lateral thoracic wall along the lower lateral border of the pectoralis minor muscle [ 40 ]. Postoperative hematomas occurred in only 0.5% of cases (exclusively unilateral), underscoring the importance of avoiding mammary margin dissection during liposuction and glandular resection to preserve vascular integrity. This protocol has demonstrated significant reduction in postoperative hematoma rates compared to prior methodologies [ 1 – 3 ].
The venous drainage of the breast is composed of an extensive vascular network. The nipple-areolar complex (NAC) is drained by the superficial subareolar plexus of veins, which converges into the medial and lateral mammary veins. The lateral, superolateral, and inferolateral veins ultimately drain into the subclavian vein, while two medial dominant veins drain the breast tissue to the internal mammary veins. The medial vessels coursing superficially, whereas laterally the veins have a deeper course [ 41 ]. However, our analysis of 52 cases with postoperative NAC ischemia revealed intraoperative absence of the superficial subareolar plexus of veins in 36 patients (67.9%), potentially attributable to iatrogenic disruption during surgery or congenital absence of this vascular network. These findings suggest that deficiencies in the subareolar venous plexus may contribute to ischemic complications. The anatomical consistency of this venous plexus in male breasts warrants further investigation. Additionally, excessive intraoperative coagulation of venous channels might predispose to postoperative venous congestion. All affected cases demonstrated restored perfusion by the 3-month follow-up interval. The subcutaneous arteriovenous network plays a critical role in maintaining cutaneous and NAC perfusion. Preservation of this vascular network during mastectomy is imperative. Current understanding of venous anatomy indicates that injury to the superficial venous system may precipitate NAC necrosis [ 42 ].
Two cases in the cohort developed NAC necrosis with tissue sloughing at 1-month follow-up. Intraoperatively, neither significant arterial branch hemorrhage nor a discernible subareolar venous plexus was identified in this patient. The necrosis may be attributed to iatrogenic disruption of the subareolar venous plexus during liposuction (resulting in intraoperative venous stasis and postoperative congestion), compounded by ischemic compression from an excessively tight postoperative compression garment. NAC perfusion in nipple-sparing mastectomy (NSM) primarily relies on superficial vascular networks following complete glandular resection, with dominant contributions from perforating branches of the internal thoracic artery (ITA) and external thoracic artery. However, postoperative NAC necrosis cannot be entirely prevented. Critical vascular networks reside 3–5 mm beneath the areolar dermis, necessitating meticulous intraoperative preservation. Yang et al. reported no incidence of NAC necrosis in their study of 110 NSM patients when the preserved subareolar flap thickness was maintained at 3–5 mm [ 43 ]. Komiya et al. demonstrated that the anterior lamina fascia extends subareolarly, exhibiting significant thickening and reflection at an average distance of 1 cm from the nipple. Microanatomical analysis revealed that this fascial layer comprises collagenous elastic fibers interspersed with smooth muscle cells, forming a thickened reflection that encircles the lactiferous ducts, neurovascular bundles, and associated stromal structures [ 44 ]. Incision through the superficial fascial reflection at 3 mm subareolar, avoiding excessive residual tissue behind NAC to prevent postoperative “checkerboard-like” glandular tissue retention in the areola. Excessively thin residual tissue may damage the dermal blood supply of the NAC or cause postoperative nipple inversion.
Cutaneous innervation of the female breast derives from anterior and lateral cutaneous branches of the second to sixth intercostal nerves (ICNs) [ 45 ]. NAC sensation is predominantly mediated by the lateral cutaneous branch of the fourth ICN, supplemented by anterior branches of the third to fifth ICNs and lateral branches of the third and fifth ICNs [ 46 ]. Substantial discrepancies exist across studies regarding the topographic course of neural pathways through breast parenchyma [ 45 , 47 – 49 ]. It is generally recognized in that the fourth ICN’s lateral branch bifurcating into superficial and deep divisions. The deep division courses within the pectoral fascia along the inferior breast border for 3–4 cm before executing a U-shaped retrograde trajectory through inferolateral breast tissue toward the NAC, corresponding to the 4 o’clock (left) and 8 o’clock (right) positions on the breast clockface [ 34 , 50 ]. Avoiding the inferolateral quadrant during liposuction and preserving adequate lateral flap thickness are critical for maintaining neural integrity within adipose tissue. Suspicious neural structures in lateral breast regions warrant meticulous preservation to optimize NAC sensory outcomes. Retaining lateral breast flaps additionally ensures natural axillary-anterior chest fat continuity, enhancing aesthetic contour. According to our follow-up results, with careful attention to nerve preservation, none of the patients experienced significant sensory deficits. Notably, some patients reported numbness during hospitalization, which showed improvement at follow-up assessments after more than 3 months of recovery. This indicates that nerve recovery requires a certain period of time, consistent with conclusions from previous studies [ 51 ].
This study propose the refined anatomical concept in gynecomastia surgery at a relatively early stage, providing procedural steps and technical considerations. Preliminary results suggest benefits in postoperative sensory preservation, recovery outcomes, and patient satisfaction, which warrant further validation in expanded cohorts. This study has several limitations. First, its single-center design may compromise the generalizability of the conclusions. Furthermore, as a preliminary report emphasizing surgical anatomical principles, we did not analyze factors affecting NAC sensation; current assessments rely solely on subjective patient-reported evaluations without objective measurements, a gap to be addressed through a dedicated prospective study in forthcoming research. Additionally, long-term follow-up data remain unavailable at this stage, with plans for their inclusion in subsequent investigations.
Endoscopic male breast surgery should not only ensure resection of the gland but also aim to reduce postoperative complications and enhance patient satisfaction. Mastering the refined anatomy of the breast fascial layers to establish the "dual-plane" architecture prevents neurovascular injury, thereby enhancing clinical outcomes for patients with gynecomastia.
Below is the link to the electronic supplementary material.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
单中心、单臂前瞻性病例系列(证据等级 III),纳入 2024 年河北医科大学第一医院 786 例男性乳腺发育内镜腺体切除术患者(773 例双侧、13 例单侧),平均随访 96.5
单中心、单臂前瞻性研究(PROCESS 报告规范),纳入2024年786例男性乳腺发育患者行内镜腺体切除术,探讨基于精细筋膜解剖的微创手术要点。
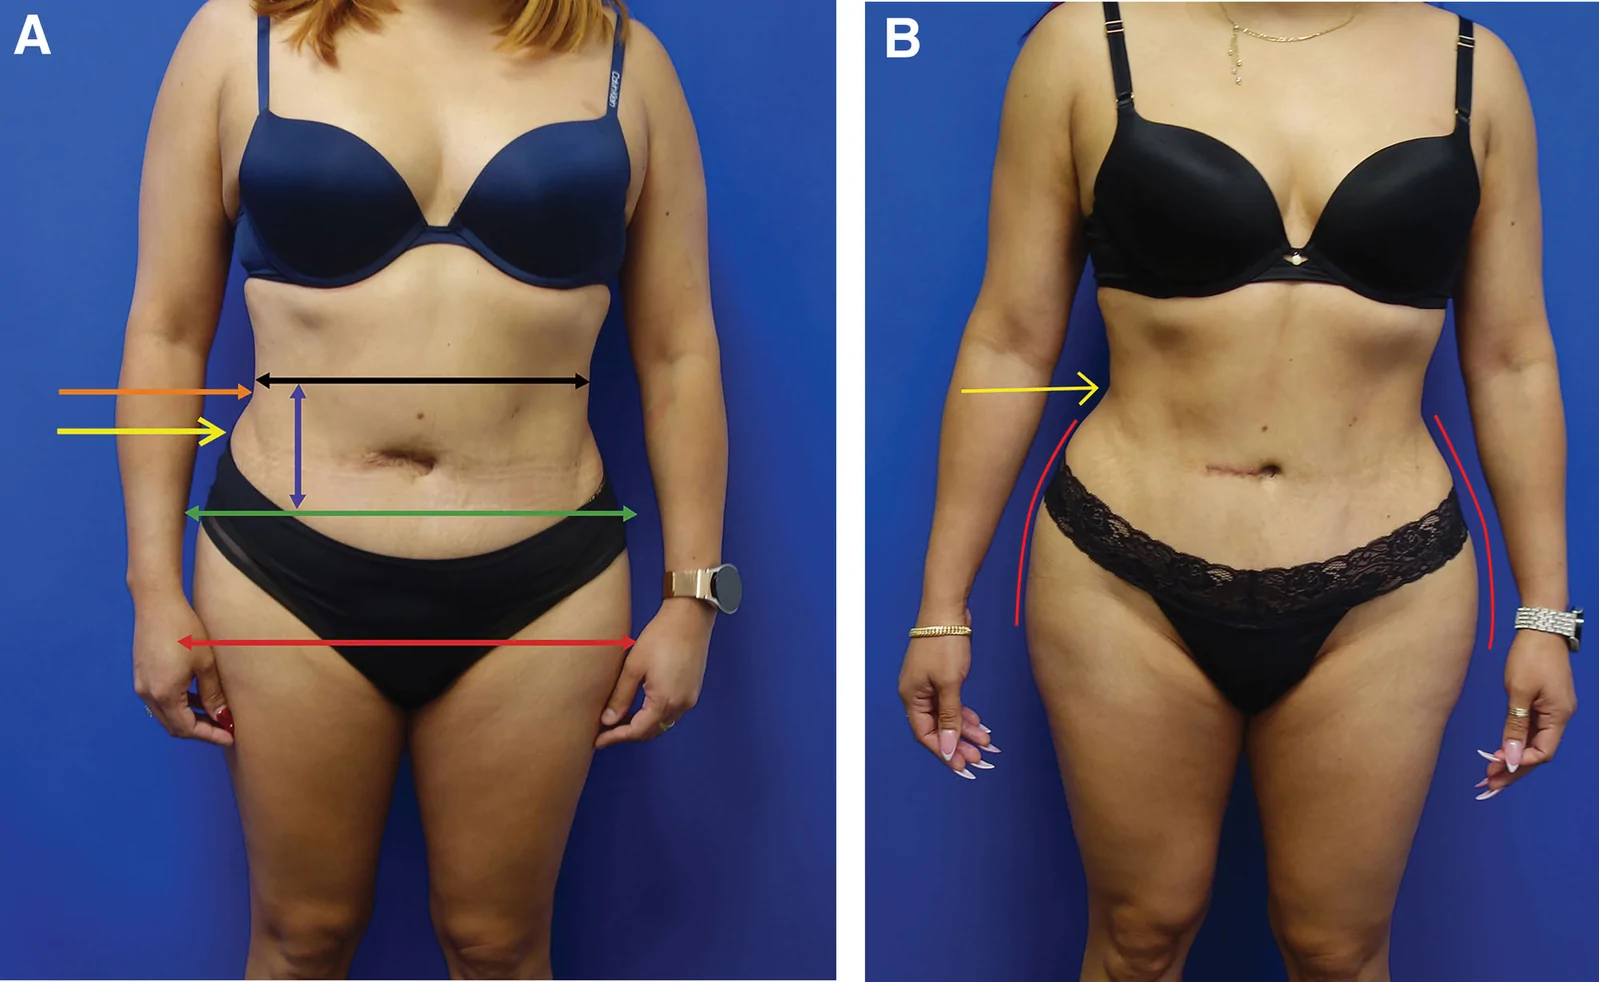
研究设计:PRS Global Open 回顾性研究,2016-11 至 2025-01 共 1999 例连续手术,旨在界定并塑形『腰腹过渡美学单元(waist transitio