鼻背结构性轮廓技术:骨软骨整合的四阶段渐进塑形方法
2026年10月19日21 min read
Plastic and Reconstructive Surgery Global Open

结论与实践要点
针对鼻整形中较棘手的骨软骨交界区鼻背轮廓不规则问题,本文提出结构轮廓技术,将骨性与软骨性操作整合为循序渐进的四阶段流程,适用于鼻背基本对齐、仅需精细雕琢轮廓的病例(含天然对齐或既往采用保留鼻背技术者,排除Goksel的ballerina手法)。其机制在于先建立稳定骨性穹顶,再稳定骨软骨过渡区,最后以软骨背环扎界定上外侧软骨「休息角」,在维持内鼻阀功能的前提下获得平行、清晰的鼻背美学线。
属4例的初步描述性技术笔记,无对照、无统计检验、无客观量化结局(仅术者主观影像观察显示背线由不连续渐变为平行清晰)。文中所有效果均来自小样本主观照片对比,缺乏鼻阀功能客观检查、并发症统计与学习曲线量化。任何机构开展前宜以小样本、标准化摄影与鼻功能评估逐步验证,不宜将文中美学效果直接外推为普适结局;对需要显著降低鼻背高度或重塑穹顶者,本技术非针对性方案。
Dorsal definition represents a persistent challenge in rhinoplasty, especially at the osteocartilaginous junction. We present the structural contour technique, a progressive 4-phase surgical approach designed to achieve a more defined and stable nasal dorsum through combined bony and cartilaginous maneuvers. The technique includes bony framework modification through targeted ostectomy and remodeling, osteochondral stabilization at the keystone area using cerclage sutures, controlled inferior reinsertion of the upper lateral cartilages, and final dorsal contour refinement with a continuous absorbable suture to achieve a cylindrical configuration while preserving nasal valve function. In a preliminary descriptive experience involving 4 patients, this technical approach allowed tailored dorsal contour refinement according to individual anatomical and aesthetic requirements. The structural contour technique provides a systematic and reproducible framework for dorsal refinement, integrating bone and cartilage in a controlled and harmonious manner.
Question: How can progressive dorsal refinement be achieved in rhinoplasty while maintaining a stable osteocartilaginous framework and preserving nasal valve function?
Findings: The structural contour technique introduces a 4-phase approach that sequentially integrates osseous and cartilaginous maneuvers, including bony remodeling, osteochondral alignment with cerclage fixation, inferior reinsertion of the upper lateral cartilages, and final dorsal cerclage refinement. This stepwise method allows progressive dorsal definition tailored to each patient’s aesthetic goals.
Meaning: A systematic and reproducible strategy for achieving stable, functional, and harmoniously contoured nasal dorsal lines in rhinoplasty.
The nasal dorsum is a pivotal determinant of facial aesthetics. 1 The osteocartilaginous junction represents a critical transition zone where even subtle irregularities become visible under tangential light. 2 Although dorsal preservation techniques have gained popularity over the last decade, they may not consistently ensure smooth integration between bone and cartilage, especially in patients with preexisting deformities or previously modified dorsums. 3 , 4
To address this limitation, we propose the structural contour technique, a systematic, 4-phase approach that integrates osseous and cartilaginous maneuvers to achieve well-defined, stable, and functional dorsal lines.
The surgical steps are presented for didactic and illustrative purposes, focusing on the technical sequence of the procedure and its anatomical rationale, rather than perioperative management or postoperative care. A detailed operative demonstration of the 4-phase structural contour technique is provided in the Video. ( See Video [online] , which shows the 4-phase approach, including bony framework modification, osteochondral stabilization at the keystone area, cartilaginous refinement, and final dorsal contour definition.)
The 4-phase dorsal approach was applied to adapt surgical planning to each patient’s anatomical characteristics and aesthetic requirements. In cases of a preserved dorsum, either naturally aligned without requiring modification of height or projection, 5 or previously managed using a dorsal preservation technique (excluding the “ballerina maneuver” described by Goksel), 6 the nasal dorsum was systematically treated in 4 sequential phases.
Phase 1 focuses on controlled preparation and equalization of the bony framework to achieve dorsal symmetry and initiate progressive narrowing. The objective of this phase is to establish a stable and balanced osseous foundation that facilitates subsequent osteochondral and cartilaginous refinement.
Preoperative views illustrating baseline dorsal morphology before bony framework modification are shown in Figure 1 . A schematic overview of the planned bony framework modifications is provided in Figure 2 . ( See figure, Supplemental Digital Content 1 , which shows phase 1: structural contouring. Preoperative left lateral view, https://links.lww.com/PRSGO/F45.)

Fig. 1. Phase 1: Structural contouring. Preoperative frontal view.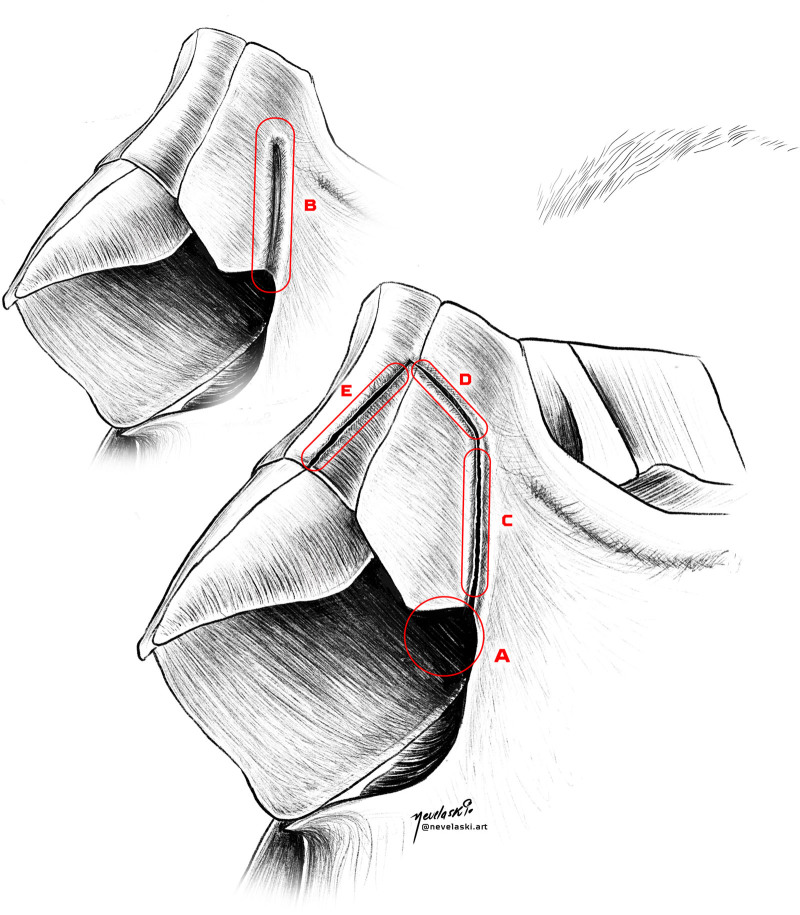
Fig. 2. Phase 1: bony framework. Stepwise illustration of osteotomies and bone modifications: (A) Webster triangle ostectomy; (B) formation of nasofacial groove; (C) low-to-low lateral osteotomy with piezotome; (D) greenstick transverse osteotomy; and (E) paramedian osteotomy for dorsal equalization.The sequence begins with targeted ostectomy of the Webster triangle at the maxillopyriform angle to reduce excessive lateral bony width (Fig. 3 ), followed by creation of the nasofacial groove through controlled bony drilling to define the lateral dorsal contour (Fig. 4 ). A complete low-to-low lateral osteotomy is then performed using a piezotome to allow precise and atraumatic mobilization of the nasal bones (Fig. 5 ). This is followed by a greenstick transverse osteotomy to facilitate controlled medialization of the bony vault (Fig. 6 ). When indicated to correct residual asymmetry or unequal dorsal height, a complete paramedian osteotomy is performed to achieve dorsal equalization (Fig. 7 ).
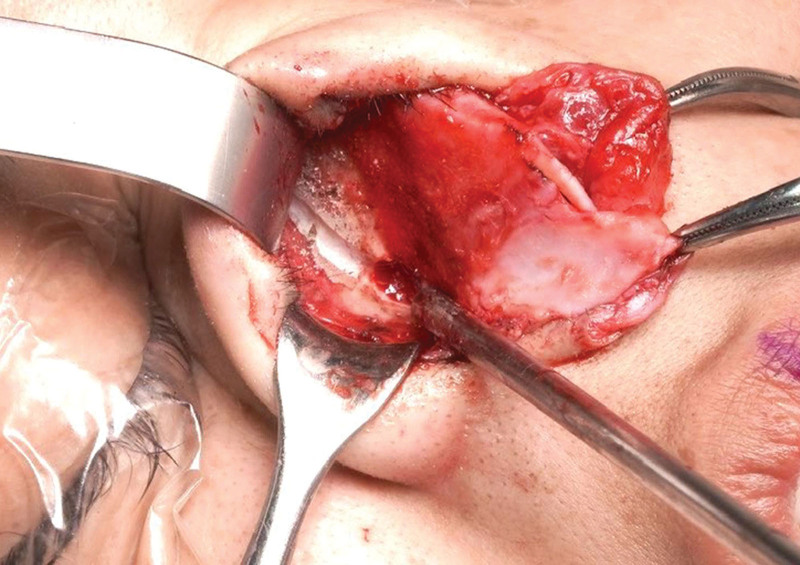
Fig. 3. Webster triangle ostectomy. Intraoperative exposure of the maxillopyriform angle following targeted bony resection, representing the first step of phase 1 in structural contouring.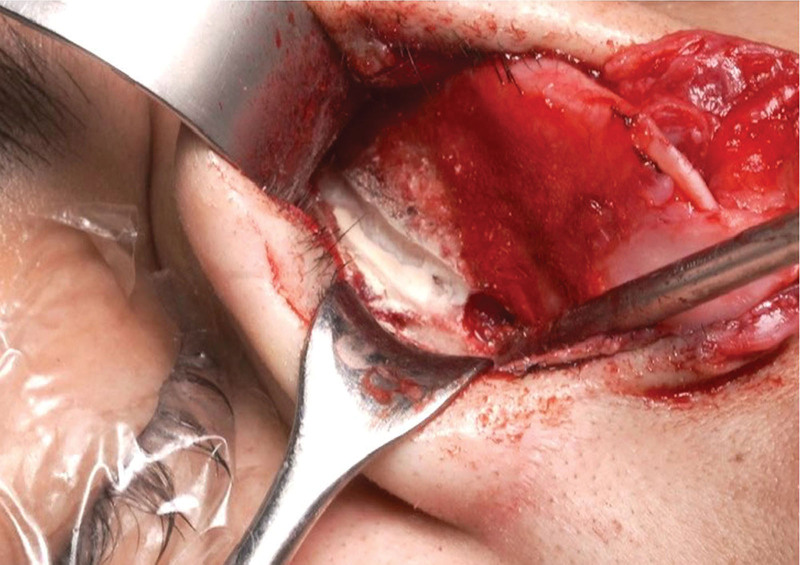
Fig. 4. Nasofacial groove drilling. Intraoperative view showing the creation of a bony channel along the nasofacial groove, corresponding to the second step of phase 1 in structural contouring.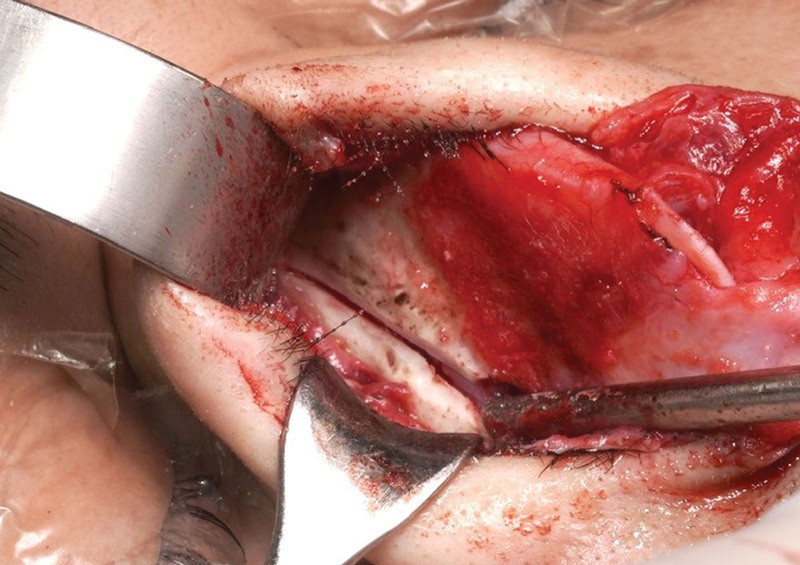
Fig. 5. Complete lateral osteotomy with piezotome. Intraoperative view of the low-to-low lateral osteotomy, representing the third step of phase 1 in structural contouring.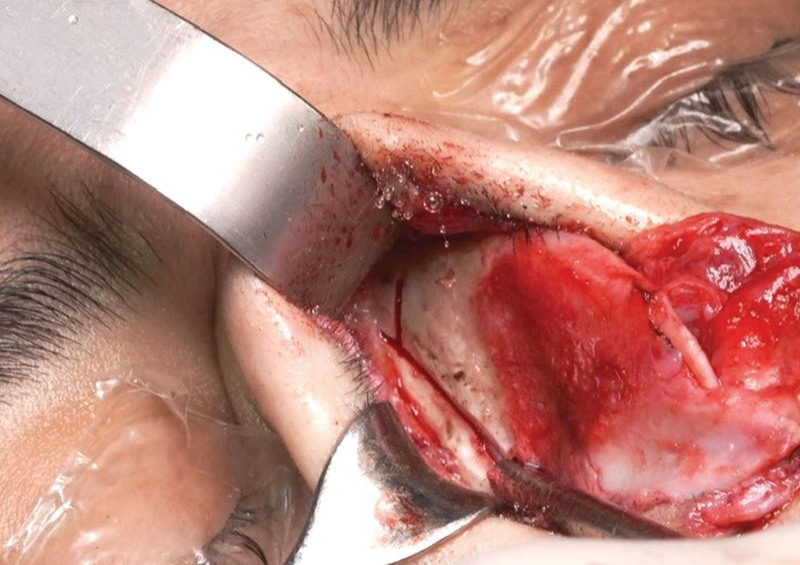
Fig. 6. Greenstick transverse osteotomy. Intraoperative image of the transverse osteotomy, representing the fourth step of phase 1 in structural contouring.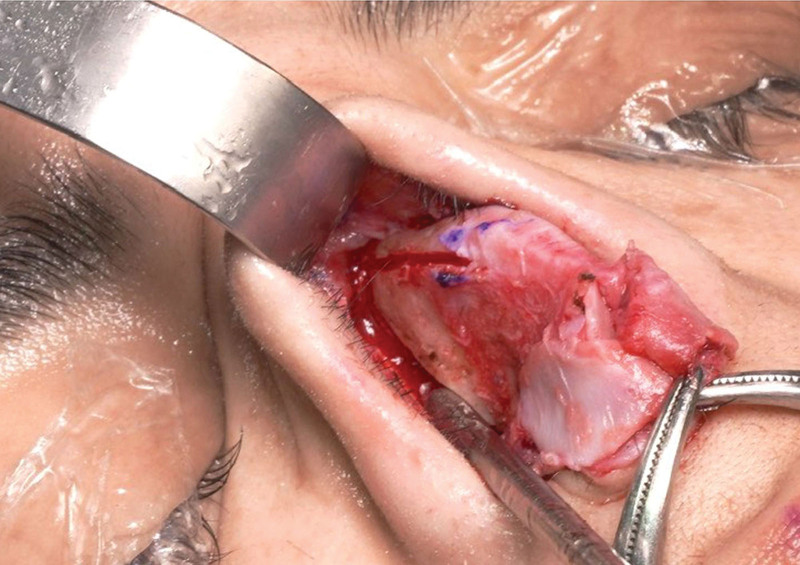
Fig. 7. Complete paramedian osteotomy. Intraoperative exposure of the paramedian osteotomy, representing the fifth step of phase 1 in structural contouring.Postoperative views after completion of phase 1 are presented in Figure 8 . ( See figure, Supplemental Digital Content 2 , which shows phase 1: structural contouring. Postoperative left lateral view, https://links.lww.com/PRSGO/F46.)

Fig. 8. Phase 1: structural contouring. Postoperative frontal view following completion of bony framework modification.
Phase 2 addresses stabilization of the osteocartilaginous junction at the keystone area, a critical transition zone for dorsal continuity and structural support. The objective of this phase is to restore controlled alignment between the nasal bones and the upper lateral cartilages, ensuring a smooth and stable dorsal contour.
Preoperative views before keystone stabilization are shown in Figure 9 . A schematic representation of the planned osteochondral stabilization strategy is provided in Figure 10 . ( See figure, Supplemental Digital Content 3 , which shows phase 2; structural contouring. Preoperative left lateral view, https://links.lww.com/PRSGO/F47.)

Fig. 9. Phase 2: structural contouring. Preoperative frontal view.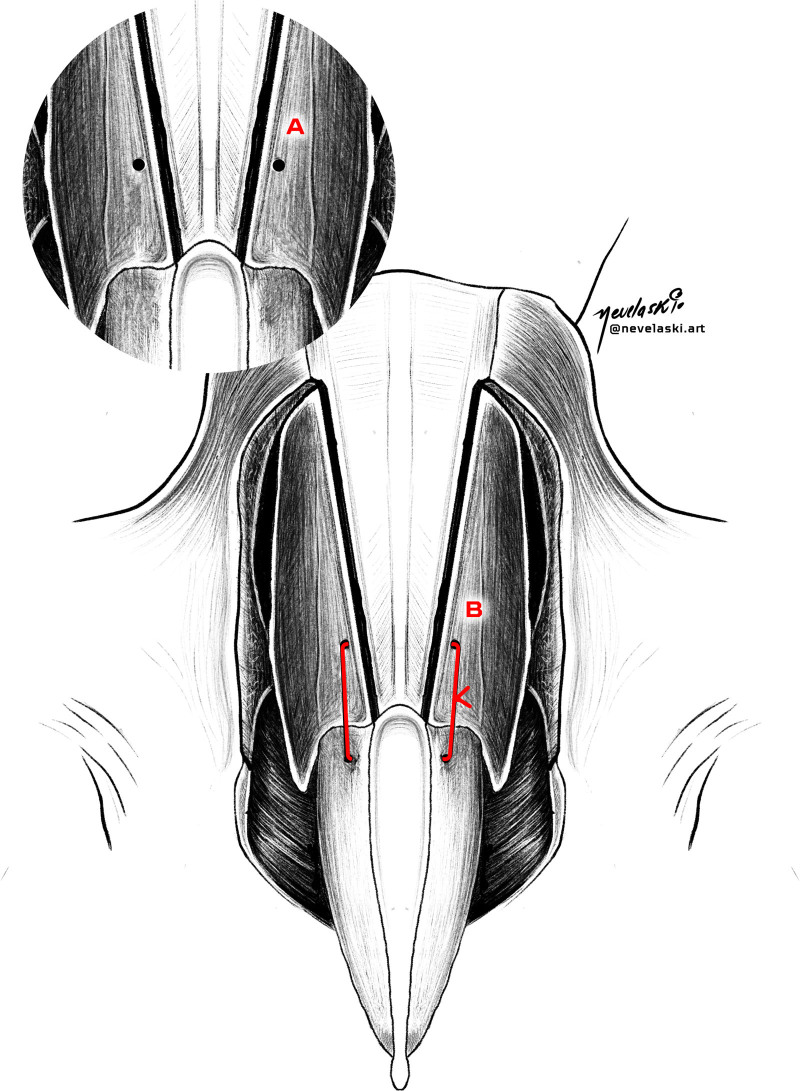
Fig. 10. Phase 2: osteochondral stabilization (keystone area). Illustrative representation of the main steps: (A) Drill hole in the nasal bone and (B) fixation of the nasal bone to the upper lateral cartilages.Intraoperatively, a drill hole is created in the nasal bone using an 18-gauge needle to facilitate precise passage of the fixation suture (Fig. 11 ). The nasal bones are then fixated to the upper lateral cartilages using a 4-0 Monocryl suture, achieving controlled osteochondral alignment and continuity across the keystone area.
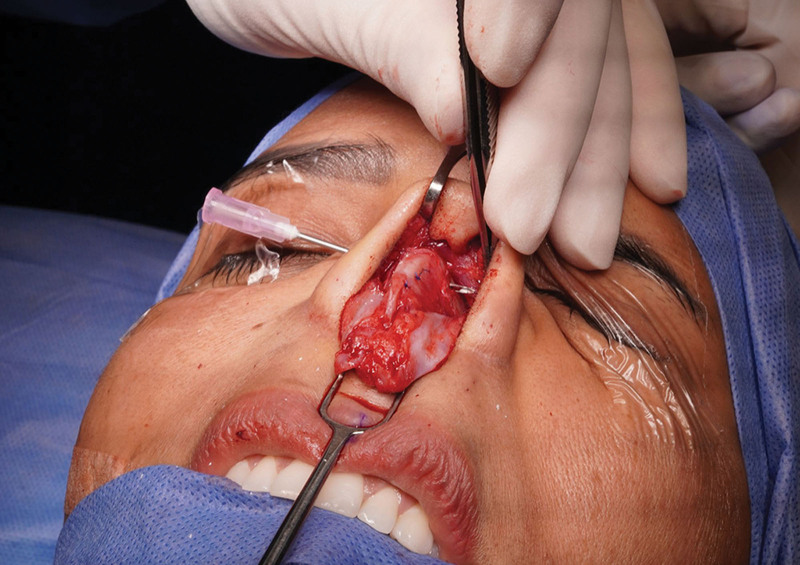
Fig. 11. Osteochondral stabilization (keystone area). Intraoperative image showing creation of a drill hole in the nasal bone and fixation of the nasal bone to the upper lateral cartilage.Postoperative views demonstrating dorsal contour following completion of phase 2 are presented in Figure 12 . ( See figure, Supplemental Digital Content 4 , which shows phase 2: structural contouring. Postoperative left lateral view, https://links.lww.com/PRSGO/F48.)

Fig. 12. Phase 2: structural contouring. Postoperative frontal view.
Phase 3 focuses on controlled cartilaginous refinement at the W ASA segment to optimize dorsal alignment while preserving internal nasal valve function. The objective of this phase is to modulate the resting position of the upper lateral cartilages, contributing to dorsal stability and smooth contour transition.
Preoperative views before cartilaginous refinement are shown in Figure 13 . A schematic illustration of the planned cartilaginous modifications at the W ASA segment is provided in Figure 14 . ( See figure, Supplemental Digital Content 5 , which shows phase 3: structural contouring. Preoperative left lateral view, https://links.lww.com/PRSGO/F49.)

Fig. 13. Phase 3: structural contouring. Preoperative frontal view.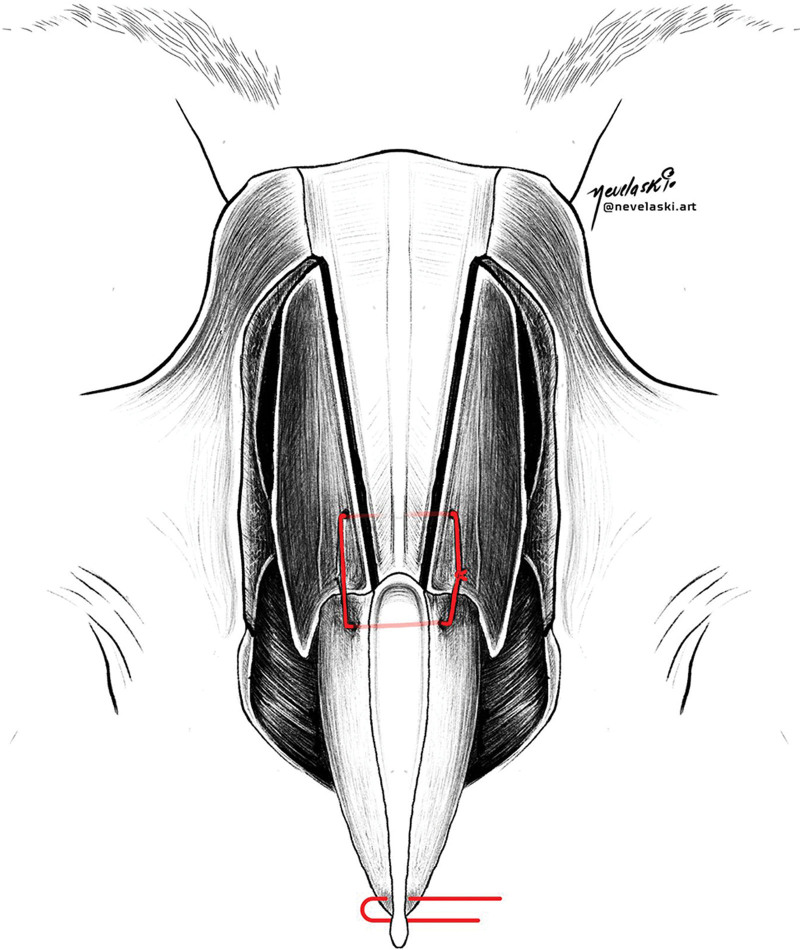
Fig. 14. Phase 3: cartilaginous refinement (W ASA segment). Illustrative image of key steps: 5 mm release at septum–upper lateral cartilage junction; 2 mm inferior reinsertion of upper lateral cartilages; preservation of the internal nasal valve.A controlled release of approximately 5 mm is performed at the septum–upper lateral cartilage junction (W point) to allow mobilization of the cartilaginous framework. Inferior reinsertion of the upper lateral cartilages onto the septum is then performed with a 2-mm advancement using 5-0 Monocryl sutures (Fig. 15 ). This maneuver permits controlled adjustment of the resting angle of the upper lateral cartilages, contributing to improved dorsal alignment and enhanced contour stability while maintaining internal nasal valve patency. Preservation of the internal nasal valve is confirmed during the procedure. ( See figure, Supplemental Digital Content 6 , which shows the maneuver to confirm internal nasal valve angulation ±30 degrees, https://links.lww.com/PRSGO/F50.)
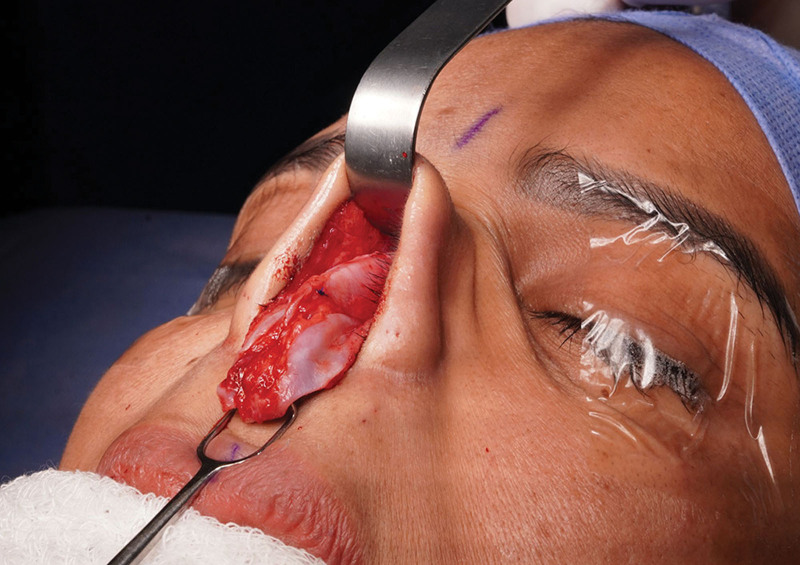
Fig. 15. Cartilaginous refinement (W ASA segment). Intraoperative image demonstrating release at the septum–upper lateral junction (W point), inferior reinsertion of the upper lateral cartilages, and formation of the W ASA segment.Postoperative views demonstrating improved dorsal support and preservation of internal nasal valve function are presented in Figure 16 . ( See figure, Supplemental Digital Content 7 , which shows phase 3: structural contouring. Postoperative left lateral view, https://links.lww.com/PRSGO/F51.)

Fig. 16. Phase 3: structural contouring. Postoperative frontal view.
The final phase consists of cartilaginous dorsum cerclage to refine and stabilize the dorsal aesthetic lines. The objective of this phase is to achieve parallel, well-defined, and durable dorsal contours while maintaining nasal valve patency.
Preoperative views before final dorsal refinement are shown in Figure 17 . A schematic overview of the cartilaginous dorsum cerclage sequence is provided in Figure 18 . ( See figure, Supplemental Digital Content 8 , which shows structural contouring. Preoperative left lateral view, https://links.lww.com/PRSGO/F52.)

Fig. 17. Phase 4: structural contouring. Preoperative frontal view.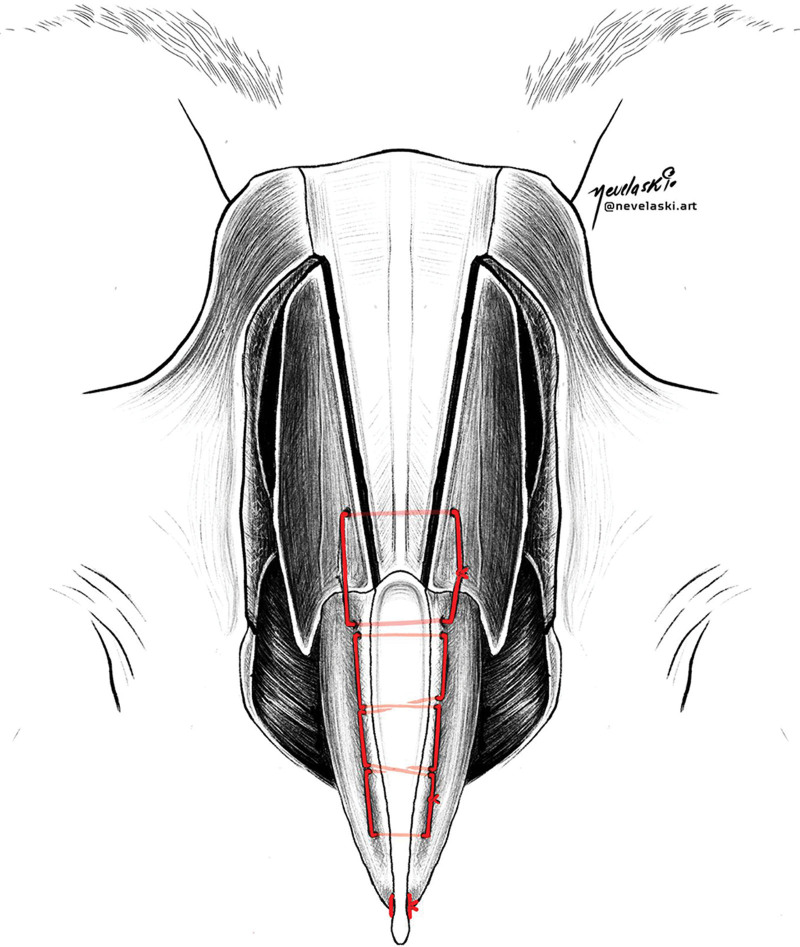
Fig. 18. Phase 4: cartilaginous dorsum cerclage. Illustrative depiction of continuous suture 2 mm posterior to the dorsum to stabilize the lateral wall and create the resting angle of the upper lateral cartilage.Intraoperatively, functional valve patency is first confirmed. A continuous 5-0 PDS suture is then placed approximately 2 mm posterior to the dorsal surface, extending toward the keystone area to stabilize the lateral nasal wall and define the resting angle of the upper lateral cartilage (Fig. 19 ).
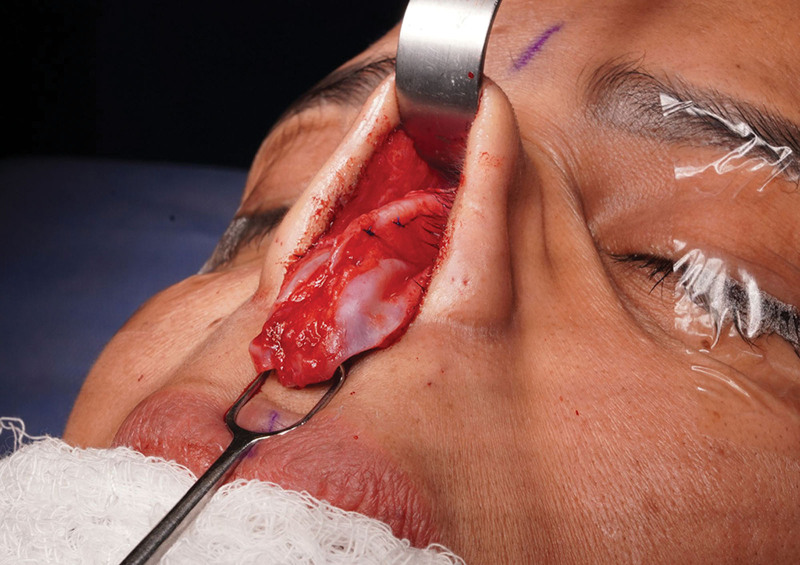
Fig. 19. Cartilaginous dorsum cerclage. Intraoperative image demonstrating continuous cerclage suture from the unobstructed area to the keystone, 2 mm posterior to the dorsum, stabilizing the lateral wall and defining the resting angle of the upper lateral cartilage.Postoperative views demonstrating restoration of parallel and well-defined dorsal aesthetic lines are presented in Figure 20 . ( See figure, Supplemental Digital Content 9, which shows structural contouring. Postoperative left lateral view, https://links.lww.com/PRSGO/F53.)

Fig. 20. Phase 4: structural contouring. Postoperative frontal view.Postoperative management followed standard institutional protocols and is not the focus of this technical description.
补充视频 / 附件(原文未随文提供原图,可于出版方页面查看)gox-14-e7920-s001.mp4Video 1. Demonstration of the structural contour technique in rhinoplasty. The video illustrates the four-phase approach, including bony framework modification, osteochondral stabilization at the keystone area, cartilaginous refinement, and final dorsal contour definition.
Dorsal contour refinement remains one of the most challenging aspects of rhinoplasty, particularly at the osteocartilaginous junction, where subtle irregularities may become visually apparent due to the complex interaction between bony and cartilaginous structures. 7 , 8 Achieving stable integration across this transitional zone is essential for maintaining dorsal definition, structural continuity, and long-term aesthetic harmony. 9
The structural contour technique introduces a reproducible 4-phase surgical framework for progressive dorsal refinement. 10 Each phase fulfills a specific technical objective, including controlled modification of the bony vault, osteochondral stabilization at the keystone area, targeted cartilaginous repositioning, and final dorsal contour definition into a cylindrical configuration. 11 , 12 This structured sequencing allows the surgeon to address dorsal contouring in a systematic and adaptable manner according to individual anatomical requirements.
Preservation approaches have emerged as a key strategy in contemporary rhinoplasty by prioritizing maintenance of native dorsal anatomy and minimizing disruption of osteocartilaginous relationships. 13 However, in patients presenting with preexisting asymmetries, inherent dorsal irregularities, or prior nasal surgery, these strategies may not consistently provide adequate contour integration or predictable dorsal alignment. 14 – 16 In this context, structured techniques that permit controlled reshaping and stabilization of both osseous and cartilaginous components may contribute to improved dorsal aesthetic continuity and surgical predictability.
The proposed approach also builds upon established biomechanical principles of cartilage behavior. The concept of a “resting angle,” previously described for the lower lateral cartilages, is extended in this technique to the upper lateral cartilages, providing a rationale for controlled modulation of middle vault architecture and dorsal contour alignment. This contributes to enhanced structural stability while preserving internal nasal valve function and avoiding excessive tension on surrounding tissues. 17
Recent reports have highlighted both structural strategies for dorsal framework stabilization and the emerging role of biologic approaches aimed at improving cartilage regeneration and long-term contour predictability in rhinoplasty. Techniques involving autologous grafting and tissue engineering concepts have been explored to enhance soft tissue adaptation and functional reliability of nasal reconstruction. In this context, mechanically driven dorsal contouring techniques such as the structural contour framework described in this report, may provide a structured platform for the future integration of regenerative adjuncts designed to optimize osteocartilaginous healing and aesthetic durability. 18 – 20
From a technical standpoint, the structural contour technique offers a structured and reproducible operative framework characterized by progressive intraoperative adaptability and integrated management of osseous and cartilaginous components within a single surgical strategy. Rather than promoting a specific aesthetic paradigm, the technique is intended to function as a versatile tool that can be tailored according to individual anatomical characteristics and aesthetic objectives through careful surgical planning.
Limitations include the inherent learning curve associated with multiphase structural techniques and the requirement for specialized instrumentation such as piezoelectric devices and cylindrical burrs. 21 – 23 Given the descriptive nature of this technical note and the preliminary clinical experience presented, formal assessment of reproducibility, complication rates, functional outcomes, standardized NOSE scoring, and learning curve dynamics was beyond the scope of the present report.
Future prospective studies involving larger patient cohorts, longer follow-up periods, and standardized outcome measures will be necessary to further validate the clinical applicability, reproducibility, and functional impact of this technique.
This report is intended to describe the technical rationale and stepwise execution of the proposed approach, rather than to assess comparative clinical outcomes, in keeping with the scope of a technical note.
The structural contour technique provides a systematic, stepwise approach for dorsal refinement that integrates bony, osteochondral, and cartilaginous maneuvers within a single surgical framework. By addressing the nasal dorsum as a continuous structural unit, this technique allows controlled shaping of dorsal aesthetic lines while preserving nasal valve function. As a technical note, this report aims to describe the surgical rationale and execution of this approach, offering a reproducible and adaptable method for dorsal contour management in selected rhinoplasty cases. Further prospective studies with larger patient cohorts and longer follow-up will be required to validate clinical outcomes and reproducibility of the described maneuvers.
The authors have no financial interest to declare in relation to the content of this article.
The patients provided written consent for the use of their images.
This technical note was conducted in accordance with the ethical standards of the institutional and national research committee and with the 1964 Declaration of Helsinki and its later amendments. Written informed consent was obtained from all patients for the surgical procedures, clinical photography, and the publication of anonymized clinical data.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
提出「结构轮廓技术(structural contour)」:将鼻背塑形整合为渐进式四阶段——骨性框架改形、keystone区骨软骨稳定、W ASA段软骨精修、软骨背环状缝合。
研究设计:PRS Global Open 回顾性研究,2016-11 至 2025-01 共 1999 例连续手术,旨在界定并塑形『腰腹过渡美学单元(waist transitio
背景:因假体并发症、乳腺植入物相关症状等需求行假体取出者增多;如何在取出同期重建自然轮廓、避免“空瘪”外观是临床难点。