电磁肌肉刺激(EMMS)不损伤人体脂肪细胞的组织学验证
2026年10月21日25 min read
Lasers in Surgery and Medicine

结论与实践要点
本研究以拟行腹部整形术的患者为对象,在人体内直接获取 EMMS 与冷冻溶脂治疗后的皮下脂肪组织,采用 H&E 与 perilipin 免疫荧光评估脂肪细胞存活及炎症反应,旨在验证 EMMS 是否如既往临床观察所提示般减少脂肪层。机制上,EMMS 经电磁场在肌层诱导强收缩,其能量分布是否波及皮下脂肪是本研究关注点。
本研究证实 EMMS 在人体内不引起脂肪细胞损伤或炎症,仅说明其“非减脂”机制,并不评价肌肉强化疗效;文献中 EMMS 临床脂肪层下降可能源于代谢改变或与饮食/运动协同,无法由本组织学直接解释。冷冻溶脂作为阳性对照显示了典型损伤,对照可靠性较好。结论外推受小样本与异质取材时间点限制。
Background and ObjectivesA previous pre‐clinical study on electromagnetic muscle stimulation (EMMS) suggested that fat cell apoptosis occurs following treatment in a porcine model. While EMMS can induce changes in muscle, the effect on fat tissue is not established. This clinical study sought to assess adipose tissue response to EMMS in comparison to cryolipolysis treatment.
Study Design/Materials and MethodsStudy subjects were recruited prior to abdominoplasty to receive body contouring treatments and subsequently to obtain tissue for histological analysis. Non‐invasive abdominal treatments were delivered using a commercially available ( n = 6) or prototype ( n = 3) EMMS system or a cryolipolysis system ( n = 2). Subjects received a single EMMS treatment (100% intensity for 30 minutes) or a single cryolipolysis treatment (−11°C for 35 minutes) to the abdomen. Superficial and deep (i.e., adjacent to muscle layer) subcutaneous adipose tissue was harvested at set timepoints post‐treatment. The presence or absence of an inflammatory response was evaluated using standard hematoxylin and eosin (H&E) staining. As adipocytes that are destined to become apoptotic cannot be distinguished by traditional H&E staining during the early phases of injury, irreversible fat cell injury was assessed using perilipin immunofluorescence.
ResultsFollowing H&E histological analysis at 3, 10, 11, and 17 days post‐treatment, no EMMS‐treated samples showed an inflammatory response in either the superficial or deep subcutaneous adipose tissue. For the cryolipolysis‐treated adipose tissue, however, the H&E staining revealed a marked inflammatory response with an influx of neutrophils, lymphocytes, and macrophages at timepoints consistent with previous histological studies. Further, loss of perilipin staining provided clear visual evidence of irreversible fat cell injury in the cryolipolysis‐treated adipose tissue. In contrast, the electromagnetic muscle stimulation‐treated samples showed persistence of perilipin staining of adipose tissue indicating that all fat cells were viable.
ConclusionThis study failed to demonstrate either fat cell injury or inflammatory response following EMMS treatment. While electromagnetic muscle stimulation may non‐invasively induce muscle changes, this clinical study found no evidence of an impact injurious or otherwise on subcutaneous fat. © 2020 The Authors. Lasers in Surgery and Medicine published by Wiley Periodicals LLC
Keywords: apoptosis、cryolipolysis、EMS、EMMS、electromagnetic muscle stimulation、HIMMS、HIFEM、histology、MMS、muscle toning、muscle strengthening、NMES、non‐invasive body contouring、non‐surgical fat reduction、perilipin、qPCR、TUNEL
There is continued interest on the part of the public in seeking safe and effective aesthetic improvement in the absence of downtime commonly associated with surgical procedures. Non‐invasive body contouring with cryolipolysis is a popular fat reduction procedure that treats undesirable subcutaneous fat with controlled cooling. Cryolipolysis is based upon the greater susceptibility of lipid‐rich adipocytes to cold injury compared with surrounding water‐rich cells [ 1 , 2 , 3 ]. Numerous clinical studies have demonstrated the safety, efficacy, and tolerability of cryolipolysis in multiple body areas including the abdomen, flanks, inner thighs, outer thighs, arms, back, bra fat area, banana roll, and submental area [ 4 , 5 , 6 , 7 , 8 , 9 , 10 , 11 ].
As patients grow increasingly comfortable with aesthetic procedures and non‐invasive body contouring, so does their appetite for greater refinement in appearance. In addition to reducing unwanted subcutaneous fat, some patients are interested in toning of the underlying muscles, while improving their feeling of well‐being and performance in the gym or on the athletic field.
Recently, electromagnetic muscle stimulation (EMMS) has been developed for aesthetic body contouring. While electromagnetic muscle stimulation has been utilized for decades in physical therapy and urological applications, it is a new technology in the field of aesthetic medicine. Based upon the inherent electrical properties of the skin, fat, and muscle, current flow can be induced directly in the muscle layer, stimulating powerful contractions without dermal discomfort. Clinical studies have been conducted to show safety and efficacy of EMMS for body contouring in the abdomen and buttocks [ 12 , 13 , 14 , 15 , 16 ]. EMMS has also been used for toning and strengthening thighs. Induction of muscle fiber hypertrophy has been reported following electromagnetic muscle stimulation treatment in a porcine model [ 17 ].
It has been hypothesized that EMMS can cause fat cell injury, specifically induction of fat apoptosis in a porcine model after a single treatment [ 18 ]. These results, however, have not yet been proven to occur in human subjects. Human histology has not demonstrated a post‐inflammatory response that would normally follow injury to a large number of adipocytes and the subsequent digestion and removal of cellular debris. These histologically observable events would be expected to precede a clinically measurable fat layer reduction.
Fat cell injury can be assessed directly or indirectly. Direct assessment can be achieved by measuring the viability of the adipocyte outer plasma membrane or inner lipid droplet membrane. Perilipin is a key regulator of lipolysis in adipocytes, where it is abundantly expressed as a phosphoprotein associated with the adipocyte lipid droplet [ 19 ]. It serves important functions in the regulation of both basal and hormonally stimulated lipolysis [ 20 ]. Under basal conditions, perilipin restricts the access of cytosolic lipases to lipid droplets and thus promotes triglyceride storage. In times of energy deficit, perilipin is phosphorylated by protein kinase A and facilitates maximal lipolysis by hormone‐sensitive lipase and adipose triglyceride lipase [ 21 ]. Investigations on the fate of adipocytes have pointed out that living and dead adipocytes cannot be distinguished with traditional H&E staining but can be distinguished with immunohistochemistry for perilipin [ 22 ]. Thus, perilipin staining has become a standard method of assessing adipocyte viability in research areas such as fat grafting [ 22 , 23 , 24 ]. Nevertheless, hematoxylin and eosin (H&E) staining is a powerful tool to inspect the inflammatory response post‐treatment and can be used as an indirect marker of fat injury.
In summary, while EMMS treatment can induce muscle changes, its effect on fat tissue is not well‐established. This study investigated adipose tissue response to electromagnetic muscle stimulation in comparison to cryolipolysis using H&E and perilipin immunofluorescence staining.
This was a multicenter, prospective, open label, non‐randomized feasibility study. The protocol was approved by an independent review board (Salus IRB, Austin, TX). Eligible subjects were male or female, at least 18 years of age, with a scheduled surgical excision of abdominal fat and skin.
Exclusion criteria included previous surgical procedures such as liposuction or non‐invasive fat reduction in or near the treatment area in the past 6 months, a known history of cryoglobulinemia, cold urticaria, cold agglutinin disease, paroxysmal cold hemoglobinuria, Raynaud's disease, bleeding disorders, or concurrent medications that could increase the risk of bruising, dermatological conditions such as excessive skin laxity or scars that may interfere with the treatment or evaluation, intrauterine contraceptive device inserted or removed within the past month, cardiac disorder, pulmonary insufficiency, and metal implant or active implanted devices such as a pacemaker, defibrillator, or drug delivery system.
Subjects had a single EMMS treatment visit with one applicator placed on the center of the abdomen. Each EMMS treatment cycle was delivered at 100% intensity for 30 minutes. Six subjects were treated with System A (Emsculpt; BTL Industries, Marlborough, MA) and three were treated with System B (CoolTone Prototype; ZELTIQ Aesthetics, Pleasanton, CA).
Two subjects were treated on the abdomen with a cryolipolysis system (CoolSculpting; ZELTIQ Aesthetics, Pleasanton, CA) using one cycle per treatment area (−11°C for 35 minutes) delivered by a cooled cup vacuum applicator (CoolAdvantage applicator series, ZELTIQ Aesthetics, Pleasanton, CA). A protective gel pad (CoolAdhesive GelPad, ZELTIQ Aesthetics, Pleasanton, CA) was applied to the skin and suction was initiated. With the applicator thus secured to the treatment area, the subject reclined throughout the cryolipolysis procedure. At the end of the treatment cycle, the applicator was removed, and a manual massage of the treatment area was performed for 2 minutes. Safety was monitored by documentation of any adverse events throughout the study, as was clinical assessment of the treatment site.
One treated and one untreated control sample was taken from each study subject. Subcutaneous fat harvested from the treated areas was further subdivided into superficial and deep specimens to assess whether the fat that was immediately adjacent to the stimulated muscle was impacted more than the superficial fat. Harvested tissue was immediately fixed in formalin after surgery and later processed for histological study using standard H&E and perilipin immunofluorescence staining.
Perilipin immunofluorescence optimization was performed on formalin‐fixed paraffin‐embedded 5‐μm tissue sections using a BOND automated immunostainer (Leica Biosystems, Buffalo Grove, IL) and an anti‐perilipin antibody (#ab61682; Abcam, Cambridge, MA) at 1:1000 dilution. Heat‐induced antigen retrieval was performed using a BOND Epitope Retrieval Solution 2 (Leica Biosystems) (ethylenediaminetetraacetic acid solution, pH 9.0) for 20 minutes. Non‐specific background was blocked with Novolink Protein Block (Leica Biosystems). Slides were incubated with primary antibody overnight at 4°C, followed by incubation with Alexa Fluor® 647 Donkey α‐Mouse IgG (H + L) (Invitrogen, #A31571, Lot#1900251, Thermo Fisher Scientific, Waltham, MA) secondary antibody at 1:200 dilution. Slides were mounted with 4′,6‐diamidino‐2‐phenylindole (DAPI) in Fluoro‐Gel II (Thermo Fisher Scientific) for nuclear visualization.
Eleven subjects were enrolled and completed treatment. All subjects were female and n = 6 Hispanic/Latino, n = 2 Asian, n = 2 Caucasian, and n = 1 African American.
The subject ages ranged from 33 to 49 years (mean 41.5 years). The average weight was 171.7 lbs. (range 132–208 lbs.) with mean body mass index 29.1 kg/m 2 (range 24.9–34.0).
As shown in Table 1 , subjects had abdominoplasty surgery from 3 to 17 days after the EMMS or cryolipolysis procedures.
Table 1 Treatment Systems and Surgical Timepoints
| Treatment system | Subjects ( n ) | Subject ID | Age (years) | BMI | Race/ethnicity | Time point (days) |
|---|---|---|---|---|---|---|
| EMMS System A | 6 | OKA‐050 | 40 | 32.6 | Hispanic | 3 |
| OKA‐052 | 49 | 29.8 | Hispanic | 3 | ||
| OKA‐051 | 48 | 30.0 | Hispanic | 10 | ||
| BAC‐021 | 39 | 27.2 | Caucasian | 11 | ||
| OKA‐053 | 33 | 24.9 | Asian | 17 | ||
| OKA‐056 | 46 | 27.6 | Hispanic | 17 | ||
| EMMS System B | 3 | OKA‐047 | 46 | 30.2 | African American | 3 |
| OKA‐048 | 44 | 25.1 | Hispanic | 10 | ||
| OKA‐058 | 42 | 26.6 | Caucasian | 10 | ||
| Cryolipolysis | 2 | BAC‐018 | 33 | 34.0 | Hispanic | 11 |
| OKA‐035 | 37 | 32.6 | Asian | 17 |
All histology slides were carefully inspected for any tissue processing artifacts and proper perilipin staining. Histology samples stained with H&E are shown in Figures 1 , 2 , 3 for EMMS‐treated samples at 3, 11, and 17 days. The EMMS‐treated samples harvested from the superficial and deep subcutaneous fat layers, at all timepoints analyzed, and in both the treated and control sites, were similar with no signs of an inflammatory response.
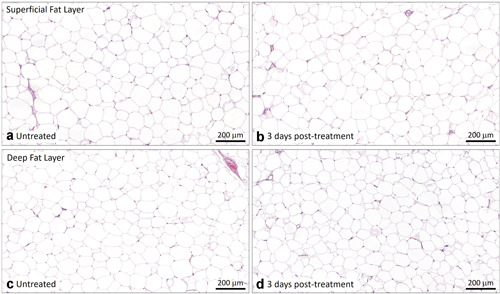
Fig. 1 Representative untreated control (a,c) and EMMS‐treated (b,d) tissue from superficial (a,b) and deep (c,d) subcutaneous fat layers, harvested 3 days post‐treatment, subject OKA‐050. H&E stain, Scale bar = 200 μm. EMMS, electromagnetic muscle stimulation; H&E, hematoxylin and eosin.EMMS 治疗 3 天后浅层/深层皮下脂肪的 H&E 染色(对照 vs 治疗),示脂肪结构正常、无炎症。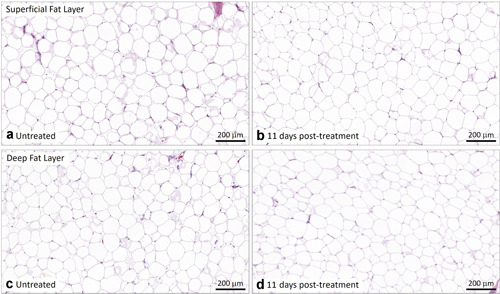
Fig. 2 Representative untreated control (a,c) and EMMS‐treated (b,d) tissue from superficial (a,b) and deep (c,d) subcutaneous fat layers, harvested 11 days post‐treatment, subject BAC‐021. H&E stain, Scale bar = 200 μm. EMMS, electromagnetic muscle stimulation; H&E, hematoxylin and eosin.EMMS 治疗 11 天后浅层/深层皮下脂肪 H&E 染色,治疗侧与对照相似、无炎症浸润。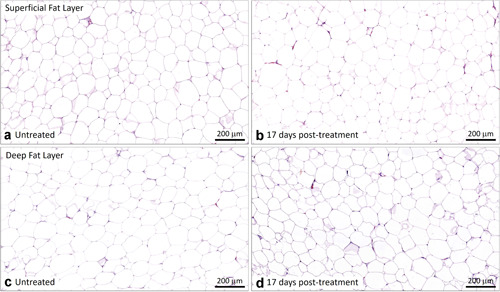
Fig. 3 Representative untreated control (a,c) and EMMS‐treated (b,d) tissue from superficial (a,b) and deep (c,d) subcutaneous fat layers, harvested 17 days post‐treatment, subject OKA‐053. H&E stain, Scale bar = 200 μm. EMMS, electromagnetic muscle stimulation; H&E, hematoxylin and eosin.EMMS 治疗 17 天后浅层/深层皮下脂肪 H&E 染色,仍未见炎症 response。Similarly, there was no loss of perilipin staining in the EMMS‐treated samples, indicating viable adipocytes throughout the superficial and deep fat layers and the absence of any disruptive effect on perilipin. Specifically, Figures 4 , 5 , 6 show untreated control samples alongside EMMS‐treated samples at 3, 11, and 17 days, respectively. All these adipocyte specimens have the usual bright yellow immunofluorescent stain marking the periphery of the adipocyte lipid droplet membrane. Nuclear stain marker is shown in blue.
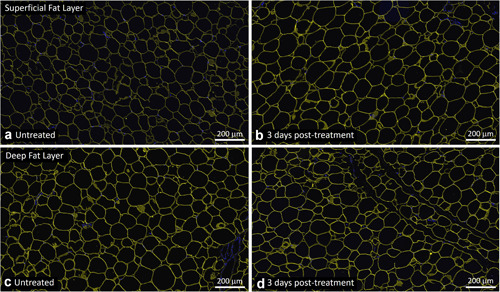
Fig. 4 Representative untreated control (a,c) and EMMS‐treated (b,d) tissue from superficial (a,b) and deep (c,d) subcutaneous fat layers, harvested 3 days post‐treatment, subject OKA‐050. Perilipin immunofluorescence stain (TRITC, yellow) and nuclear stain (DAPI, blue), Scale bar = 200 μm. DAPI, 4′,6‐diamidino‐2‐phenylindole; EMMS, electromagnetic muscle stimulation.EMMS 治疗 3 天后 perilipin 免疫荧光(黄)与 DAPI(蓝),脂肪细胞 perilipin 持续存在提示存活。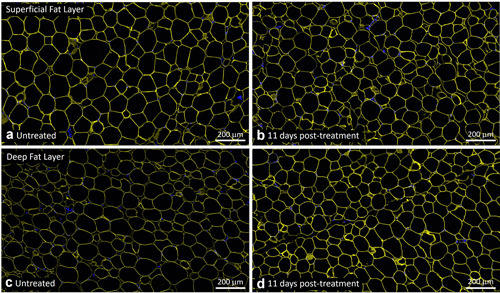
Fig. 5 Representative untreated control (a,c) and EMMS‐treated (b,d) tissue from superficial (a,b) and deep (c,d) subcutaneous fat layers, harvested 11 days post‐treatment, subject BAC‐021. Perilipin immunofluorescence stain (TRITC, yellow) and nuclear stain (DAPI, blue), Scale bar = 200 μm. DAPI, 4′,6‐diamidino‐2‐phenylindole; EMMS, electromagnetic muscle stimulation.EMMS 治疗 11 天后 perilipin 免疫荧光,治疗侧与对照均显示完整 perilipin 染色。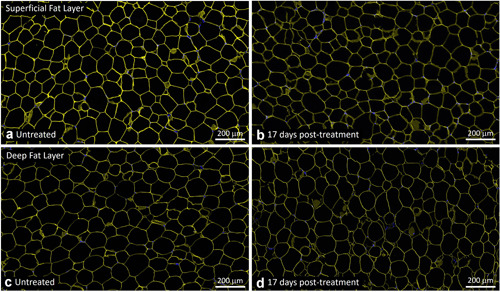
Fig. 6 Representative untreated control (a,c) and EMMS‐treated (b,d) tissue from superficial (a,b) and deep (c,d) subcutaneous fat layers, harvested 17 days post‐treatment, subject OKA‐053. Perilipin immunofluorescence stain (TRITC, yellow) and nuclear stain (DAPI, blue), Scale bar = 200 μm. DAPI, 4′,6‐diamidino‐2‐phenylindole; EMMS, electromagnetic muscle stimulation.EMMS 治疗 17 天后 perilipin 免疫荧光,脂肪细胞仍存活、无 perilipin 丢失。Figures 7 and 8 compare cryolipolysis‐treated tissue to untreated controls and EMMS‐treated samples stained with H&E. The cryolipolysis‐treated tissue exhibits an inflammatory response in the fat layer, which is consistent with previously published histology data [ 1 , 2 , 3 ] and is characteristic of injured fat. The control and EMMS‐treated samples, however, showed no inflammatory response and look very similar. Figures 9 and 10 confirm the H&E observations. In contrast, the cryolipolysis‐treated samples show loss of perilipin within the subcutaneous fat, indicative of irreversible fat cell injury. The EMMS‐treated samples, however, look comparable to the untreated controls and exhibit no signs of adipocyte injury.
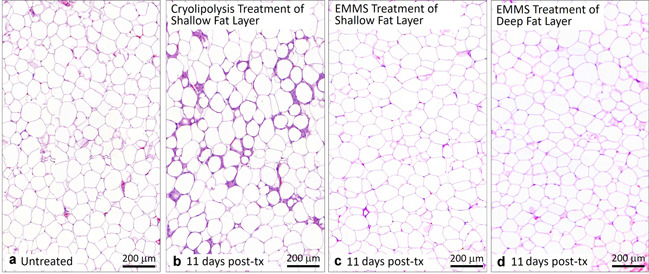
Fig. 7 Comparison of (a) untreated control, (b) cryolipolysis, and EMMS‐treated tissue (c) superficial and (d) deep fat, harvested 11 days post‐treatment. H&E stain, Scale bar = 200 μm. DAPI, 4′,6‐diamidino‐2‐phenylindole; EMMS, electromagnetic muscle stimulation; H&E, hematoxylin and eosin.第 11 天对照/冷冻溶脂/EMMS 浅层与深层脂肪 H&E 比较:冷冻溶脂呈现炎症,EMMS 与对照相似。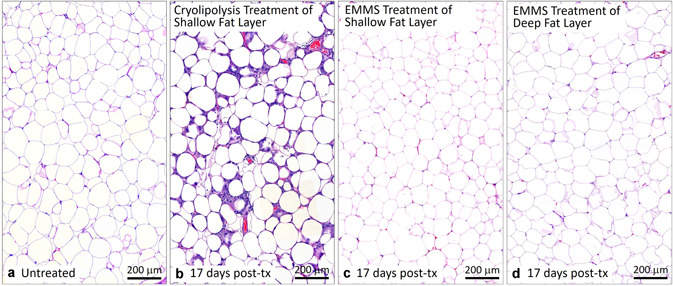
Fig. 8 Comparison of (a) untreated control, (b) cryolipolysis, and EMMS‐treated tissue (c) superficial and (d) deep fat, harvested 17 days post‐treatment. H&E stain, Scale bar = 200 μm. EMMS, electromagnetic muscle stimulation; H&E, hematoxylin and eosin.第 17 天对照/冷冻溶脂/EMMS 浅层与深层脂肪 H&E 比较:冷冻溶脂炎症明显,EMMS 无炎症。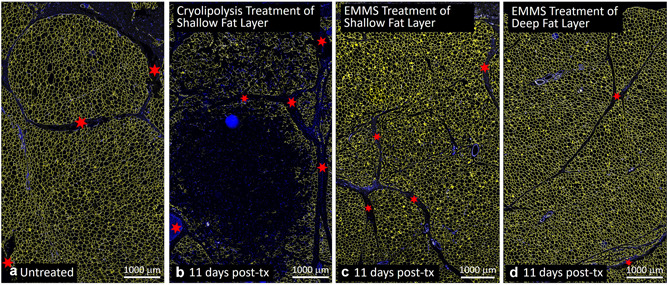
Fig. 9 Comparison of (a) untreated control, (b) cryolipolysis, and EMMS‐treated (c) superficial and (d) deep adipose tissue, harvested 11 days post‐treatment. Perilipin immunofluorescence staining (TRITC) shown in yellow. Nuclear stain (DAPI) shown in blue. Scale bar = 1000 μm. Red stars highlight fiber septae or connective tissue structures. DAPI, 4′,6‐diamidino‐2‐phenylindole; EMMS, electromagnetic muscle stimulation.第 11 天 perilipin 免疫荧光比较:冷冻溶脂区 perilipin 丢失(黄染减少),EMMS 与对照保留。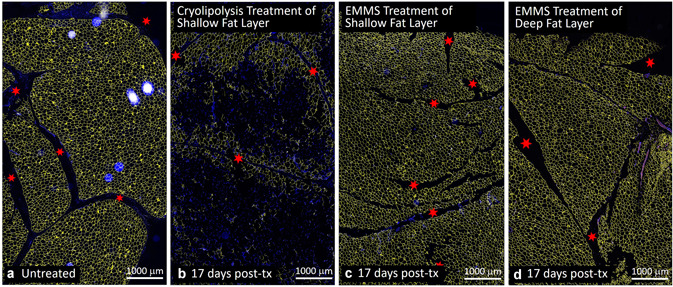
Fig. 10 Comparison of (a) untreated control, (b) cryolipolysis (17 days post‐treatment), and EMMS‐treated (c) superficial and (d) deep adipose tissue (17 days post‐treatment). Perilipin immunofluorescence staining (TRITC) shown in yellow. Nuclear stain (DAPI) shown in blue. Scale bar = 1000 μm. Red stars highlight fiber septae or connective tissue structures. DAPI, 4′,6‐diamidino‐2‐phenylindole; EMMS, electromagnetic muscle stimulation.第 17 天 perilipin 免疫荧光比较:冷冻溶脂区脂肪细胞损伤,EMMS 区与对照均完好。
This is the first study to compare adipocyte viability after EMMS and cryolipolysis in human adipose tissue. There are numerous clinical studies on EMMS and cryolipolysis showing clinical safety and efficacy, but there is little published fundamental research exploring the microscopic effect on subcutaneous adipose tissue following clinical treatment.
This feasibility study is limited by the small sample sizes and differing post‐treatment timepoints. The tissue specimens were obtained from abdominoplasty surgeries and timepoints vary somewhat based upon surgical schedule and study subject availability for experimental device treatment. Pre‐abdominoplasty study subjects are difficult to recruit and the clinical studies require significant resources, thus the resultant small sample sizes limit the feasibility study data from being generalized to the entire population.
In this study, two different EMMS systems were used. Histology results were similar between the two and the sample sizes are too small to statistically differentiate between the two systems. Thus, the data are pooled for both EMMS systems here.
The assessment of fat cell injury and loss is based on two characteristic features that are present in the case of irreversible fat injury: the first is loss of cell viability and the second is an inflammatory response due to fat cell death. The two major modes of cell death, which might occur following energy‐based device treatments, are necrosis and apoptosis. Although there are wide morphological differences between necrosis and apoptosis, both present cell membrane alterations indicative of injury.
During necrosis, the ultimate breakdown of the plasma membrane causes cytoplasmic contents to be released extracellularly, and in vivo , necrotic cell death is often associated with extensive tissue damage and an intense inflammatory response. In contrast, during apoptosis, the plasma membrane initially maintains its integrity; later, however, cells undergo morphological changes, such as cytoplasm shrinkage, and fragmentation into smaller bodies. In the case of adipocytes, the cell membrane and the lipid droplet membrane have an active metabolic function in homeostatic and stimulated conditions such as lipogenesis and lipolysis [ 25 ].
Accordingly, irreversible injury can be detected by the loss of key membrane‐associated proteins, such as perilipin. Although an often‐accepted dogma is that apoptotic cells do not cause inflammation, there is evidence that apoptotic adipocytes are phagocytosed and digested by macrophages [ 26 , 27 , 28 ]. Since adipocytes can be tens of times larger than macrophages and since the apoptotic rate may be much higher than the regularly encountered magnitudes in other cells/tissues, adipocytes are too large and too abundant to be digested by conventional phagocytic processes by resident phagocytes. Consequently, inflammatory cells need to be recruited to the zone of injury for proper digestion and clearance of adipocytes. Uptake and complete degradation of adipocytes requires a high number of macrophages resulting in many foam cells, which are clearly visible histologically with standard microscopy [ 29 , 30 ].
Both EMMS systems showed similar histological results when comparing the treated tissue and the untreated controls. The EMMS treatment did not produce loss of adipocyte viability, as indicated by persistence of perilipin immunofluorescence staining, or an inflammatory response as evaluated by H&E staining, as shown in Figures 1 , 2 , 3 , 4 , 5 , 6 . The cryolipolysis‐treated tissue, in contrast, showed both an inflammatory response in the subcutaneous fat and loss of perilipin, indicative of irreversible adipocyte injury, as shown in Figures 7 , 8 , 9 , 10 .
While this study found no fat cell injury following EMMS treatment, previously published studies have suggested fat layer reduction. Clinical studies have demonstrated fat layer reduction as measured by computed tomography, magnetic resonance imaging, and ultrasound [ 12 , 13 , 14 , 15 , 16 ]. It is possible that the fat layer is reduced by metabolic changes that are not yet understood following EMMS treatment or due to synergistic changes in diet and/or physical activity, which cannot be observed histologically. But the current study results show that the fat cells are not injured following EMMS treatment and did not result in the cellular and inflammatory response typically seen following cryolipolysis or other energy‐based device procedures, such as high‐intensity focused ultrasound or non‐thermal focused ultrasound or laser heating.
Prior to the clinical study discussed here, we reviewed a previously reported pre‐clinical study that found evidence of apoptosis in a porcine model [ 18 ]. We did carefully replicate the published study methods for the porcine study and failed to reproduce the results for apoptosis following EMMS treatment. Both fluorometric and colorimetric terminal deoxynucleotidyl transferase dUTP nick end labeling (TUNEL) staining and quantification was used along with assessment of RNA markers via quantitative polymerase chain reaction analysis in the replication study and all methods failed to replicate the published results for apoptosis in a porcine model. Those pre‐clinical study replication results are consistent with the clinical data reported here, showing no effect of EMMS treatment on the adipose tissue layer.
There is much left to explore in the field of fat metabolism and adipocyte response to injury. While this study found consistent lack of fat cell inflammatory response and loss of perilipin in response to EMMS treatment, the study size was small. In a larger population, adipose tissue metabolism will vary from patient to patient and in response to degree of external injury. Additional fundamental research is warranted to further explore fat injury and metabolism.
EMMS is an exciting new energy‐based device treatment that utilizes electromagnetic energy to induce powerful contractions in the targeted muscle layer. This procedure appears to produce clinically meaningful changes in the muscle layer leading to toning, strengthening, and firming and, anecdotally, improved balance. It may be an important new procedure to complement a variety of non‐invasive body contouring procedures, such as cryolipolysis, radiofrequency heating, 1060 nm laser heating, high‐intensity focused ultrasound, and non‐thermal focused ultrasound. This procedure is relatively new to the world of aesthetic medicine and more basic science research should be done to explore the effect on the underlying muscle, fat, and skin layers.
A fundamental viability study was conducted to explore fat cell injury following cryolipolysis and EMMS for non‐invasive body contouring in human subjects. The EMMS treatment failed to produce either fat cell injury or an inflammatory response, whereas the cryolipolysis treatment induced an inflammatory response in the H&E stained adipose tissue and loss of perilipin in the immunofluorescence stained tissue, indicative of irreversible fat cell injury.
声明:中文精读 · 仅供学术参考。内容来自公开文献检索,不代表本人观点,不构成诊疗建议。 医疗美容需在正规医疗机构由执业医师实施。
基于相同主题推荐 · 继续深挖
多中心、前瞻性、开放性、非随机可行性研究,纳入 11 例拟行腹部整形术的女性受试者(33–49 岁,均值 41.5 岁;BMI 均值 29.1),在体内直接比较 EMMS 与冷冻溶

背景:冷冻溶脂为非侵入性、耐受良好的皮下减脂手段;新型双治疗头系统可同时治疗多个部位、提升治疗效率。
1997-2023年共988例出生分配为男性的性别焦虑者接受唇女性化与年轻化,累计1789例次手术,年龄22-75岁(平均39.5岁),79.8%小于50岁。